I. INTRODUCTION
Equitable access to quality and timely diagnosis linked to appropriate care is critical for ensuring health for all. However, access to testing is the weakest link across the patient care-seeking pathway [1]. On the other hand, specimen referral systems play a critical role in ensuring access to laboratory services by allowing patients to receive care and treatment at one location, while their specimens are transferred to various levels of a tiered laboratory system for testing [2].
Delivering patient-centred and equitable diagnostic testing services is complex. Despite significant investments over the past decade to strengthen diagnostic systems, particularly for HIV and tuberculosis (TB), critical gaps and weaknesses remain [3, 4, 5].
Referral systems can efficiently increase access to diagnostics in areas where testing is not available, prevent the need and associated costs for patients to travel, and lead to equity in access to health care. Furthermore, tests centralized or regionalized testing and a robust specimen referral system may be more cost-effective than placing staff, procuring, and maintaining equipment to conduct testing at lower levels [2].
The goal of a diagnostic network to deliver the right amount of testing, in the right place, at the right time, for the right people and at an affordable and sustainable cost, ensuring that accurate test results are delivered in a timely manner to inform patient care and public health decision-making, on a scale consistent with national goals and strategies. The present study aim was to evaluate the efficiency of the new secondary package for biological sample, locally developed in Maputo-Mozambique to respond the challenge of spillage, reducing the loss of sputum for TB diagnostic.
II. METHOD
a) Study design and area
To prevent spillage of samples, Local TB Response (LTBR)/FHI360 collaborated with National TB Reference Laboratory (NTRL) to design and pilot use of individualized, water and leak-proof insulated secondary packaging and ensure triple packaging for TB specimens transport as recommended. The secondary packaging was piloted in 5 districts of Zambezia province (Quelimane, Namacurra, Morumbala, Lugela and Pebane), two with good access roads and other three with poor access roads, what may contribute to increase samples spillage during twelve weeks. LTBR ADPP activists and motorbike riders were trained on usage of the secondary package to transport sputum samples from remote communities and/or peripheral Health Facilities to Health Facilities with laboratory services, using bicycle and motorbikes with cooler boxes.
b) Brief Information about Zambezia
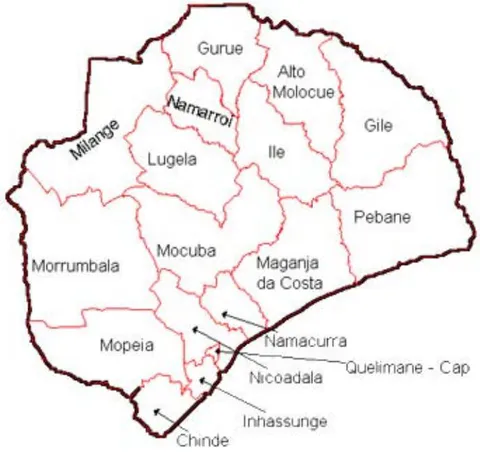
Zambezia Province is located in central Mozambique, bordered by Nampula and Niassa Provinces to the North, Malawi and Tete Province to the West, Sofala Province to the South and the Indian Ocean to the East. It has an area of , with Quelimane as its capital city. The Province is divided in 22 Districts and 6 Municipalities. As of 2017, Zambezia has a total population of 5,164,732, which is equivalent to roughly of the national population (INE). About of the population is female. The economy is dominated by subsistence agriculture; a few of the cash crops include cashews, sesame seeds and cotton. Artisanal fishing and livestock production are also important subsectors in the socioeconomic life of the population for employment, income and food security. Other important sectors include tourism (eg Gilé National Reserve, Namuli Mountain and Primeiras e Segundas Environmental Protected Area), trade and manufacturing. Zambezia Province is responsible for of Mozambique's Gross Domestic Product (GDP) and of the population of the Province is living below poverty line [6].
c) The role of community activists selected
Local staffing requirements were identified and a programme of staff training was developed. Local community outreach worker was prior employed through the project TB Response in order to access all affected communities with known or suspicious TB cases. For this study, we used the same people and in meantime, laboratory technician and a TB coordinator were appointed and trained on use of the secondary package.


Using approach for tuberculosis treatment, the activists hired by TB Response play a similar role as DOTS in tuberculosis treatment and control. Basically, they are well-trained health care worker or other designated individual (excluding a family member) who provides the prescribed TB drugs and watches the patient swallow every dose, gives instruction on sample collection and follow the contacts of people with DR TB or DS TB, delivering the prescribed medication, checking for side effects, watching the patient swallow the medication, documenting the visit and answering questions.
The strategy has been successful, it helps prevent TB from spreading to others, decreases the risk of drug-resistance resulting from erratic or incomplete treatment, decreases the chances of treatment failure and relapse.
The big challenge noted during these activities was the boxes used by the activists to transport sputum from the community to health facility avoiding spillage. Because of improvised boxes got from the pharmacy, not all sample reached the lab properly for testing and some were rejected.
To evaluate the efficiency of the new developed secondary package vs improvised boxes, specific forms were adopted to record in the lab when sample were delivering. In each district, not all activists received the new box to allow comparison result. It is, if a district selected had 4 or 5 activists, only 2 received the new boxes and others still using the improvised. It was a group control with new boxes and study group with the improvised boxes.


III. RESULTS
The outcomes of usage of the new package could be evaluated after three months of pilot from April to June 2022, when the sample where transported in both way as explained above. To improve TB sample referring system in the 4 supported provinces, TB Response Project in collaboration with the National Tuberculosis Reference Laboratory designed a compartmentalized and robust secondary packaging to prevent spills in 5 districts of Zambezia piloted by Activists and motorbike riders.
During the pilot, 2689 TB sample was transported and only 46 were rejected in the laboratory due to spillage using the improvised boxes. Data's were weekly reported and analyzed per district as we can see below.
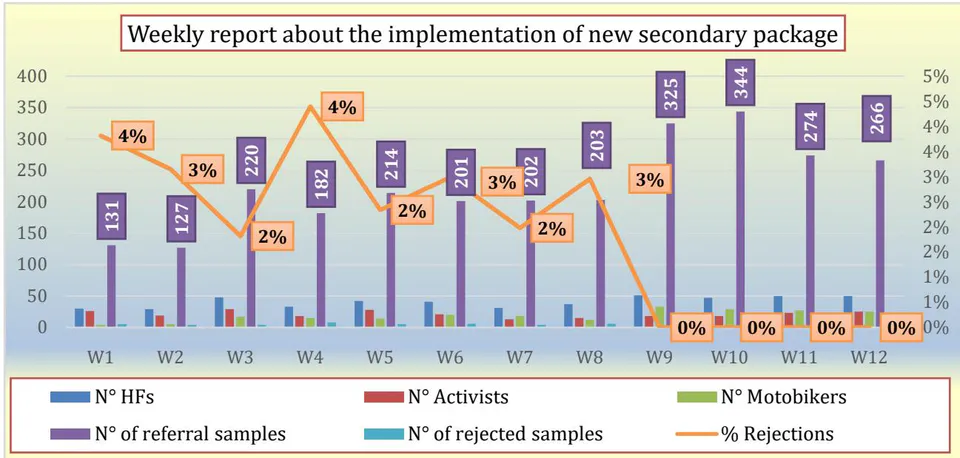
Two districts (Morrumbala and Namacurra) has 0 rejections. The Health facility with more rejected sample were Impaca (6) and Naburi (5) both in Pebane district, all associated with the improvised boxes. No spillover or rejected sample notified for all districts, using the new secondary package.
Namacurra was the district that had a lot of irregularity in the report, having reported data only in weeks 1, 3, 5, 9 and 12. A total of 108 originated were referenced, without any rejection.
Comparing the improvised boxes used by the activists and motorbike riders, we can see that they are not appropriate leak-proof seal. In case of spill is common to lose the patient opportunity to test and minimize the chance of spreading TB. Although the first approach in packaging sample must be follow the international standards, related to triple packaging as recommended, the required material is scares in the country. This is why people try to adopt easy solution to deliver the samples for testing.
IV. DISCUSSION
The interpretation of the microbiological results depends, to a great extent, on the quality of the samples received for study. Therefore, an appropriate management of the samples is necessary to achieve an optimal diagnosis in Microbiology [7]. The analyzable substances are all the biological samples available, from sterile fluids, samples from different organs or systems, such as faeces, urine, sputum, Broncho alveolar lavage, aspirates, biopsies and exudates from different locations or superficial or deep lesions, and hospital devices, such as catheters and prostheses [8].
There is a great variety of containers in which microbiological samples can be collected, with a common characteristic to all of them being that they are sterile and with a leak-proof seal [7]. The issue in the process of sample transportation, a part of the type of container, avoid spillage must be considered. As in other low-income countries, missed cases of TB have been attributed in part to difficulties transporting and handling TB specimens and Mozambique is not an exception [9]. Road infrastructure is poor and at times impassable and also contribute for spill increasing and loss of specimen [10].
The handling of the samples should only be carried out by trained and qualified personnel, who should also be in charge of their safekeeping and organization of the transportation [11]. Since samples are transported by couriers who do not take care of the samples and sometimes do not show evidence of training in biological sample management, this may be associated with the high number of spills, given the road situation also.
To transport all infectious substances, the basic triple packaging system must be used. This transport system comprises three layers: Primary container, which is the primary leak-proof and watertight container that contains the sample. This container should be wrapped in absorbent material with the capacity to absorb all the fluid in case of breakage or leakage; Secondary container, resistant, watertight, leak-proof container that encloses and protects the primary container. Several wrapped primary containers can be placed in a secondary container, but sufficient absorbent material must be used to absorb all the fluid in case of breakage or leakage and Outer container, where the secondary containers are placed in outer transport packages provided with a suitable cushioning material. The outer containers protect the contents from the external elements, such as physical damage, while the package is in transit [12].
Given the severity of the TB epidemic, innovative solutions are needed to ensure that patients have the diagnosis needed for clinical management and for public health measures [13]. Considering the different situations of spill management, safe transport of samples and safety of personnel, the secondary packaging was designed with the objective of covering these needs identified during the process of sending samples in the country.
Everyone has a responsibility to manage the potential for occupational exposures. Responsibility for the cleaning of body fluid spillage should be clear within each care setting. Following a spill, sampling programs play a vital role in documenting the extent of contamination and providing valuable information to inform clean-up strategies [14].
V. CONCLUSION
The use of the secondary packaging by activists and motorbike riders are substantially improving TB sample referencing and reducing dramatically spillage. The stroke rate also remained at . Eighty-nine percent of the rejected samples are caused by spills due to the use of TDR boxes, improvised for the transport of samples.