





INTRODUCTION
After nearly forty-two years in practice, this is a short summary of experience from our institution and also from other centers; and, especially, incorporating experiences from other colleagues, so that the idea is to share valuable stories, circumstances, and knowledge. Therefore, this paper may become a source of reference as an aid when working in this quite demanding medical and surgical specialty.
The circumstances herein described may have occurred in many centers and institutions, and we must remember that communicating and sharing our experiences may prevent the occurrence of undesirable events.
This paper is an update of a previous article that was published nine years ago. New topics that are part of our current practice have been introduced and developed. Perhaps there are not many references since this is not a strict scientific document or a rigorous research project or a paradigmatic icon in Obstetrics and Gynecology. The decision for preparing and updating this paper was based on the generous reception it achieved in different academic meetings, including symposia of the Peruvian Gynecology and Obstetrics Society, our latest National Congress; and particularly, on requests made by many dear friends and junior specialists who are so eager to learn from the experience of us, senior practitioners.
For a proper start, the four cornerstones of modern medical ethics will be introduced (Belmont Report, April 18th, 1979) and then things that MUST NOT BE DONE in Obstetrics and Gynecology will be developed.
No Maleficence: This means never causing any deliberate harm to patients under our care.
Autonomy: This is our current model and now it is replacing the traditional paternalistic attitude within medical care. This allows patients to participate in the diagnosis, management and therapy processes. This ethics value was developed after the Second World War.
Beneficence: Our actions must be solely directed towards doing the best for our patients, aiming to achieve the best benefit for all of them.
Justice: All patients must be treated equal, no matter their social condition, religion, economic status or any other particular consideration.
Coffee consumption: It is not advisable the surgeon has an excessive intake of coffee, dark tea, or alkaloid containing energizing beverages or soft drinks, prior to a surgical procedure, particularly if delicate procedures such as microsurgery are to be performed. Most soda drinks contain caffeine. Alkaloids may exacerbate adrenalin and endorphin production and they reduce the capability for performing fine movements. A good choice is to drink decaffeinated coffee or caffeine-free soda (1), (2).
Air exchange. Never miss having air exchange in the Operation Room (OR), aiming to reduce and prevent infections. Exchange must consist of using 15 times the total environmental air volume for every hour we may spend in the OR. Good quality air extractors and air conditioning devices must be available. Surgeons performing open surgical procedures, or any other procedure type should not transpire, since there is likelihood that sweat droplets may reach the operative field (3), (4).
Antibiotic prophylaxis. This measure must not be abused. Many studies, including some performed in our institution have shown that in elective surgery, patients undergoing adequate pre-surgical preparation have the same likelihood for developing any infectious complication compared with those that had received antibiotic prophylaxis, including those undergoing vaginal or abdominal hysterectomy or those undergoing a cesarean section (5),(6),(7),(8). Antibiotic misuse or abuse leads to the development of multidrug-resistant microorganisms.
NSAIDS in the immediate postoperative period. Analgesic agents that may lead to coagulation alterations must not be used, at least during the first 24 hours after pelvic surgery. The use of opiate derivatives is a preferable choice. The rich venous network and abundant vascular plexuses in the pelvis must be considered, in which the only hemostatic action we could take is compress affected tissues, without using vascular ligation or cauterization.
Appropriate dressing in the Operating Room. Hair from the head and other areas, as well as the nose, must always be covered with a cap, mask, and gown. If exposed, hair may contaminate the surgical area and the immediate surrounding environment. Some female or male doctors misuse their caps by allowing some portions of their hair to be exposed, just as if they were participating in beauty contest; which may be a reflex of their own insecurity on their physical capability (and also intellectual disability?) for attracting the opposite sex. Sometimes, their nose is not adequately covered, and maybe they ignore the number of microorganisms currently residing in this area. The larger the nose is, the larger the number and presence of potentially pathogenic microorganisms. The Operating Room and the Surgical Center are not a place for having an affair. These are places for saving lives, and for alleviating and cure patients. The most serious situation is that such behaviors may constitute a negative paradigm for all involved personnel. We are healthcare professionals, independently of sex, and no matter how good looking we are or not.
Seasonal or Occasional Infections. No sick person(s) must be allowed to enter the Operating Room, even if they should have a mild cold, low-grade fever, or any suspiciously infected skin lesion.
Wound Care. Wound care must not be performed on infected patients before entering the Surgical Area. This activity must be performed at the end of the scheduled surgery day, or personnel that is not scheduled for any surgical procedure may perform surgical care. Everyone and everything are a potential infection source.
Gloves during the Surgical Procedure. Gloves generally come impregnated with powder, aiming to prevent adhesions or leaving debris in the surgical cavity which may lead to pyrogen generation and adherence enhancement. Do not forget to wash gloves with saline solution until every residue is eliminated. Glove washing must not be done using dextrose solution, since glove covered fingers and hands may become firmly fixed (9).
Surgery times. No time limits should be established when performing a surgical procedure. This may lead to apprehension, it may alter the surgeon's mood, it creates stress in participants and in all personnel. The anesthesiologist should be cautious should he/she request to shorten or hurry the surgical procedure. Being fast for performing any surgical procedure comes with practice. The fastest professional when operating is not necessarily the best in the field. Of course, there are some exceptions to the rule.
Electrosurgical materials. Do not miss checking up where the electrocautery plaques are placed. These may lead to severe burns in patients if they accidentally get wet or if inadequate contact is achieved.
Heparin for helping with irrigation while performing videolaparoscopy. In laparoscopic surgery, do not forget to use heparin in the irrigation fluid, this prevents the formation of clots that may obscure the surgical bed. Proper heparin use allows easy fluid and blood aspiration for adequately identifying structures. The likelihood for heparin anticoagulating the patient is nil, since a minimal dose is used, and it does not generate any systemic effect.
The importance of bipolar forceps. No endoscopic gynecological procedure should be done without having adequate spare bipolar forceps. These devices are so useful for hemostasis. Without their use, rates for conversion to laparotomy would be higher, with the consequent risk for patients.
Menses during gynecological surgery. No gynecological surgery procedure should be performed, whether open or laparoscopic if the patient is menstruating (do not consider cases of abnormal uterine hemorrhage), since problems with bleeding and hemostasis may become more severe, because of the physiological alterations occurring in the coagulation cascade during this time period in women of child-bearing age (10).
Presence of a Foley catheter. Do not forget to place a permeable Foley catheter in the urinary bladder during the whole surgical procedure. Therefore, lesions in an empty bladder are prevented, and the pelvic operative field is widened, reducing the likelihood for affecting structures like the ureter and the intestines, on top of the urinary bladder.
Preoperative assessment. No surgical procedure should be started without having previously met the patient and without having performed a thorough physical examination. This latter procedure defines the type of incision to be made, the procedure type, or withhold the surgical procedure because of an inappropriate indication. Many times, some surgeons operated patients assessed by other colleagues with indications for excising cysts or fibromas; and when cavities were explored, none of such 'tumors' were found.
Intravenous access for fluid administration. No surgical procedure should be initiated without having a proper intravenous access. This is crucial for rapid fluid or blood replenishment. This is a lifesaving procedure.
Patient relaxation. A poorly relaxed patient must never be operated. We must request the anesthesiologist to have the patient completely relaxed, particularly for laparoscopic surgical procedures, unless it may be a matter of life or death. Having a patient perform Valsalva's maneuver during the surgical procedure where crucial steps are being taken, would not be feasible and it would be very risky for all.
Introducing Veress needle. The introduction of the Veress needle is to be taken so seriously when we are about to insufflate the abdomen and produce pneumoperitoneum for a laparoscopic surgical procedure. We must be so careful, since subcutaneous emphysema may occur, a blood vessel may be perforated, or an organ may be damaged.
Adequate pneumoperitoneum. The abdomen must never be inadequately insufflated when entering for the very first time in a blinded fashion while performing videosurgery. Insufflation must be adequately performed, or no insufflation is done, and then open surgery is to be performed. There are some reports of aortic perforation occurring in such circumstances (11).
Gas from pneumoperitoneum. Do not use oxygen or gases that may unfavorably affect patients when laparoscopic surgery is performed, even if they were less expensive. Oxygen is a good electricity conductor and it may inadequately conduce an electric spark. Other gases may compete for patient's oxygenation and lead to deleterious effects. The most adequate measure is to use carbon dioxide (12).
Auxiliary instruments in videosurgery. Auxiliary instruments, such as uterine manipulators, fixing forceps, separators or dual valves for irrigation must not be left apart. Some persons think that by using less instruments they might become better surgeons. They might be skillful, but they may not be working under comfortable conditions and then they may place patients at an avoidable risk. This arrogant act is against the principles of medical ethics. Adequate instruments for each circumstance must be properly used.
Horizon when doing videosurgery. When performing laparoscopic and hysteroscopic surgery, the horizon line and/or the tridimensional space must never be lost. We must demand that the cameraman follows the action maintaining these vital reference points. By doing so we will not lose the anatomical perspective and we will avoid having lesions in different organs and systems. Because of losing perspective and horizon, ureteral, bladder, and intestinal lesions have been reported. There have been cases in which bladder perforation has occurred, with invasion of the wide ligament, crossing the uterine wall.
Dorsal aspect of Fallopian tubes. When performing Fallopian tube surgery, it is important not to forget that the dorsal aspect of Fallopian tubes is the less vascularized area, and there is the place where the procedure may be safely performed.
Usefulness of irrigators in videosurgery. Do not forget that irrigators they also are helpful in dissection and not only for irrigation and aspiration. The technique is called hydrosection, and this must be mastered by every laparoscopy specialist (13).
Abdominal incision in case malignancy is suspected. No transversal incisions should be made when opening the abdomen when there is strong suspicion on the presence of a malignancy. Cancer staging or cytoreduction may become more difficult by doing so.
Gauze in surgery. Folded gauze packages must not be opened, since small pieces of thread may be left in the abdominal cavity, and these materials may become pyrogenic compounds. These should never be dragged when cleaning the area, since they may cause lesions in vascular structures and enhance the formation of adhesions.
Gauze in microsurgery. Never use dried gauze when performing microsurgery procedures. Gauze should always be humidified for use, even when solely used for hemostasis.
Aid in videosurgery. When performing laparoscopic surgery and microsurgery, you should never operate with an assistant that might have no idea of the anatomical area to work with and/or who is poorly trained. This becomes of paramount importance when they are starting their learning curve.
Coagulation and cauterization in Endoscopic Surgery. When working in endoscopic surgery, blood vessels and tissues must not be sectioned without prior cauterization. Should this not be the case, these structures may bleed and sometimes it is so demanding to stop all bleeding.
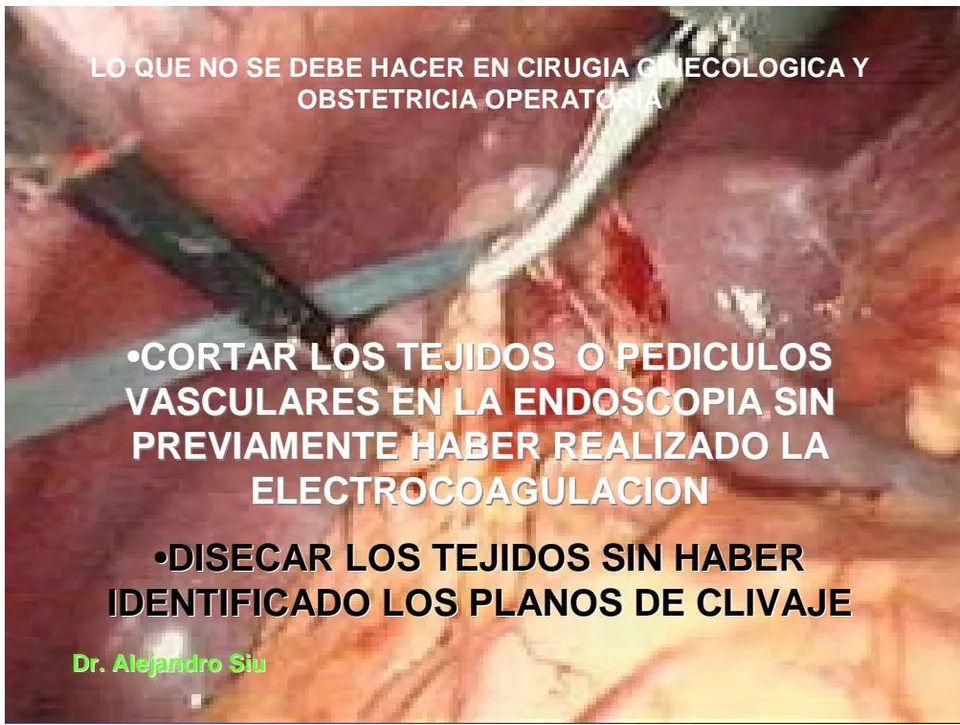
CORTAR LOS TEJIDOS O PEDICULOS VASCULARES EN LA ENDOSCOPIA SIN PREVIAMENTE HABER REALIZADO LA ELECTROCOAGULACION
DISECAR LOS TEJIDOS SIN HABER IDENTIFICADO LOS PLANOS DE CLIVAJE
Cut Down Tissues or Vascular Pedicles During Endoscopy without Having Performed Electrocoagulation
Dissect Tissues without Having Identified Cleavage Planes.
Dissection planes. Do not leave cleavage planes unidentified. Otherwise, dissection may become difficult with plenty of bleeding.
Septic foci when performing high-complexity fertilization procedures. Septic foci in laparotomy (hydrosalpinx, ovarian microabscesses) must never be left when performing laparotomy prior to a high-complexity fertilization procedure. These structures or tissues are embryotoxic, they maintain the presence of endorphins that reduce pregnancy viability (14).
Hysterotomy while performing myomectomy. No uterine corporal incisions should be made in case a myomectomy is performed. Transverse incisions are preferred since they lead to less bleeding and they also lead to less adherence formation. Although some cases have been reported where no transverse incision could be made, because of concern with respect to affect tubal ostia or because of the tumor localization.
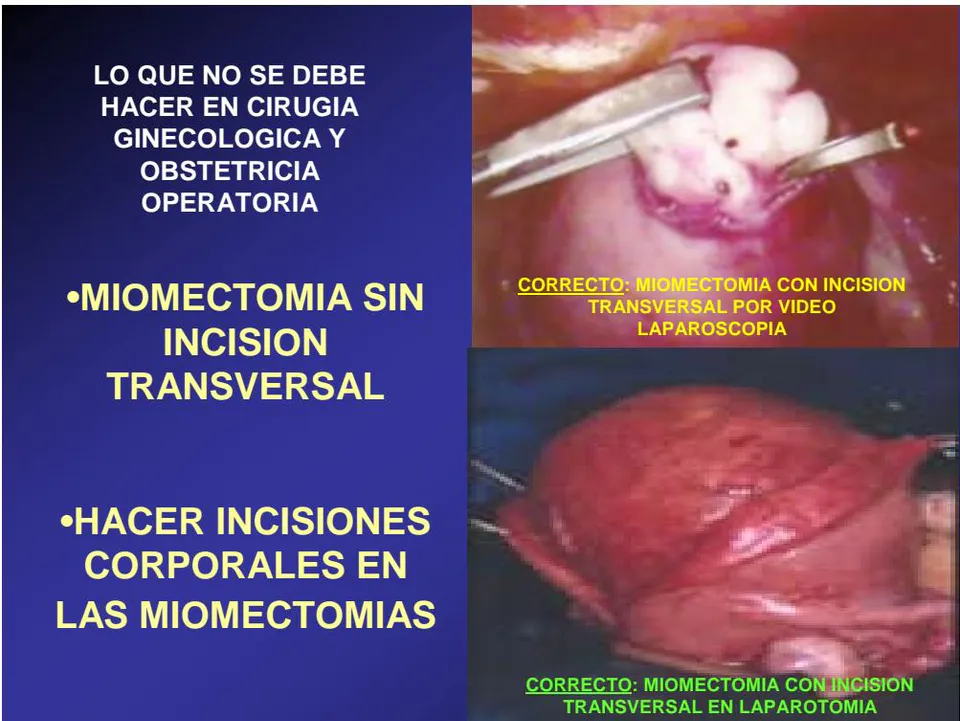
LO QUE NO SE DEBE HACER EN CIRUGIA GINECOLOGICA Y OBSTETRICIA OPERATORIA
MIOMECTOMIA SIN INCISION TRANSVERSAL
HACER INCISIONES CORPORALES EN LAS MIOMECTOMIAS
CORRECTO: MIOMECTOMIA CON INCISION TRANSVERSAL POR VIDEO LAPAROSCOPIA
Myomectomy With No Transverse Incision
Correct: Myomectomy With A Transverse Incision Using Videolaparoscopy
Making Uterine Corporal Incision In Myomectomy
Correct: Myomectomy With A Transverse Incision In Laparotomy
- Capsule of an Ovarian Endometrioma. When doing endometrioma surgery, conventional or laparoscopic, the pseudocapsule or portions of the pseudocapsule must never be left. Recurrences of the disease will be higher. The whole pseudocapsule must be excised; if this is not possible, this structure will have to be destroyed using electrical ablation (15).
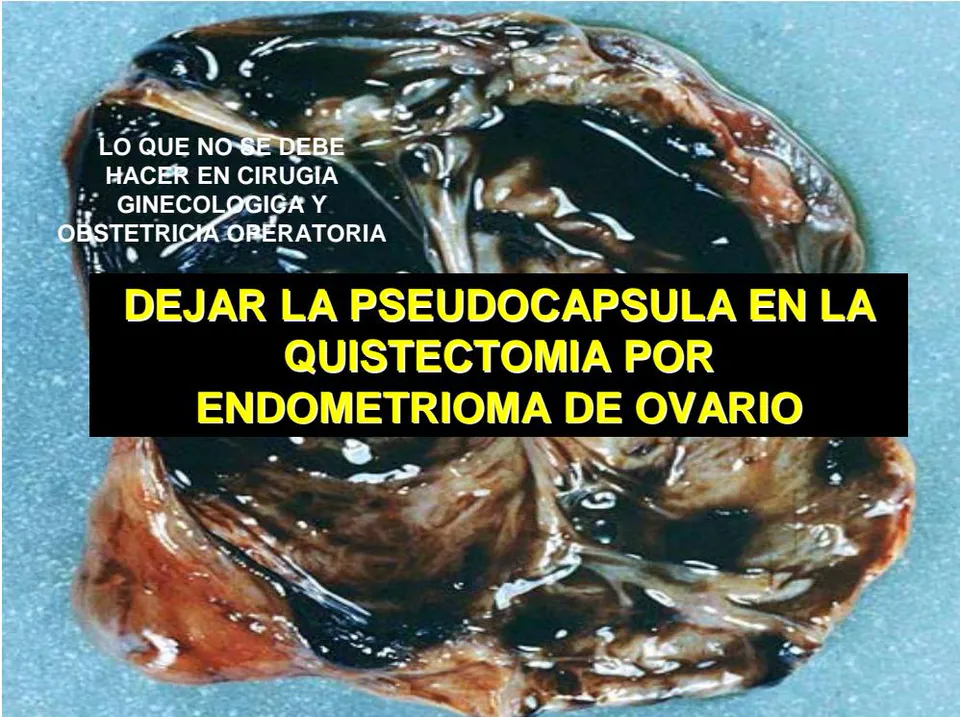
DEJAR LA PSEUDOCAPSULA EN LA QUISTECTOMIA POR ENDOMETRIOMA DE OVARIO
Leaving the Pseudocapsule when Performing Cystectomy Because of an Ovarian Endometrioma
Endometriosis areas. If endometriosis areas are being worked with, their destruction must not be superficial. Their whole depth implantation must be reached unless the implants are located upon a hollow viscus and risk of perforation may supervene. In such cases, management may incorporate complementary medical therapy (16), (17).
Uterine tumors and videosurgery. Do not intervene on uterine tumors that are extrapelvically located according to videosurgery, if no electric morcellator is available. Doing morcellation using a vaginal approach with such tumor means putting the patient at risk; and if a decision is made for using a vaginal approach, ad-hoc instruments must be readily available, including a special bayonet.
Decision for conversion. Neither folly nor silliness should prevail for deciding of converting a laparoscopic to an open surgical procedure. We must always think about the patient.
Fallopian tube microsurgery. We must never leave less than 4-cm of the Fallopian tube in case of performing reconstructive surgery. If in the projection the tube is less than 4-cm long, surgery must not be scheduled or attempted. Such tubes will never work, or they will be site for a future ectopic pregnancy (18).
Simultaneous videosurgery procedures. Do not miss combining hysteroscopic resection of deep seated myomas with simultaneous videolaparoscopy control, aiming to monitor the hysteroscopic procedure in order to prevent uterine perforation.
Importance of anatomical markers. We must not operate without knowing the anatomical markers of vascular, ureteral, and bladder crossings as well as those for all plexuses.
Hypogastric or internal iliac ligation. We must not miss the technique for hypogastric (blood vessels) ligation. Every pelvic surgeon who respects himself/herself must master the technique for locating and ligating hypogastric arteries. We must remember that these arteries downstream become uterine arteries. They are also known as internal iliac arteries and their anatomical marker is the obturator fossa or foramen, in the vicinity of the ureter.
Washing the abdominal cavity. Avoid not performing thorough washing of the abdominal cavity. Not less than 8-liter fluids or saline solution should be used when washing a cavity, especially if a perforation of a cystic teratoma had occurred, because of the risk for the development of chemical peritonitis. This washing procedure must be performed both in open surgery as well as in laparotomy.
Surgical approach for an abdominal malignant tumor. Videosurgery must never be performed when there is strong suspicion that the ovarian tumor (to be operated) is a malignant neoplasia. In such cases, an open procedure with a median incision is preferable.
Preventing pelvic adhesions. Because of not leaving enough fluid or because of leaving clot residues. When a small amount of fluid or clots are left in an unpolished surface, the generation of adherences is enhanced.
Relationship between intraabdominal pressure with hemostasis. Do not review hemostasis excessively reducing intraabdominal pressure when finishing a laparoscopic procedure. The intraabdominal pressure should be reduced to 7-mm Hg. With this level, collapse of both venules and arterioles that might bleed when taking cannulas and the laparoscope tube out is prevented.
Reviewing the places where trocars are inserted. We must never miss reviewing the places where intraabdominal trocars and cannulas for videolaparoscopy have been inserted when the procedure is over, in order to determine whether a hematoma had been formed or if there is any bleeding.
Assessing the uterine cavity during hysteroscopy. While performing a hysteroscopy we must never explore using optics or during the introduction. The exploration must always be performed taking out the optics, after reaching the end of the cervix we introduce the instrument once again until touching the uterine fundus, exploration is reinitiated, and the procedure is repeated as many times as necessary. By respecting this technique, we will avoid perforation accidents. Surgeons overestimating their capability are those who have accidents, that is not the case with those who recognize their limitations.

- Introduce Optics from the Cervix Towards the Uterine Fundus in Hysteroscopy During the Exploration
Correct: Always Vision from the Fundus towards the External Part
Releasing uterine synechiae. Uterine synechiae must not be released using curettes. Uterine synechiae must be released using an adequate resectoscope for such circumstance during direct vision hysteroscopy, and it is much better to have appropriate scissors available.
Time for correcting cystocele during TOT suspension. Perform TOT (Trans obturator Tape) suspension not having corrected cystocele (19). Emmett needles must never pass through the obturator fossa for sling placement, without previously having corrected urinary bladder prolapse, since likelihood for having urinary bladder perforation is increased; also, it will be more difficult to establish the ideal stress aiming to suspend the ureterocele with a sling or a mesh in order to avoid stress urinary incontinence.
Fetus in transverse dorsal anterior position with premature membrane rupture. Transverse hysterotomy must not be done in those cases showing the fetus in a transverse position with its dorsal part facing forward and membrane rupture. The likelihood for failure when attempting fetus extraction is so high and the incision would have to be extended or another incision might be performed. The likelihood for tearing the uterine segment and hemorrhagic complications is much higher. There have been reported cases that ended in hysterectomy. The adequate procedure is to perform corporal hysterectomy.
Suprapubic amniocentesis in preterm pregnant women. Suprapubic amniocentesis must not be performed in preterm pregnant women. This procedure should be done using other approach and always under ultrasonography guide. If a suprapubic puncture is performed, the likelihood for premature membrane rupture is very high.
Forceps, vacuum, and cervical dilatation. Forceps or vacuum must never be used if the cervix is not completely dilated. The likelihood for the occurrence of cervical and segmental tearing is increased, and the baby may get hurt (20).
Forceps, vacuum, and pelvis. No instrument must be used (for delivery) if you are not sure the pelvis is gynecoid and there is no fetal-pelvic disproportion (20).
Breech presentation in a first-time mother. Breech delivery in a first-time mother must not be managed without proper assistance. Adequate assistance is necessary for performing the appropriate maneuvers. By this, we may obtain a less-affected baby.
Forceps type for each situation. Any forceps type must not be used for any circumstance. Each forceps type has its own indications. Simpson is for fetuses with molded head occurring in first-time mothers, Elliot is for fetuses with non-molded head occurring in multiparous women. McLean is a non-fenestrated forceps to be used with premature babies since it protects their head from contacting vaginal walls. Piper is for breech presentations in case of last head, and Kielland is a rotating forceps.
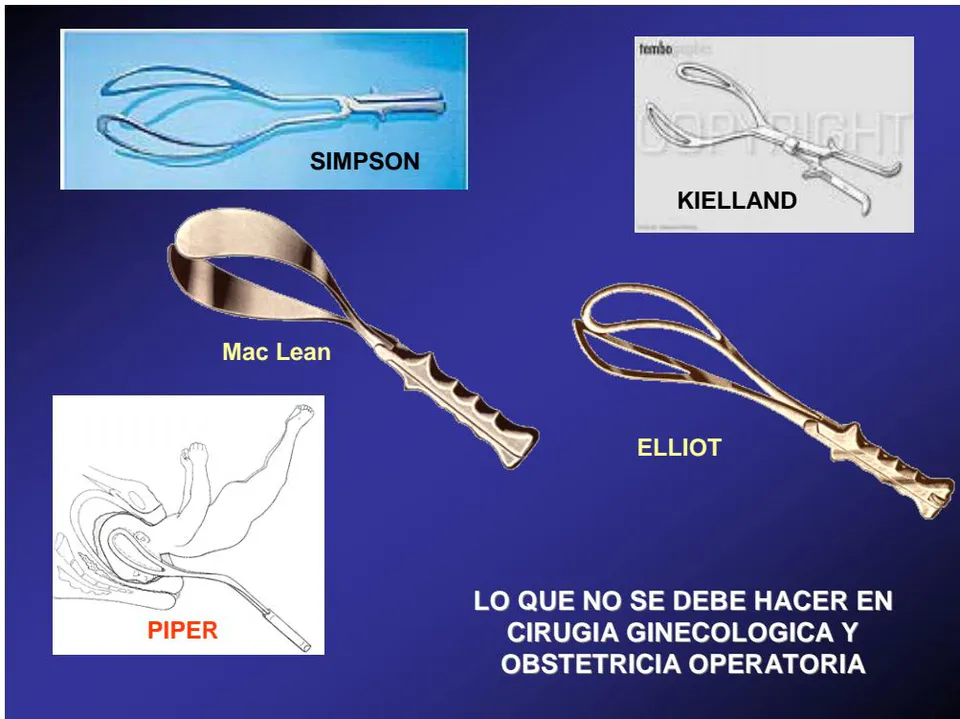
- Piper Forceps Placement. Piper forceps must never be used by a single professional. You must always
use this instrument with proper assistance. The technique for its use requires so (20).

Presence of an assistant: No gynecological examination should be performed without the presence of an assistant. By doing so, you may avoid any demand because of sexual harassment or the like.
Dressing style. No informal dressing should be used since this may lead to confusion and it may generate uncomfortable situations with the patient and/or her relatives. Gynecology and Obstetrics specialists must always dress properly, emphasizing their physician status.
Informed consent: Never miss explaining the procedure stating all its benefits and consequences; also, make the patient and her spouse sign the informed consent before performing any intervention (26), (27).
This compound may eliminate viruses, bacteria, and fungi.
- Personal protection equipment withdrawal: DO NOT FORGET that the moment with a maximum likelihood for transmission occurs when taking out the protective equipment, such as face protectors, gloves, coats, face masks, etc. (30).



