




I. INTRODUCTION
The first COVID 19 case was detected in Wuhan in December 2019, and COVID 19 was declared as a pandemic by WHO. COVID-19 is a disease caused by a new coronavirus called SARS-CoV-2. WHO first learned of this new virus on 31 December 2019, following a report of a cluster of cases of 'viral pneumonia' in Wuhan, People's Republic of China. (1). The effects of COVID 19 were profound calling for a Nationwide lockdown from 23 March 2020. This led to a disruption of essential health care facilities with only urgent/emergency health services being available for a quite a long time.
Criteria for Testing
i. A woman with respiratory illness with one of the following
ii. History of travel to abroad in the last 14 days
iii. Is a close contact of a laboratory proven positive patient
iv. She is a health care worker herself
v. Hospitalized with features of severe acute respiratory illness.
- In the reproductive period, non-inflammatory and inflammatory diseases of the lower genital tract, such as abnormal uterine bleeding and pelvic inflammatory disease, respectively, are common. Agynecologist's decision is fundamental in the definition of elective procedures that may be postponed depending on the general and clinical status of the patient and the availability of access to clinical treatment.
II. MATERIALS AND METHODS
A cross sectional observational case study of 20 gynaecological cases operated during the COVID-19 pandemic from a period of October 2020 to March 2021 at Grant Government Medical College, Mumbai.
III. RESULTS AND DISCUSSION
a) Distribution of cases as per age
| Age in years | No of cases | percentage |
| 15- 20 years | 1 | 5% |
| 21-30 years | 1 | 5% |
| 31-40 years | 4 | 20% |
| 41-50 years | 10 | 50% |
| > 50 years | 4 | 20% |
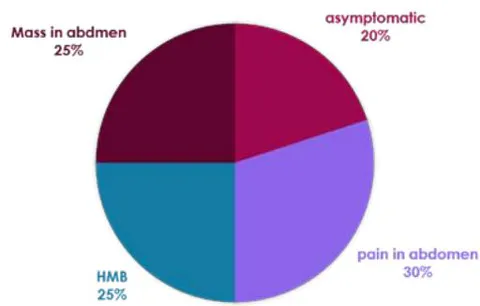
The most common complaint amongst the women who were symptomatic was b pain in abdomen in 30% of the cases. Around 20% of the cases were asymptomatic.
c) Distribution of cases as per Duration of presenting symptoms
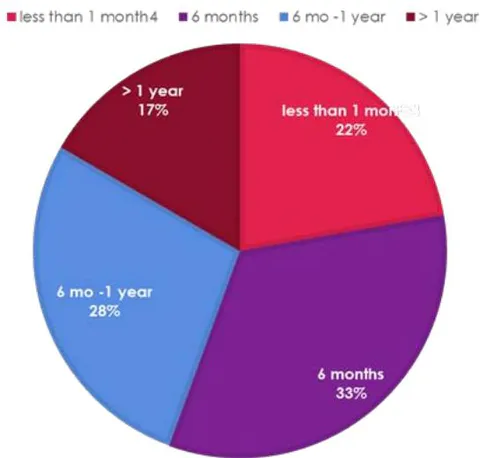
Most of the cases had a history of onset of symptoms for more than 6 months, the cause of it can be attributed to the lockdown and the non availability of elective services.
- The patients mainly presented with a chief complaint of abdominal distension, dyspepsia and pain in abdomen. Other presenting complaints included menstrual irregularities and menorrhagia and difficulty in micturition. The age group studied comprised from 25 – 65 years of age.
The patients belonged to upper and upper middle socioeconomic class and the patients presented from both urban and rural residential areas.
The ovarian tumors were huge with size ranging from 30 x 35 centimeters to 20 x 25 centimeters.
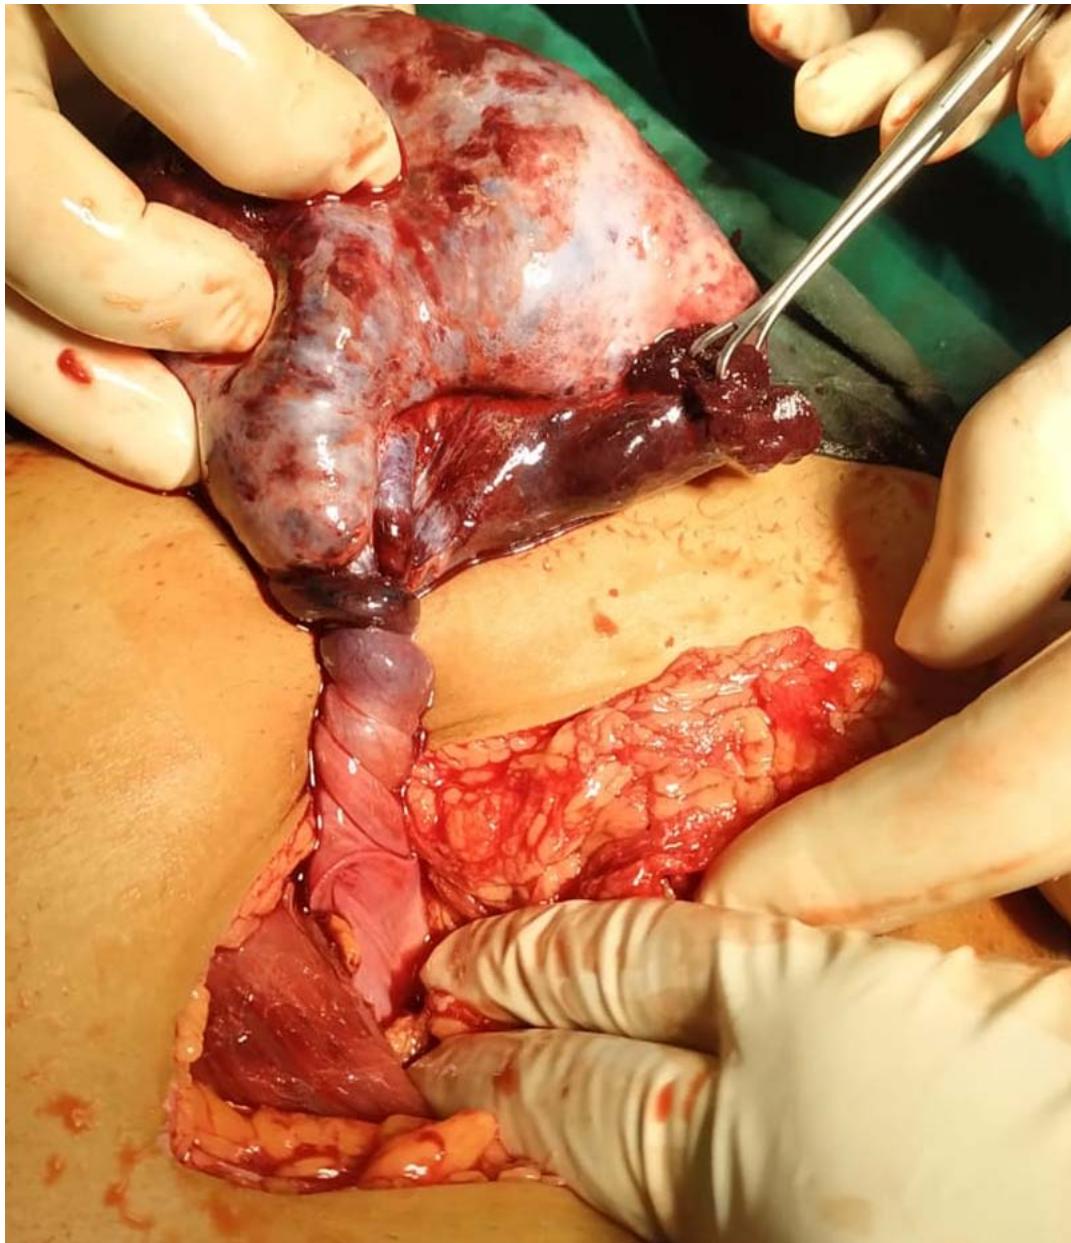
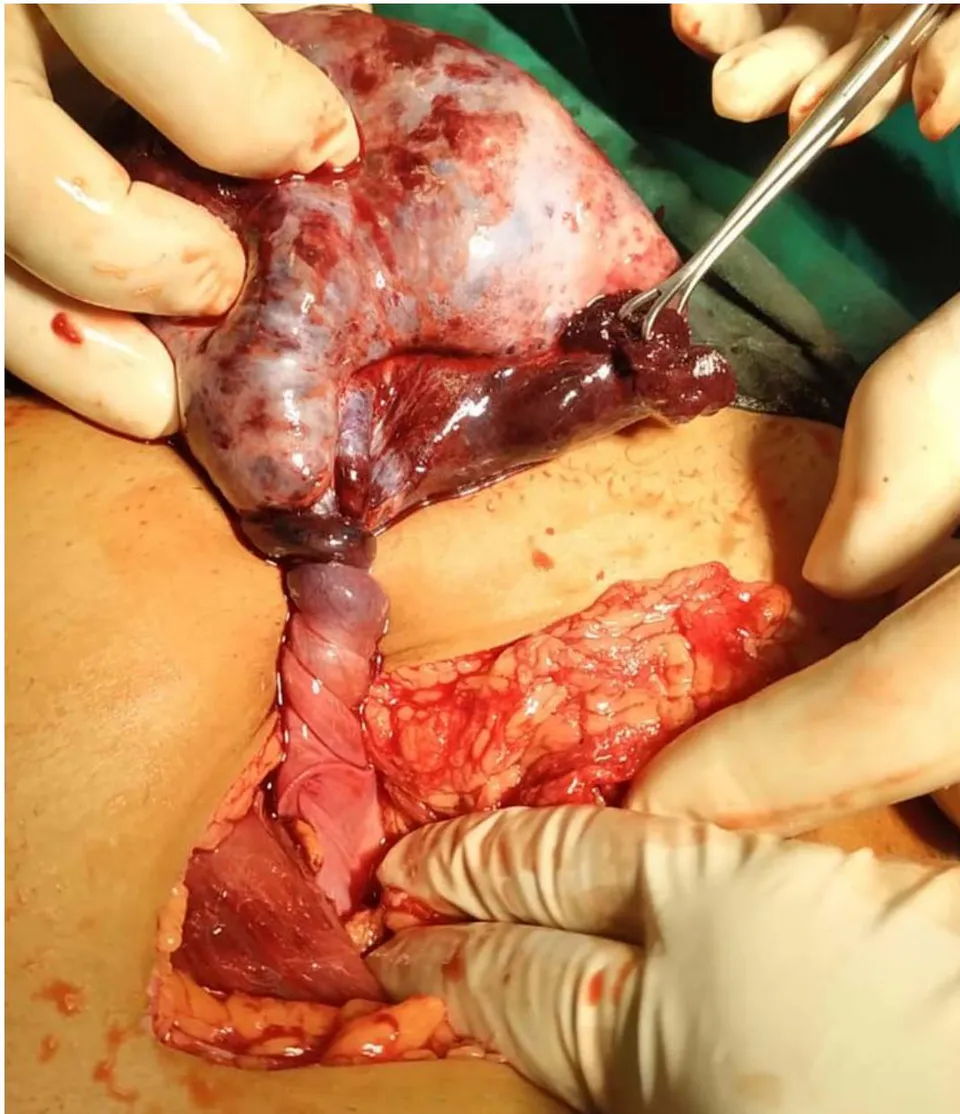
The tumors underwent torsion for more than 5 turns In most of the cases with onset of gangrenous ovary in some cases, however were managed with great surgical expertise and precision and timely intervention so as to minimize the intra-operative and post-operative complications.
The histopathological report included epithelial tumors like serous and mucinous cystadenomas and non epithelial tumors like granulosa cell tumors and fibrothecoma were mainly from the high income group.
The American College of Surgeons proposed stratification of surgical cases according to the patient's clinical condition and the severity of the disease as low, intermediate, or high severity.
Emergency (<1h): Peritonitis by tubo-ovarian and/or pelvic abscess, necrotizing fasciitis in surgeries for pelvic and breast neoplasms;
Urgent (<24h): Postoperative infections, acute inflammatory abdomen (adnexal torsion, myoma torsion, ovarian cysts), hemorrhagic conditions (ovarian cysts);
Elective urgent (<2 weeks): Surgeries for neoplasms of the lower genital tract and breast previously diagnosed by pathological examination;
Essential Elective (>2 to <3 months): Hysteroscopy for abnormal uterine bleeding (unknowledge causes, suspected malignancy, and menopausal transition), postmenopausal bleeding (suspected malignancy), cervical conization or looped electro excision procedure (to exclude neoplasm in the lower genital tract)
Non-essential/elective surgery: Infertility procedures, family planning procedures (bilateral tubal ligation procedure).
The protocol followed at our tertiary care institute before operating the cases were as follow-
All elective patients should be admitted to Transit ward initially. Swabs should be sent for all patients from there.
After swab reports patients should be segregated into Covid/Non Covid Category.
Covid POSITIVE swab patients should be transferred to COVID facility/Centre (St. George's Hospital).
COVID NEGATIVE Swab patients should be transferred to respective unit wards.
Repeat swab should be sent for these patients from their respective wards 72 hrs. before proposed surgery.
All patients should have at least two consecutive negative swab reports, of which the latest swab should be within 72 hours of planned procedure.
All OT Healthcare workers, patients and visiting relatives should be screened before entering OT as per protocol. If found suspect/symptomatic, should not be permitted to OT, and should be sent to designated swab collection facility.
All OT Personnel should follow COVID sanitisation protocols on entry to OT with repeated handwashing, social distancing and adequate protective gear.
Visiting relatives of the patients should also have COVID Negative swab report prior to entry to OT/wards.
Re-evaluate admitted patients for signs and symptoms of COVID-19
Encourage Physical Distancing (maintaining distance of 6 feet)
There should not be any adjoining inhabited buildings within 20 meters
There should be separate changing rooms for male and female heath care workers with attached toilet and shower facilities
Ideally, independent changing rooms with toilet and shower facility should be there for doctors, nurses and support staff
There should be provision for opening the doors with feet or elbow without touching the handles
Non elective surgeries postpone – at least 4 weeks
The ovarian cases presenting to the gynecology is not new.
However during the COVID-19 pandemic a varied presentation was observed and hence demanded a study of such cases.
Some of the selected cases are mentioned as follows-
CASE 1
A Case of 30 years old, married since 14 years Parity 3, Living 3, who presented with acute pain in abdomen. Her Ultrasound Abdomen + Pelvis was suggestive of heterogeneous to isoechoic solid lesion in left adnexa measuring 10.8 x 1.3 x 5.1 cm with ovarian vein engorgement & displacing the uterus inferiorly. cystic areas seen within suggestive of neoplastic lesion On Examination, her general condition was fair, vitals normal, no pallor/edema/icterus, cardiovascular/respiratory system – within normal limits. On per abdomen examination, a 10x 8 cm hard, firm mass felt, irregular margins, lower border palpated, restricted mobility, generalised tenderness and guarding was present. On per speculum examination, white discharge was seen, uterus not felt separately from mass.
Tumor markers were sent: CA125 - 7.25, CEA-2.38, rest tumor markers-WNL
Contrast Enhanced Computed Tomography done on 11/2/2021 was suggestive of torsion of ovary along with part of fallopian tube.
On 13/2/2021, Patient was taken up for Emergency exploratory laparotomy done with ovarian mass excision. Frozen section was suggestive of germ cell tumor.
Histopathology was suggestive of mixed germ cell tumor (yolk sac tumor + dysgerminoma). Patient withstood the procedure well. Post operative monitoring done, followed by chemotherapy with Bleomycin + etoposide + Docetaxel.
CASE 2
A case of 37 years old, unmarried, nulligravida with right tubo-ovarian mass, with ventriculoperitoneal shunt, presented to outpatient department with pain abdomen, irregular menses.
On Examination, her general condition - fair, vitals normal, no pallor/edema/icterus, cardiovascular/respiratory system – within normal limits. On per abdomen examination, a mass of 30 weeks felt over abdomen, irregular margins present, firm to hard in consistency, immobile, local rise of temperature noted. ON Per rectal examination, firm, irregular mass felt
Her ultrasound Abdomen + Pelvis was suggestive of right ovarian mass of 14x 17 x 17 cm, in lower abdomen, and right adnexal region. The lesion shows spongiform pattern with multiple variable sized anechoic cyst interspersed with echogenic stroma, suggestive of right ovarian mass possibly neoplastic and right sided tubo-ovarian torsion.
Tumor markers- LDH - 1251 U/L, HCG - 1.5 MIU/ML, CA 125 - 233.3 U/ ML
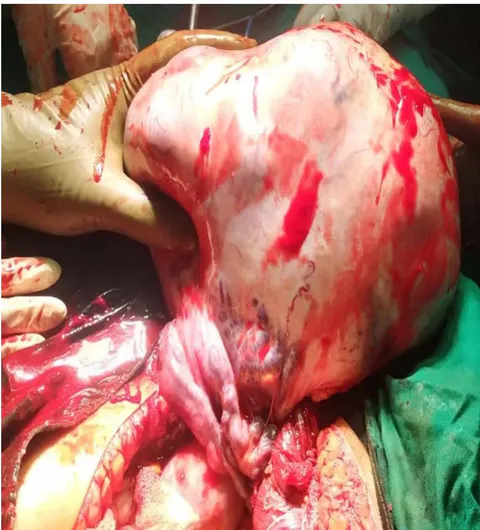
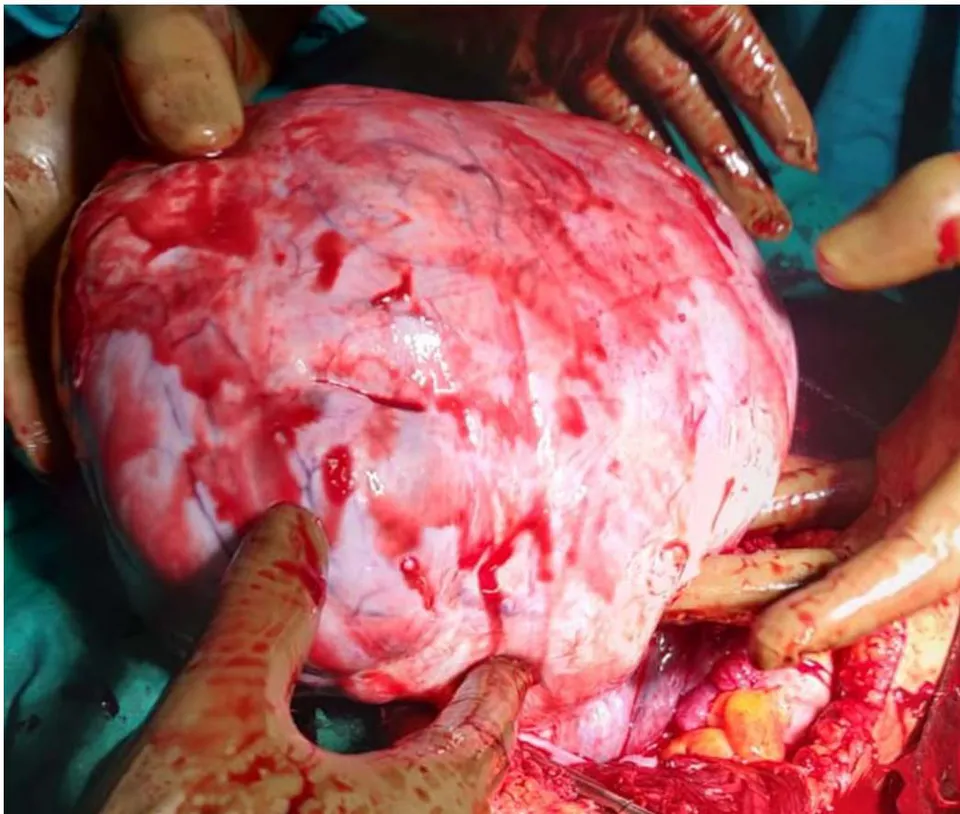
On 23/12/2020– patient underwent exploratory laparotomy with right ovarian mass excision. frozen sections was suggestive of granulosa cell tumor. Post operatively patient recovered well and discharged after suture removal. Histopathology report suggestive of granulosa cell tumor.
CASE 3
A 60 yrsold, married since? years, parity 3, living 3, all normal deliveries, tubal ligation not done, post menopausal since 10-15 years, came with complaints of pain abdomen in right side.
On examination: general condition fair, vitally stable, no pallor/ edema/ icterus, cardiovascular/ respiratory system – within normal limits On Per abdomen – soft, minimal tenderness over right iliac fossa noted. On per speculum – cervix was pulled up, atrophied. Per vaginally a cystic mass felt in the right fornix, mobile, non tender,? uterus,? right adnexal mass, cervix pulled up, deviated to the left.
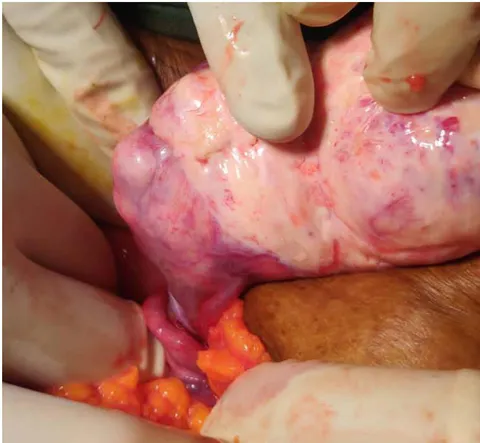
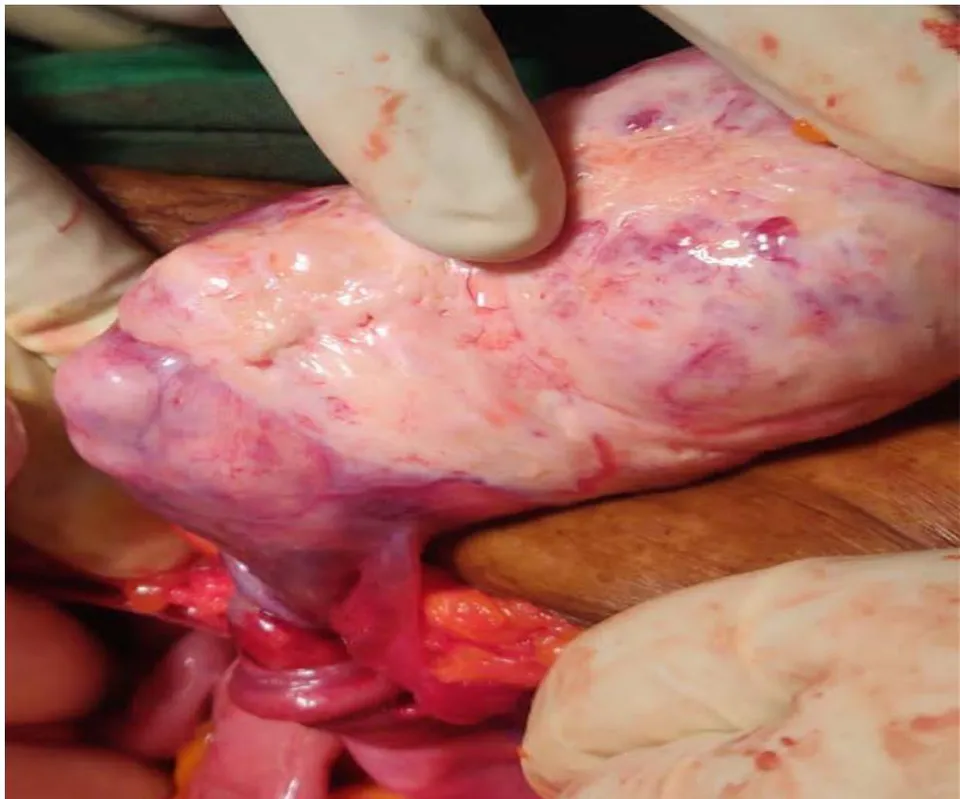
Tumor markers- ca 125 – 10.2 u/ml, LDH- 325 U/L, CEA – 1.9, beta hcg – 5.4, AFP – 13.
On 10/3/2021- Patient underwent exploratory laparotomy with total abdominal hysterectomy with bilateral salphingectomy with bilateral oophorectomy. Pt withstood the procedure well. post operatively patient was well. Histopathological report- sex cord stromal tumor, fibrothecoma.
CASE 4
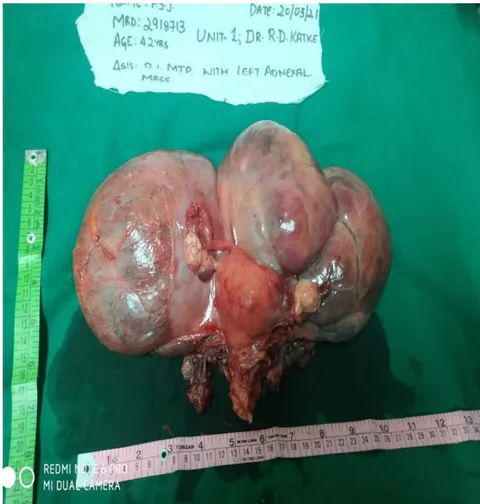
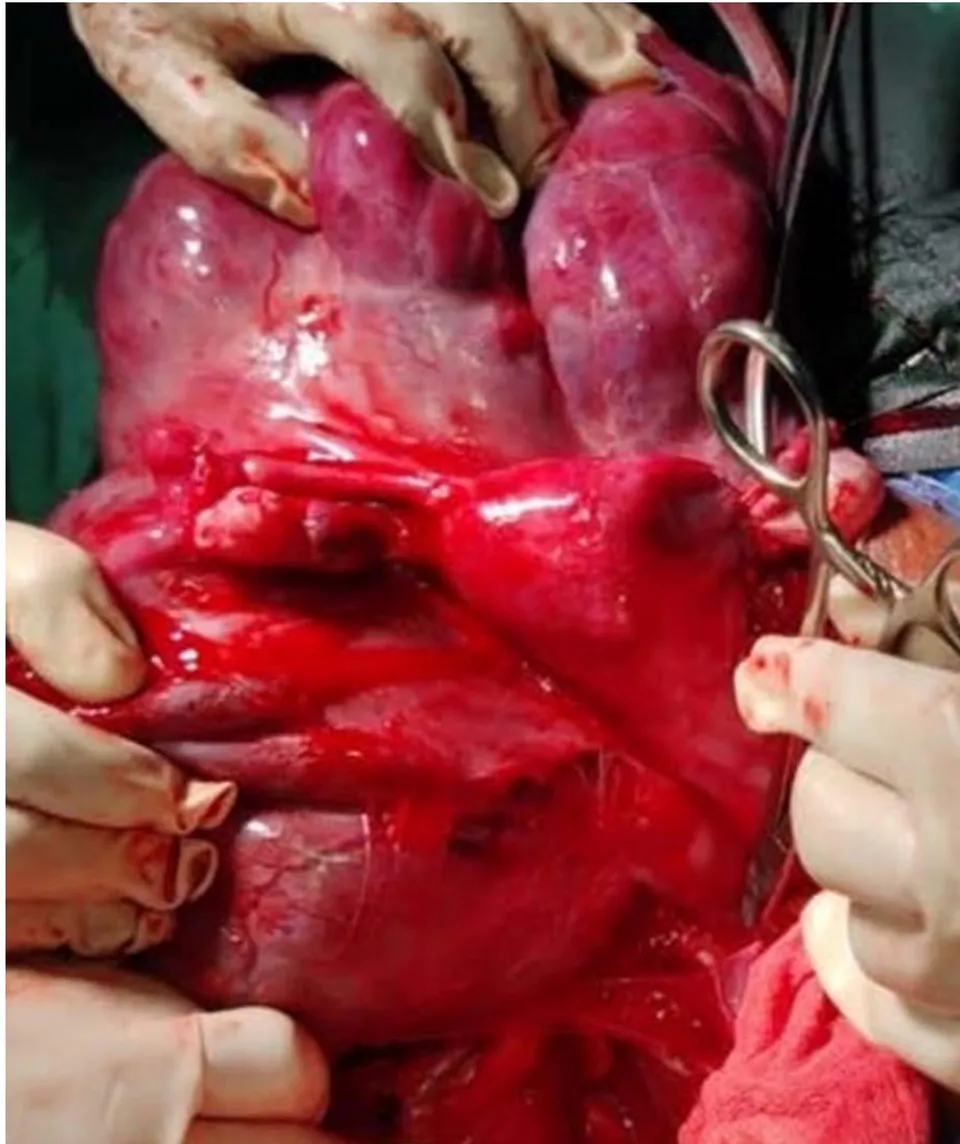
A 42 years old Parity 3, Living 3 with a huge mass in abdomen and pain in abdomen on and off since 1 year. on per abdomen examination a cystic mass of 10 x 15 cm in hypogastric region extending from umbilicus to lower abdomen, regular margins, mobility+, non tender. On per speculum examination, cervix was taken up. On per vaginum examination, a 22 weeks mass felt, cystic in consistency with mass covering the right iliac fossa, extending upto umbilicus, right fornix obliterated.
On 1/2/2021– Ultrasound (A+P) suggestive of 17 x 21 22 cms complex solid cystic lesion with septations, likely arising from ovary, likely malignant etiology.
Tumor marker were sent, B hcg 0.1, CA19.9-2.6, CEA 1.1, AFP 1.37, CA 125-1 On 20/3/2021, exploratory laparotomy with retroperitoneal mass excision with Total Abdominal mass excision with B/L salpingo-oophorectomy. Histopathology report suggestive of Spindle cell tumor with differential diagnosis being-
1. Low grade Fiboromyxoid Sarcoma,
2. PEComa,
3. Lymphangioeliomyomatosis
CASE 5
A 60 years. Parity 2, Living 2 came with complaint of pain in abdomen. On examination: general condition fair, vitally stable, no pallor/edema/icterus, cardiovascular/respiratory system – within normal limits On per abdomen examination a 24 weeks mass in hypogastrium, right iliac region, extending above umbilicus, regular margin, lower border felt, cystic in consistency, with restricted mobility felt. On per speculum examination, cervix pulled down and backwards. On per vaginum examination, uterus could not be felt separately.
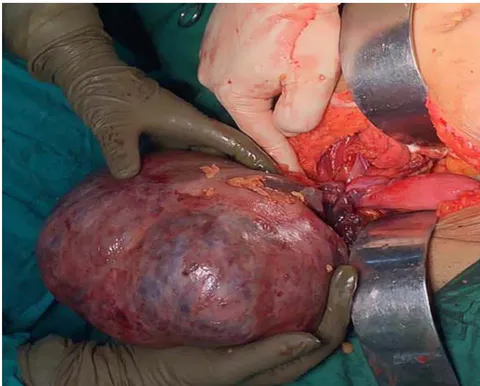
Ultrasound (Abdomen +Pelvis) suggestive of large multi loculated cystic pelvic mass, 13 x 15 x 18 cm, arising from pelvis, right adnexal or ovarian origin. Patient underwent exploratory laparotomy with Total Abdominal Hysterectomy with right ovarian mass excision with B/L salpingo-oophorectomy. Histopathology report suggested Haemorrhagic cyst–right ovarian mass
The unusual increased incidence of huge abdominal masses to our gynecological department raised a need to study the effects of lockdown. A similar effect of covid 19 pandemic leading to lockdown and inaccessibility of health facilities was studied that lead to a conclusion that although COVID-19 does not directly affect pregnancy outcomes, it has indirect adverse effects on maternal and child health. (2)
These patients have had complaints like pain in abdomen for more than a year, however due to non availability of certain facilities like limitation of transport facility, cessation of elective surgical procedures, conversion of hospitals to COVID designated centres, led to a decreased accessibility of immediate medical help to these patients.
As a result of which despite having symptoms they had a delay in the management of their cases. However administrative regulatory activities like lockdown were a need of hour in order to contain the rampant spread of the COVID -19 and reduce the morbidity and mortality associated with it.
The epithelial and non epithelial tumors showed a greater incidence of torsion of adnexal mass with tumor thereby leading to gangrenous and necrotic changes and an acute abdomen.
In the modern era of medicine, such huge mucinous ovarian tumours have become rare in the current medical practice, as most of the cases are detected early during routine gynaecological examinations or on ultrasound. However this was not the case during lockdown. Conservative surgery as ovarian cystectomy and salpingo-oophorectomy is satisfactory for benign lesions.4 Frozen section is very significant to know the malignant variation of this tumour and that helps in the management of the patient. As in the huge tumours, the anatomical planes get distorted, so the surgical expertise is required to prevent the complications (3)
Management of ovarian tumors depends on the patients age, the size of the cyst and its histopathological nature for large ovarian masses with a risk of malignancy and hence a staging laparotomy and intraoperative frozen section has their importance.(4)
The ovarian tumors both benign as well as malignant can undergo torsion and have been reported in numerous studies. Patient can present with acute abdomen due to torsion. In a case presenting with acute abdomen with lump abdomen, ovarian mass with torsion should be considered as differential diagnosis. (5)
The disruption of services has resulted into health being affected in all ways including family planning services. It has been studied that there is a huge unmet need of contraception available. Hence a proper mitigation of family planning is of utmost demand, although restraining of COVID 19 pandemic is also important (6)
IV. CONCLUSION
Although the measures like lockdown have been imposed for the containment of the COVID 19 infection, the increased cases of torsion of adnexal masses was reported in my experience. With proper management protocols and with all universal safety precautions the cases were managed with a great surgical expertise. Non epithelial ovarian cancers mainly granulosa cell tumours have excellent prognosis. Sex cord stromal tumours with an indolent course have good short-term prognosis, but with a greater risk of relapse.
More and more studies are needed to be devised to study their clinical presentations, course, prognosis and role of different adjuvant therapies. Such studies are required at an international level for increasing the disease free survival rates, reducing relapse rates and to decrease the morbidity and mortality associated with such rare ovarian cancers.
The management of such cases was challenging because the effects of COVID pandemic and effect of lockdown that restricted the availability and easy accessibility of health services thereby increasing the incidence of torsion of ovarian tumors.
Acknowledgements: None
Conflict of interest- NONE



