






I. INTRODUCTION
Diabetes mellitus (DM) is one of the important health problems affecting the major population worldwide. Diabetes mellitus is an endocrine disorder which involves multiple organ systems and leads to significant morbidity and mortality due to accompanying complications. Diabetes mellitus is characterized by absolute or relative deficiency in insulin secretion or insulin action or both, associated with hyperglycemia and disturbances in carbohydrate, lipid and protein metabolism.
Thyroid diseases and diabetes mellitus are the two most common endocrine disorders . Diabetic patients have increased prevalence of thyroid disorder, with hypothyroidism being the most common. In diabetic patients, thyroid dysfunction varies from 2.2% -17%.
Diabetic women are more commonly affected than men. Hypothyroidism is a clinical syndrome occurs from a deficiency of thyroid hormones. It is very common thyroid problem in diabetic patients. Thyroid hormones and insulin are the antagonistic, and involved in the metabolism of carbohydrates, proteins, and lipids. Thyroid hormone as well as insulin levels are altered if there is functional impairment of the thyroid gland and endocrine pancreatic beta cells. Thyroid disorders adversely affect diabetes control. Diabetes Mellitus appears to influence thyroid function in two sites; firstly, at the level of hypothalamic control of TSH release and secondly at the conversion of to in the peripheral tissue. Increased hyperglycemia causes reversible reduction of the activity and hepatic concentration of -deiodinase, low serum , increase in reverse and also variation in the level of .
Euthyroid Sick syndrome (ESS) or Non-thyroidal illness Syndrome (NTIS) identifies abnormalities of thyroid function tests observed in patients with systemic non-thyroidal illnesses and in those patients undergoing surgery or fasting. Abnormalities of thyroid function tests observed in ESS or NTIS includes 1) Low T Syndrome 2) Low T and T syndrome 3) High TT syndrome 4) other abnormalities like low TT and TSH, high TSH and low TT and TT .
Experiments on both animal and human models Diabetes Mellitus was found to be associated with alteration of thyroid hormone picture in absence of clinical thyroid diseases irrespective of the type of diabetes. In both type1 and type2 diabetes significant reduction of both TT and FT , increased rT and high rT /T ratio was demonstrated. Serum FT and FT I were normal, TT was normal or suppressed and TSH was found normal or slightly elevated. All the parameters of thyroid function specially TT , FT and rT become normal when euglycemia was achieved. More over it was found that reduction of FT and TT , rise of rT are significantly correlated with the severity of hyperglycemia and the thyroid secretory response to large dose of TSH is also declined in uncontrolled diabetes mellitus which frequently improves with improved glycemic control.
A previous study among young Bangladeshi diabetic population demonstrated significant alteration of thyroid hormone pictures in absence of clinical thyroid diseases which is consistent with the other study done in abroad earlier. But ESS or NTIS in the setting of type2 diabetes was not investigated extensively earlier and there is no available data regarding the changes in thyroid hormone pictures in patients with uncontrolled type2 Diabetes Mellitus among Bangladeshi population. Although there are few studies in abroad; which revealed that there are significant alteration of thyroid hormones in uncontrolled type2 diabetic subjects. As most of these studies did not exclude other causes of ESS or
NTIS which are responsible for activating inner ring deiodination or inhibition of outer ring deiodination of to produce from instead of ; the result was found to be poorly representative.
In the above context our present study was designed to document the changes of thyroid hormones pictures in absence of clinical thyroid diseases among Bangladeshi population in the setting of uncontrolled type2 diabetes mellitus.
II. OBJECTIVES AND METHODS
To evaluate the circulating thyroid hormone pictures in absence of clinical thyroid diseases among type 2 diabetic subjects in a group of Bangladeshi population.
III. METHODOLOGY
a) Types of study
This was a case and control study.
b) Place and duration of study
The study was conducted in the Endocrinology department of Sylhet MAG Osmani Medical College (SOMC) and Hospital, Sylhet, Bangladesh in collaboration with the Research Division, BIRDEM, Dhaka, Bangladesh during the period of January 2016 to December 2017.
c) Study population
A total of 100 type 2 diabetic subjects, 30-50 years of age, irrespective of glycemic status, duration of diabetes, BMI and sex were recruited from the outpatient department (OPD) of SOMC hospital and BIRDEM hospital. Prior to recruitment, diabetes mellitus was confirmed according to current American Diabetic Association (ADA) criteria for the diagnosis and classification of diabetes mellitus. Control subjects (n=100) were selected from friends and family of the patients within 5 years of age band without diabetes or impaired glucose regulation (IFG, IGT) determined according to ADA criteria and having no clinical thyroid diseases or other evident systemic diseases documented on clinical evaluation. Informed written consent was taken from all recruited diabetic and control subjects for the purpose of the study.
d) Exclusion criteria
Type 2 diabetes with acute metabolic decompensation.
Type 2 diabetes with clinically detectable thyroid diseases.
Type 2 Diabetes with clinically diagnosed other acute or chronic systemic diseases.
Diabetic subjects with overt nephropathy in which serum creatinine > 2mg/dl
Pregnancy and postmenopausal woman.
e) Method
Selection criteria as per availability and was given an appointment to come in a particular date. Preparation of the subjects and collection of blood of the Controls and diabetic subjects that were assigned for the purpose of study done according to the recommendation of the "Report of the Expert committee of the Diagnosis and Classification of Diabetes Mellitus." They were requested to fast overnight for at least eight hours and in the subsequent morning 16 ml of venous blood was drawn from the ante-cubital vein by using 25 cc disposable plastic syringe with 18G needle for the estimation of fasting serum insulin, C-peptide, glucose, HbA1c, TT3, TT4, FT3, FT4 and TSH. One ml of collected venous blood was taken in an anticoagulant containing vial for estimation of HbA1c. Remaining 15ml of blood was kept in 3 separate plain test tubes in equal amounts (5ml in each) to centrifuge immediately. Blood sample contained in the test tube was centrifuged for 15 minutes at a rate of 4000 rpm. A total of 200 μl of serum was collected in appropriately labeled eppendorf in duplicate with the help of micropipette for each of the biochemical parameters. Then the serum sample was preserved immediately at -30°C for analysis.
f) History and clinical examination
Detailed socio-demographic and clinical data were recorded in a pre-designed case record form. These include age, sex, residing area, occupation, socioeconomic status, dietary habit, exercise, alcohol and smoking habit, duration of diabetes, associated diseases like hypertension, obesity, dyslipidemia, coronary artery disease, cerebrovascular diseases, peripheral vascular diseases and crystal deposition diseases. Family history of these diseases were also been noted. Classical and non-classical features of diabetes mellitus and any adverse outcome of diabetes on life style was noted by taking history from the diabetic subjects.
Height, weight, BMI, waist circumference, hip circumference, waist-to-hip ratio (WHR), and waist-to-height ratio (WHtR) of all the controls and diabetic subjects were recorded. Percent body fat and total fat mass were measured by "Body Logic Body Fat Monitor; Omron Corporation, Japan". Systolic and diastolic blood pressure of all patients and control subjects was recorded. Blood pressure was measured using a mercury sphygmomanometer after at least 5 minutes of recumbence in a calm and quiet environment. A systolic blood pressure of 130 mm Hg and a diastolic blood pressure of 85 mm Hg was taken as the cut-off value for categorizing normal and abnormal values among diabetic patients.Diabetic neuropathy was tested by appropriate clinical tests. Autonomic function tests were done by documenting heart rate variability and blood pressure response on standing. Motor neuropathy was tested by eliciting jerks and reflexes with a percussion hammer. Retinopathy of all diabetic subjects was screened by routine dilated fundoscopy at the BIRDEM ophthalmology outpatient department and SOMC hospital outpatient department. For the documentation of nephropathy, urine albumin in mg/L and urine creatinine in g/L were estimated to calculate the albumin-to-creatinine ratio (ACR). FPG was measured by glucose oxidase method and HbA1c was measured by HPLC-based analyzer. Insulin, C-peptide, TT3, TT4, FT3, FT4, and TSH were measured by chemiluminescence technique in Immulite Auto-analyzer.
g) Statistical analysis
All the data were expressed as mean standard deviation, median (range) and/or number and percentage (%) as appropriate. Statistical analysis was done by using SPSS 7.5 packages for windows. Appropriate statistical test of significance like unpaired t test, one way analysis of variance (ANOVA) and Mann-Whitney test was used as necessary. P < 0.05 was taken as minimum level of significance.
h) Data presentation
Tabulation and/or drawing either in the form of graph or in the form of diagram were utilized as necessary for data presentation.
IV. RESULTS Table-1: Demographic status of the study group In table-1 shows demographic status of the study group where mean±SD age of the control and diabetic subjects were and respectively. Duration of diabetes is one month to six years. Systolic and diastolic blood pressure of the control and diabetic subjects were almost similar and it was within normal range. The table given below showed it in detail:
| Groups | Age mean ± SD | Annual Income Median (Range) | Family Member | SBP mean ± SD | DBP mean ± SD | Duration of DM, years |
| Controls (n =30)100 | 39.53± 5.24 | 120000 (30000-220000) | 6 ±1 | 120 ±23 | 80±7 | -- |
| DM(n=100) | 39.24± 5.79 | 100000 (20000-200000) | 6± 2 | 124 ±17 | 80±10 | 0.02(0.01- 6) |
| t/p value | u/p value | t/p value | ||||
| Cont vs DM | -.248/0.804 | 1114/0.32* | 1.1770/.241 | 1.177/0.241 | 1.101/0.273 | -- |
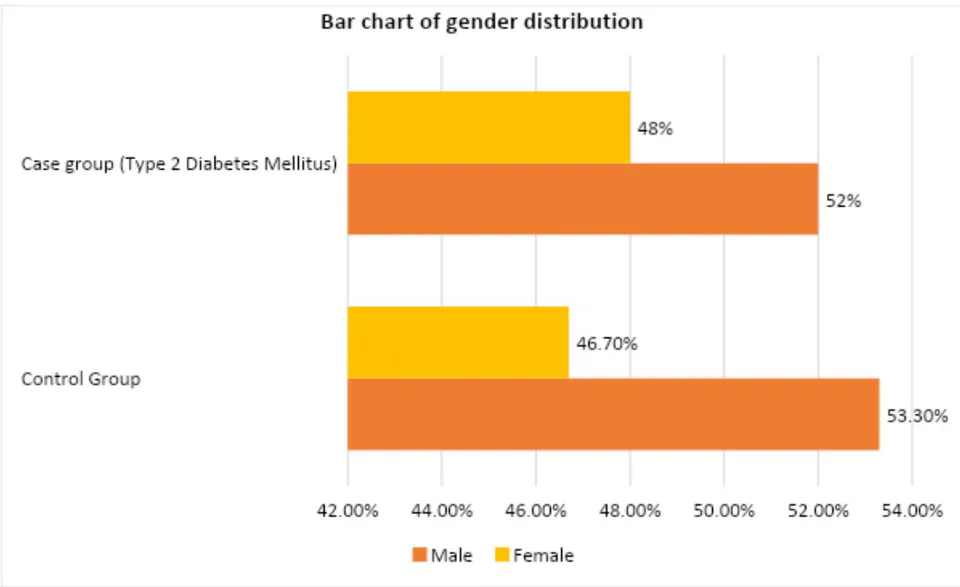
In figure-1 shows gender distribution of the study group where both the groups have shown in the figures in details. Male persons are 53/3% and females are 46.7% in controls and in type Diabetic group male patients are 52% and females are 48%.
| Clinical history | Controls | Type-2 Diabetes mellitus | |||
| Number | Percentage | Number | Percentage | ||
| Sex | Male | 53 | 53 | 52 | 52 |
| female | 47 | 47 | 48 | 48 | |
| Type of work | Sedentary | 90 | 90 | 84 | 84 |
| Physical work | 10 | 10 | 16 | 16 | |
| Exercise | Regular | 37 | 37 | 23 | 23 |
| Irregular | 63 | 63 | 57 | 57 | |
| No Exercise | 0 | 0 | 20 | 20 | |
| Smoking | Smoker | 7 | 7 | 20 | 20 |
| Non Smoker | 90 | 90 | 70 | 70 | |
| Past Smoker | 3 | 3 | 10 | 10 | |
| FH diabetes | Present | 53 | 53 | 65 | 65 |
| Absent | 47 | 47 | 23 | 23 | |
| FH HTN | Present | 50 | 50 | 48 | 48 |
| Absent | 50 | 50 | 36 | 36 | |
| FH obesity | Present | 44 | 44 | 46 | 46 |
| Absent | 56 | 56 | 54 | 54 | |
| FH CAD | Present | 27 | 27 | 24 | 24 |
| Absent | 73 | 73 | 52 | 52 | |
| FH CVD | Present | 24 | 24 | 27 | 27 |
| Absent | 76 | 76 | 50 | 50 | |
| H/O CAD | Present | 4 | 4 | 38 | 38 |
| H/O CVD | Present | 0 | 0 | 06 | 6 |
| Retinopathy | Present | 0 | 0 | 35 | 35 |
| Neuropathy | Present | 0 | 0 | 35 | 35 |
| Nephropathy | Present | 0 | 0 | 25 | 25 |
| Anti DM drugs | Present | 0 | 0 | 24 | 24 |
| Typical Symptoms | Present | 0 | 0 | 37 | 37 |
| Atypical Symptoms | Present | 0 | 0 | 63 | 63 |
In table-2 shows clinical status of the study group where 53 out of 100 controls and 65 out of 100 diabetics have family history of diabetes. Family history of hypertension was found in 50 out of 100 and 48 out of 100 controls and diabetic subjects respectively. Family history of obesity was found in 44% controls and 46% diabetic subjects. Around 27% of controls and 24% of diabetic subjects have family history of coronary artery diseases (CAD) and 24% of control and 27% of diabetic patients have family history of cerebrovascular diseases (CVD). Early retinopathy and neuropathy were observed in 45.5% and 36.5% diabetic subjects. Nephropathy was documented in 25 diabetic subjects.
| Parameters | Control | DM | P value | |||||||
| MC** | FC** | TC** | MD** | FD** | TD** | MCvs MD | FC vs FD | TC vs TD | MD vs FD | |
| 93.67±17.14 | 83.46±12.78 | 88.91±15.88 | 85.02±22.7 | 83.46±22.0 | 84.27±22.3 | 0.912 | 1.00 | -1.268/0.209 | 1.00 | |
| 8.54±1.9 | 8.07±1.31 | 8.32±1.64 | 8.22±1.90 | 8.63±1.69 | 9.26±9.44 | 1.00 | 1.00 | 0.54/0.589 | 1.00 | |
| 2.69±0.36 | 2.56±0.55 | 2.60±0.54 | 2.40±0.68 | 2.37±0.74 | 2.53±1.72 | 0.816 | 1.00 | 0.215/0.83 | 1.00 | |
| 1.49±0.21 | 1.37±0.23 | 1.43±0.22 | 1.43±0.18 | 1.31±0.27 | 1.36±0.25 | 1.00 | 1.00 | -1.35/0.179 | 0.065 | |
| TSH | 1.33±0.88 | 1.35±1.16 | 1.34±1.00 | 1.26±0.89 | 1.84±1.42 | 1.54±1.21 | 1.00 | 0.961 | 0.824/0.411 | 0.08 |
| Groups | TT3 | FT3 | TSH |
| Groups with Low level of Thyroid hormone | 58.46±12.32 | 1.31±0.44 | 0.50±0.49 |
| Groups with Normal level of Thyroid hormone | 93.81±16.91 | 2.53±0.59 | 1.50±0.86 |
| T/p value | -11.45/0.0001 | -6.83/0.0001 | -6.018/0.0001 |
(Results are expressed as mean±SD, p value was calculated using ANOVA Bonferrony, t/p value was calculated using unpaired 't' test)
Table-4 showed that the mean serum TT3 in patients with low T3 syndrome groups of patients and in patients with normal values of TT3 were and respectively which was statistically significant (p=0.0001) between the two groups. Mean Serum TSH level in low TSH group was and in normal TSH group was which was statistically different significantly (p=0.0001) from each other. Serum FT3 levels in low FT3 groups and normal FT3 groups of patients were and respectively which was statistically different between the two groups.
| Groups | TSH | FPG | HbA1c | S Insulin | Serum C-Peptide | ||||
| Group A, N=13 | 78.42±24.50 | 8.77±1.15 | 2.40±0.59 | 1.37±0.25 | 1.37±0.25 | 5.97±1.8 | 6±0.56 | 5.9 (3.5-12.5) | 0.88(0.11-5.1) |
| Group B, N=15 | 89.71±24.33 | 8.00±1.53 | 2.35±0.61 | 1.22±0.27 | 1.90±1.40 | 7.7±1.9 | 7.37±0.32 | 8.0 (3.2-16.3) | 0.71(0.12-2.1) |
| Group C, n=72 | 84.19±21.51 | 8.45±1.95 | 2.35±0.73 | 1.39±0.24 | 1.41±1.11 | 12.39±4.5 | 10.84±1.89 | 7.9 (19-48.9) | 0.74(0.06-3.6) |
| P value U/p value | |||||||||
| A vs B | 0.554 | 0.773 | 0.255 | 0.774 | 0.135 | 0.749 | 0.09 | 75/0.30 | 88.5/0.67 |
| A vs C | 1.000 | 1.000 | 1.000 | 1.000 | 1.000 | 0.000 | 0.000 | 343/0.13 | 392/0.35 |
| B vs C | 1.000 | 1.000 | 1.000 | 0.97 | 0.862 | 0.000 | 0.000 | 513/0.76 | 469/0.42 |
| Groups | Serum Insulin | Serum C peptide | FPG mg/dl | HbA1c% | TSH | |||||
| BMI A N=55 | 6.0 (1.9-38.0) | 0.74(0.06-3.62) | 11.77±5.18 | 10.35±2.63 | 81.45 ±20.70 | 8.51± 1.77 | 2.31± 0.68 | 1.41± 0.26 | 1.28 ±0.89 | |
| BMI B N=35 | 8.6 (2.3-48.9) | 0.76(0.12-5.11) | 9.66±3.79 | 8.83±2.01 | 89.54± 24.58 | 8.46± 1.78 | 3.02± 2.72 | 1.32± 0.26 | 1.78 ±1.51 | |
| BMI C N=10 | 14.9 (4.9-21.5) | 0.94(0.20-2.13) | 9.96±3.30 | 9.10±2.01 | 81.33± 20.62 | 7.74± 2.15 | 2.00± 0.56 | 1.29± 0.18 | 2.09 ±1.30 | |
| u/p value | P Value | |||||||||
| A Vs B | 710/0.036 | 811/0.21 | 0.108 | .013 | 0.285 | 1.000 | 0.164 | 0.721 | 0.160 | |
| A vs C | 140/0.014 | 219/0.30 | 0.761 | .399 | 1.000 | 1.000 | 1.000 | 0.651 | 1.000 | |
| B vs C | 120/0.13 | 172/0.93 | 1.000 | 1000 | 0.913 | 1.000 | 0.288 | 1.000 | 1.000 | |
Table 7: Glycemic Status and indices of obesity in patients with low
syndrome and in patients with having normal among the Diabetic subjects categorized according to BMI groups
| Groups | FPG | HbA1c | BMI | % body Fat | Total Fat Mass | Fasting Serum Insulin | ||
| BMI A | Low | 14.24±7.13 | 10.74±3.15 | 23.16±1.39 | 23.46±5.45 | 7.6 (1.92-18.3) | 7.6 (1.92-18.3) | |
| Normal | 1018±3.61 | 10.18±2.39 | 22.74±1.89 | 25.48±5.84 | 5.55 (1.9-38.0) | 5.55 (1.9-38.0) | ||
| t/p value | 1.96/0.064 | 0.721/0.474 | 0.813/0.420 | -1.210/0.23 | u/p value | u/p value | *281/0.44 | |
| BMI B | Low | 9.55±4.40 | 9.08/±2.41 | 27.19±1.25 | 33.31±4.83 | 8.0 (2.3-47) | 8.0 (2.3-47) | |
| Normal T3 | 9.70±3.68 | 8.76±1.93 | 27.33±1.45 | 3.72±5.82 | 8.8 (3.5-48.9) | 8.8 (3.5-48.9) | ||
| t/p value | -.094/0.925 | 0.380/0.706 | -0.233/0.817 | 1.146/0.26 | u/p value | u/p value | *99/0.72 | |
| BMI C | Low | 10.45±0.64 | 9.55±1.34 | 33.41±3.61 | 36.85±6.29 | 13.4 (5.3-21.5) | 13.4 (5.3-21.5) | |
| Normal | 9.84±3.73 | 8.99±2.54 | 31.63±1.60 | 37.30±4.10 | 14.9 (4.9-20.8) | 14.9 (4.9-20.8) | ||
| t/p value | 0.222/0.83 | 0.294/0.776 | 1.144/0.286 | -.182/0.901 | 0.335/0.726 | u/p value | *7.0/0.79 | |
| Groups | FPG | HbA1c | Fasting S. Insulin | BMI | %Body Fat | Total Fat Mass | |
| Low (n=27) | 12.57±6.44 | 10.16±2.89 | 7.7(1.9-47.0) | 25.11±3.35 | 27.37±3.74 | 18.12±5.93 | |
| Normal (n=73) | 10.21±3.63 | 9.52±2.32 | 8(1.9-48.9) | 25.41±3.45 | 28.72±6.83 | 19.14±6.13 | |
| t/p value | 2.30/0.024 | 1.572/0.119 | 972/0.92* | -0.384/0.702 | -0.856/0.394 | -0.753/0.453 | |
| Low (n=12) | 11.45±5.09 | 9.98±2.43 | 7.4(4.4-38.0) | 26.59±3.52 | 30.42±7.24 | 21.42±5.94 | |
| Normal (n=88) | 10.77±4,61 | 9.66±2.51 | 7.8(1.9-48.9) | 25.16±3.33 | 28.07±6.91 | 18.52±6.03 | |
| t/p value | 0.475/0.636 | 0.426/0.671 | 480.5/0.61* | 1.357/0.178 | 1.096/0.276 | 1.562/0.122 | |
| TSH | Low TSH (n=12) | 12.24±4.16 | 10.86±2.48 | 8.3(1.9-48.9) | 25.27±1.82 | 30.19±7.65 | 19.98±5.0 |
| Normal TSH (n=88) | 10.81±4.78 | 9.65±2.48 | 7.7(1.96-47.0) | 25.21±3.65 | 27.63±6.66 | 18.40±6.20 | |
| t/p value | 0.986/0.327 | 1.573/0.137 | 461.5/0.48* | 0.449/0.218 | 1.524/0.782 | 0.982/0.624 | |
12mmol/l" data-thumbhash="/fcBBoC0yPlqV4jFbFZnaYSW4JIMPtk=" style="display: block; width: 100%; height: 100%; object-fit: contain;" decoding=async height=468 loading=lazy src=https://doc.globaljournals.org/wict42_59969/ocr/images/derivatives/34/342316d4b695156c5fcbae146243c9df2d610cf2ce011cce316e77fd236bafb3.webp width=548>
V. Discussion
Some studies done earlier in abroad; the age (mean±SD) of type 2 diabetic patients who were participated in study was (47.5±7.4) years coincides with the fact that type 2 diabetes mellitus usually develops after the age 40 years. Where as in our study age (mean±SD) of the control and diabetic subjects were 39.5±5.2 and 39.2±5.8 respectively.
Thyroid hormones among control and Diabetic subjects was evaluated and it was found that the differences observed in serum thyroid hormones and TSH levels between controls and diabetic subjects were not statistically significant. When the thyroid hormones and TSH were reevaluated on the basis of BMI and HbA1c groups among the diabetic subjects, similar observation was noted (table 5 and 6). But when serum TT , TT , FT , FT , and TSH values of all the diabetic subjects were divided into two groups by applying the cut off values to each hormone into normal values of thyroid hormones group and TSH with low values of thyroid hormones groups and TSH among the diabetic subjects, 27 diabetic patients were found to have low TT below the lower limit of normal range than that of their normal counterpart which was significant at p=0.0001 level (table-4 and 8), 12 patients were found to have serum
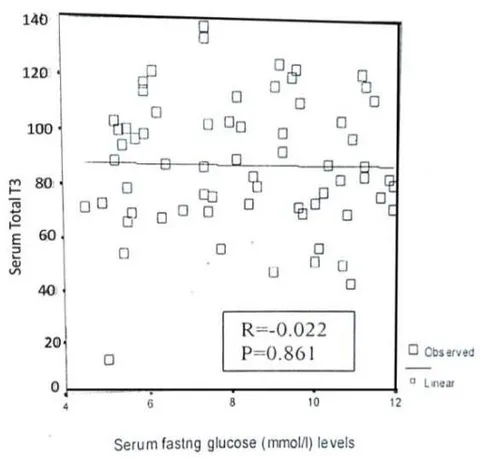
FT levels which was significantly (p=0.0001) lower than their normal counterpart groups. Again 12 diabetic subjects were found to have low TSH level than their normal groups. 4 diabetic subjects were found to have significantly lower serumTT when compare to normal TT groups. When the TT , FT , TT , and TSH groups were reanalyzed in relation to fasting serum glucose and HbA1c, low thyroid hormones and low TSH group have significantly (p=0.0001) higher fasting serum glucose and HbA1c than the groups with hormones within the normal range(table-8). The diabetic patients with Low TT showed strong negative correlation to FPG and HbA1c (Fig: 19, 20). This finding is consistent with the findings of the other studies done in abroad in both type 1 and type 2 diabetic subjects. . Our findings showed that around the level of 12mmoll of fasting serum glucose was associated with marked alteration of thyroid hormone picture in the blood in absence of clinical thyroid diseases. When low TT group was categorized according to BMI, diabetic subjects having BMI within normal range was found to have more deteriorating fasting serum glucose, HbA1c and serum TT levels; compare to other BMI groups (Table-8). This finding suggests that changes in thyroid hormone possibly much more obvious in young diabetic groups who are mostly have low or normal BMI than the type2 diabetic subjects that are mostly associated with obesity and higher degrees of BMI. These findings also supports the findings of the others study done in abroad. and also in the cell and molecular biology department of BIRDEM, Dhaka, Bangladesh. Our findings also conclude that BMI and other indices of obesity possibly have very little or no impact on serum thyroid hormones and TSH levels until and unless they are associated with very high serum fasting glucose levels beyond 12mmol/l.
VI. CONCLUSION
Uncontrolled type 2 diabetes mellitus is associated with alteration of thyroid hormone pictures particularly altering the TT , FT and TSH in absence of clinically evident thyroid diseases.
This biochemical feature is more evident if the BMI of the subjects is low or within the normal range, and it was also found that worsening glycemic status as determined by FPG and HbA1c levels leads to a more deteriorating circulating serum thyroid hormone profile and TSH.
Interpretation of abnormal thyroid hormone profiles requires a very high index of suspicion in patients with uncontrolled type 2 diabetes mellitus, as it was found to be associated with ESS or NTIS.
ACKNOWLEDGEMENT AND DISCLOSURE
I hereby acknowledge and express my honor and gratitude To Professor Hajera Mahtab, the supervisor of the research work, for her guidance, advise and contribution for selection of the title of the research work, designing of the protocol and all through contribution to complete the work.
To Professor Liaquat Ali, my co-supervisor of the research work for constant guidance, constructive criticism, developing scientific and research interest within me and also arranging the fund for completing the research work throughout the whole tenure of the work.
To Dr. Samira Jamal for data collection, data entry and compiling the data, preparation of the manuscript and all through contribution for the work.
To Sheikh Raihan for data entry, data compilation, data analysis and manuscript preparation during the whole period of the work.
Dr. Mohamed Emran for data collection, data compilation and preparation of the manuscript wholeheartedly throughout the work.
To Omar Faroque for giving all through for laboratory specimen collection, specimen preparation and preservation and finally laboratory analysis of all biochemical parameters throughout the whole period of the work.



