I. INTRODUCTION
Patients undergoing limb amputation surgery are at risk of postoperative pain. Phantom limb pain (PLP) is a painful sensation referred to the absent limb after amputation; but it's not limited to the extremities, phantom pain has also been reported after loosing almost any body part, for example, nose, tongue or breast.
The onset time of PLP varies from days to years, but it's common to be experienced between the first 24 hours to one week after amputation. In long-term studies, it's been observed a decrease in the frequency and duration of pain attacks over the years, which is accompanied by a decrement in its intensity, although in some cases, a worsening may occur.
a) Etiology and risk factors for PLP
Up to date, the exact reason that some patients develop PLP and others do not is unknown. It has been observed that its development is multifactorial, involving from peripheral, central and also psychological mechanisms. There is not a clear relationship between age or sex and the appearance of PLP in the literature, and it's more likely to appear when it's a bilateral amputation and how proximal it is.
There are studies about the influence of previous pain on an extremity as a factor for the development of PLP. There are reports that more than 50% of patients described PLP as similar to the pain they suffered before amputation.
At our country, type 2 Diabetes is the most common pathology causing amputation, referred as vascular diseases, it contributes to 81% of cases. On the other hand, traumatic amputations represent 16%, tumors, and congenital diseases account for 3%.
b) Pathophysiology
We may assume that PLP is an example of neuropathic pain since it occurs mainly as a result of an attempt to reorganize the nervous system followed by the deference of all sensory information involving amputation with nerve section.
There are three mechanisms involved: "peripheral" given by the massive lesion discharge and the loss of nerve impulses towards the spinal cord. "spinal" Experimental studies have provided evidence of structural, physiological and neurochemical changes in the deferential neurons of the medullary dorsal horn. And it also causes alterations in "central" processing like transneuronal changes at the level of the nucleus of the thalamus.
There are many pharmacological therapies to treat PLP once it appears, and some others are trying to prevent it, without consistent results that allow us to have a standardized treatment regimen. Madabhushi et al. Made a case report of a patient undergoing femoral supracondylar amputation, using bupivacaína (local anesthetic) and clonidine (α2 agonist) with excellent results, the patient didn't report any pain in the stump and neither PLP 12 months after surgery. There are also systematic reviews about the use of dexmedetomidine (α2 agonist) as an adjuvant to the local anesthetic for neuraxial and peripheral nerve blocks, to prolong the duration of analgesia compared to local anesthetic only. Cataloging Dexmedetomidine as a potential adjuvant and with more favorable pharmacodynamic and safety profile than Clonidine.
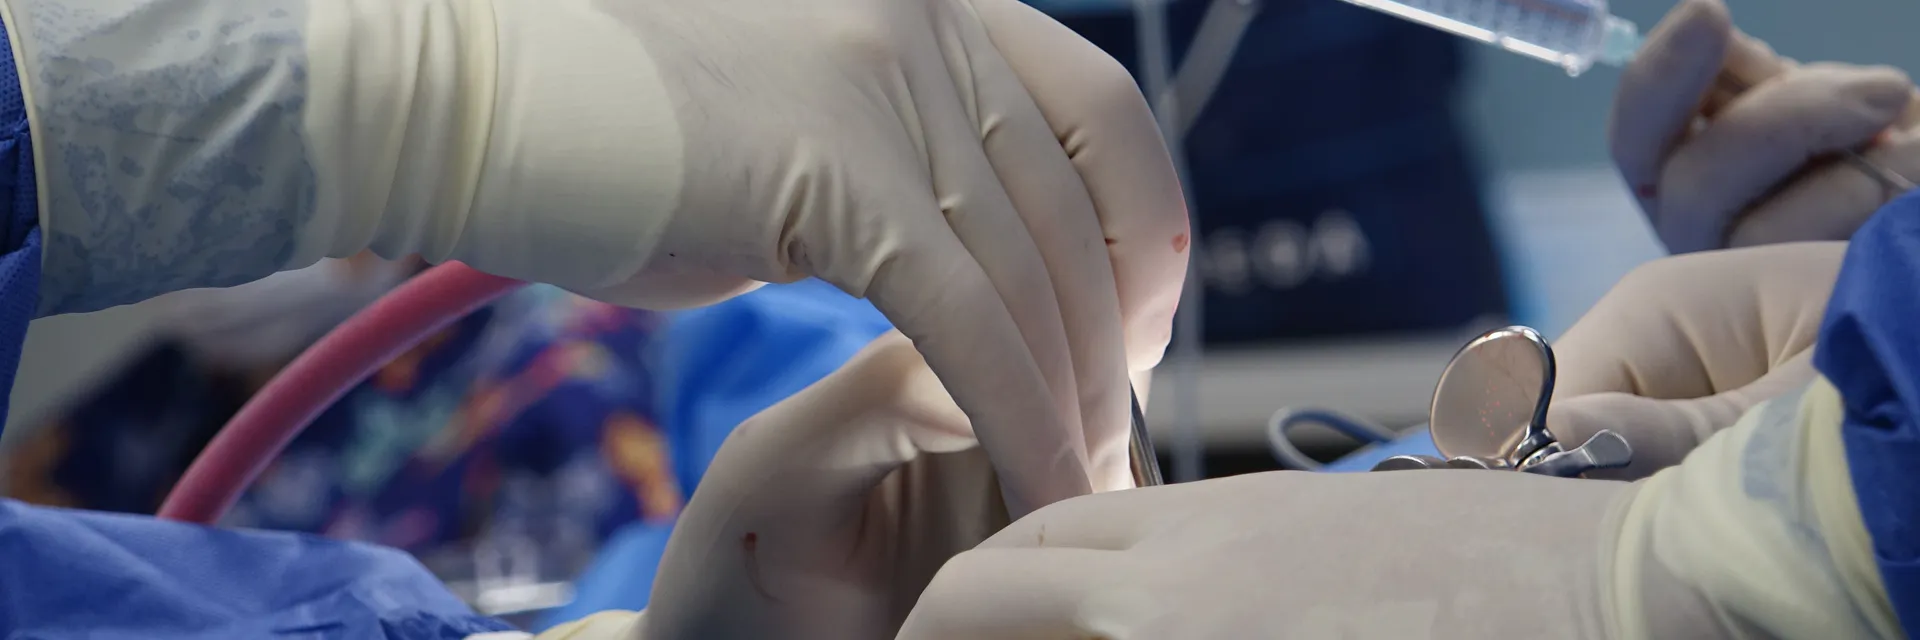
Due the incidence of chronic pain or symptoms related to phantom limb, which may determine disability, a very poor quality of life by the dependence on consumption of opioid and non-opioid analgesics or neuropathic medications to decrease pain, we proposed preventive analgesia in this case, consisting in the application of an anesthetic and analgesic before the surgical incision of the sciatic nerve with the mainly aim to reduce the magnitude and duration of acute postoperative pain and so, assess the appearance or not of PLP, which it implies a decrease in morbidity and improvement in the quality of life; benefiting the patient, family and health institutions.
II. MATERIALS AND METHODS
We carried out this study in Guadalajara's Civil Hospital "Fray Antonio Alcalde", México. Our study was a controlled, simple randomized, double-blind, clinical trial, conducted within a period of one year, from January 2018 to January 2019.
Inclusion criteria: Adult patients, scheduled for femoral supracondylar amputation, being due to traumatic cause, chronic disease and malignant tumor. Neuraxial block as anesthetic technique. American Society of Anesthesiologists's physical status I-III. With signed informed consent.
The exclusion criteria were: Refusal of the patient to participate, allergies known to any of the medications used, chronic hepatopathy disease, chronic renal disease, branch block or bradycardia and coagulation disorders.
III. RESULTS
During January 2018 to January 2019, there were included 30 patients (15 per group) scheduled for supracondylar femoral amputation at our Hospital, under the anesthetic technique of subarachnoid block and perineural block of the sciatic nerve, which met the inclusion criteria from the study.
According to demographic data, of the 15 patients in the RD group were 2 women (13%) and 13 men (87%) with a mean age of 57.4 years (SD 20.7). We classified them according to physical status in ASA Of the 15 patients in the RS group, were seven women (47%) and eight men (53%) with a mean age of 60 years (SD 17.4). We classified them according to physical status in ASA I: 2 patients (13%), ASA II: 1 patient (7%), ASA 3: 12 patients (80%), with the following diagnoses: diabetes mellitus 53%, arterial occlusion 33%, cancer 7%, fracture exposed 7%. (Table 1).
| Variable | RD Group. Ropivacaína + Dexmedetomidina.N=15 | RS Group. Ropivacaína + Solución Salina.N=15 | P (CI 95%) |
| (Mean ± SD) | (Mean ± SD) | ||
| Edad | 57.4 ± 20.7 | 60 ± 17.4 | 0.56 |
| Género | |||
| Masculino | 13 | 8 | |
| Femenino | 2 | 7 | |
| ASA | 0.83 | ||
| I | 1 | 2 | |
| II | 1 | 1 | |
| III | 13 | 12 |
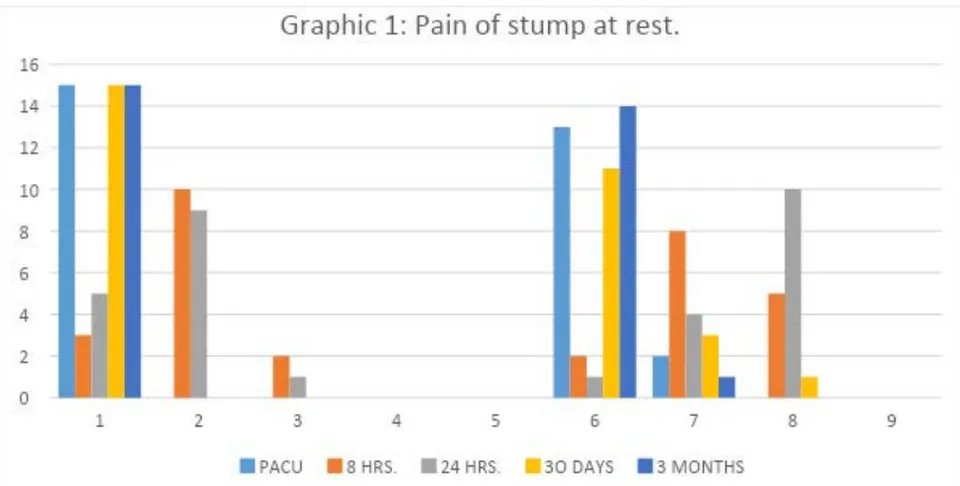
During the postoperative period, both groups were evaluated for pain intensity, both at rest and in movement, of the stump and phantom limb, from PACU, at 8 hours, 24 hours, 30 days, and up to 3 months.
| Variables | Evaluated Period | RD GroupN = 15 | RS GroupN = 15 | p (CI 95%) |
| Pain Level | (Main ± SD) | (Main ± SD) | ||
| Rest | PACU | 0 | 0.13 ± 0.35 | 0.143 |
| 8 hrs. | 0.93 ± 0.59 | 1.2 ± 0.67 | 0.426 | |
| 24 hrs. | 0.73 ± 0.59 | 1.60 ± 0.63 | 0.003 | |
| 30 days | 0 | 0.33 ± 0.61 | 0.099 | |
| 3 months. | 0 | 0.06 ± 0.25 | 0.303 | |
| Movement | PACU | 0 | 0.20 ± 0.41 | 0.068 |
| 8 hrs. | 1.40 ± 0.73 | 1.60 ± 0.73 | 0.066 | |
| 24 hrs. | 1.33 ± 0.48 | 1.73 ± 0.45 | 0.022 | |
| 30 days. | 0 | 0.33 ± 0.72 | 0.189 | |
| 3 months. | 0 | 0 | - |
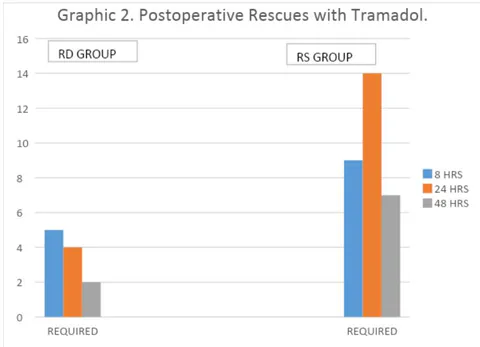
Pain values with VAS 4 and above, had the prescription of rescue with Tramadol at 1mg/kg. In the RD group, at 8 hours, five patients required Tramadol, at 24 hours four patients, and 48 hours 2 of them. In the RS group at 8 hours, nine patients were given tramadol rescue, at 24 hours fourteen patients, and at 48 hours, 7 of them. Then it is possible to demonstrate with statistical significance that the perineural administration of dexmedetomidine does reduce the postoperative opioid requirements. (Table 3, Graph 2).
| Variables | Evaluated period | RD GrupN = 15 | RS GrupN = 15 | p (CI 95%) |
| Tramadol rescue. | Percent. | Percent. | ||
| 8 hrs. | 33% | 60% | 0.143 | |
| 24 hrs. | 27% | 93% | 0.0002 | |
| 48 hrs. | 13% | 47% | 0.046 |
We evaluated the appearance of phantom limb pain at rest and movement, which was not reported by any patient of the RD group from the moment of evaluation at PACU up to 3 months of follow-up. It is worth mentioning that two patients of the RD group presented prior amputation, one by contralateral first toe, and another ipsilateral transtibial, none reported previous phantom limb pain.
From the RS group, up to 30 days, one patient reported mild phantom limb pain and one more patient moderate resting pain; on movement three patients reported mild pain at 30 days and only one patient mild pain at 3 months, who we referred to the Hospital Pain Clinic for evaluation and treatment. Without being these statistically significant values. (Table 4)
| Variables | Evaluated period | RD GroupN = 15 | RS GroupN = 15 | p (CI 95%) |
| Pain Score | (Main ± SD) | (Main ± SD) | ||
| Rest | PACU | 0 | 0 | - |
| 8 hrs. | 0 | 0 | - | |
| 24 hrs. | 0 | 0 | - | |
| 30 days. | 0 | 0.20 ± 0.56 | 0.343 | |
| Three Months. | 0 | 0.13 ± 0.51 | 0.309 | |
| Movement | PACU | 0 | 0 | - |
| 8 hrs. | 0 | 0 | - | |
| 24 hrs. | 0 | 0 | - | |
| 30 days. | 0 | 0.20 ± 0.41 | 0.068 | |
| Three months. | 0 | 0.06 ± 0.25 | 0.309 |
We decided to measure the possible side effects of perineurally administered medications on systemic blood pressure and heart rate in PACU, as well as the level of sedation (Ramsay scale) and oxygen saturation in PACU up to 24 hours after surgery.
About sedation in the postoperative care unit, we found significant difference (p < 0.025) with a higher degree of sedation in the RD group with an average of 2.8 on the Ramsay scale. 2.4 in the RS group.
We didn't find statistically significant differences in the values of systemic blood pressure, heart rate, and oxygen saturation after the intervention.
| Variables | Evaluated Period | RD GroupN = 15(Main ± SD) | RS GroupN = 15(Main ± SD) | p (CI 95%) |
| Mean arterial pressure (mmHg) | PACU | 82.9 ± 13.12 | 83.5 ± 12.04 | 0.341 |
| Heart rate (Bpm) | PACU | 75.2 ± 10.56 | 74.0 ± 8.4 | 0.555 |
| Pulse-oximetry (%) | PACU | 96.4 ± 2.02 | 95.7 ± 1.90 | 0.552 |
| 8 hrs. | 94.93 ± 0.96 | 95.33 ± 0.72 | 0.261 | |
| 24 hrs. | 94.86 ± 0.80 | 95.06 ± 0.59 | 0.057 | |
| Sedation (Ramsay) | PACU | 2.80 ± 0.41 | 2.40 ± 0.50 | 0.025 |
| 8 hrs. | 2.20 ± 0.41 | 2.00 ± 0.41 | 0.068 | |
| 24 hrs. | 2.00 ± 0 | 2.00 ± 0 | - |
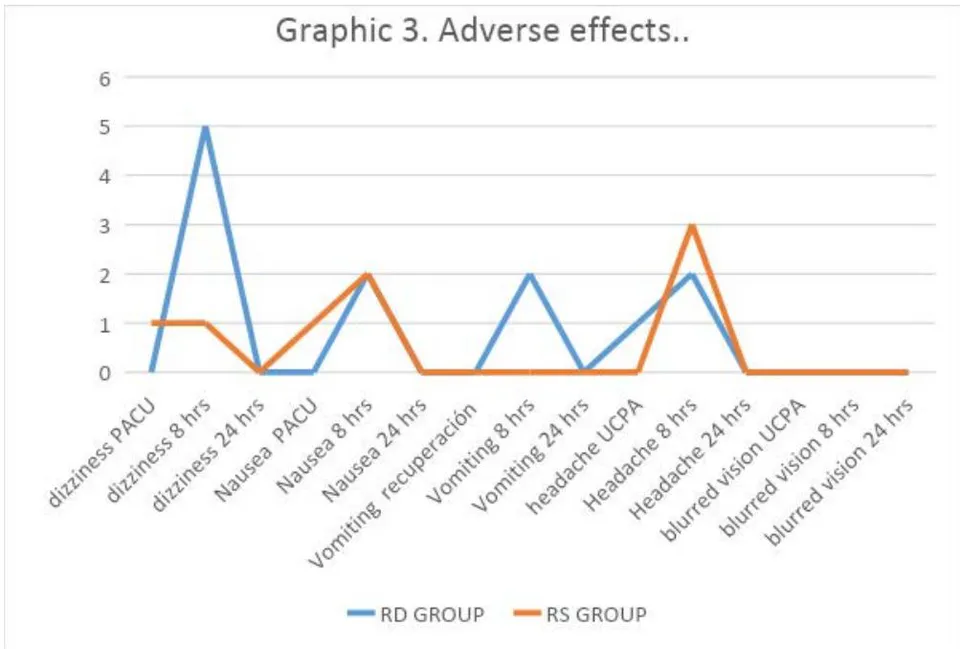
Of the possible adverse effects of the drugs used in our study, dizziness, nausea, vomiting, headache, and blurred vision were evaluated the first 24 hours after the perineural block. It was observed mainly in the RD group, dizziness in 13% at 8 hours, against 7% in the RS group (p = 0.068). Nausea in 13% at 8 hours in both groups. And headache 13% in the RD group against 20% in the RS group at 8 hours (p = 0.62).
However, we didn't find statistically significant difference for any of the adverse effects measured.
IV. Discussion
This study yielded significant data regarding the analgesic intervention of perineural infiltration with the combination of a local anesthetic (Ropivacaine) and an agonist (Dexmedetomidine) since in the published literature there are only isolated reports of clinical cases of this combination, but no clinical trials and much less meta-analysis; there are some others of perineural infiltration with local anesthetic without additive for the prevention of PLP, and other about the addition of an agonist for prolongation of peripheral nerve block, without assessing the impact on the prevention of phantom limb pain after amputation objectively.
Regarding the levels of postoperative pain, at 24 hours lower scores of pain at rest were found using the combination ropivacaine + dexmedetomidine (p = 0.003); However, both interventions evaluated in this study with infiltration of local anesthetic and its postoperative infusion by using an elastomeric pump were effective for pain management, coinciding with the study by Borgh et al. In which they conclude that the use of a prolonged postoperative perineural perfusion of 0.5% ropivacaine is effective therapy for the treatment of phantom limb pain.
Therefore, postoperative opioid consumption was also reduced as described by Bosanquet et al. in a systematic review and meta-analysis on the use of intraoperative placed perineural catheter with infusion of local postoperative anesthetic . In this case, for our study, the addition of dexmedetomidine to perineural infiltration had a statistically significant difference in the reduction of the use of rescue tramadol at 24 hours, compared with the use of only local anesthetic .
V. CONCLUSION
Phantom limb pain, associated with the amputation of a member of the organism, is a frequent complication after each procedure, sometimes reported with very high incidence rates.
In the understanding of the pathophysiology for the development of this neuropathic pain, there were proposed different interventions for its treatment, but few focused on preventing its onset. One of those proposals is perineural infiltration and continuous infusion of local anesthetic adding an adjuvant to mitigate peripheral sensitization in nociceptors at the medullary level and central de-centralization (cortex and thalamus) in a preventive manner, avoiding the development of the PLP, which once it appears is very complex to treat.
In this study, we corroborate and verified the advantages of doing a preventive intervention as described with a local anesthetic but adding an agonist, observing excellent results, and with no significant side effects.
Financial support and sponsorship
Nil.
Conflicts of interest
There are no conflicts of interest.