





I. INTRODUCTION
Staphylococcus aureus is one of the major resistant pathogens in clinical practice. Methicillin Resistant Staphylococcus aureus (MRSA) is defined as a strain of S. aureus that is resistant to a large group of antibiotics called -lactams, that includes penicillins and cephalosporins. The first case of MRSA was reported in Britain in 1961 and is now "quite common" in hospitals. Methicillin resistance in S. aureus is primarily mediated by overproduction of PBP2a protein, an altered penicillin-binding protein with lower affinity for beta-lactam antibiotics than PBP2, the main physiological methicillin target. PBP2a is encoded by the mecA gene, a component of a larger DNA fragment designated the mec region. Coagulase negative Staphylococcus (CONS) have been considered as non-pathogenic and were rarely reported to cause severe infections. However, with the increase in the number of hospitalized immunocompromised patients, CONS have become a major cause of nosocomial infection and they account for 9% of these infections.
There are many traditional and commercial systems for detection of MRSA in clinical microbiology laboratories. Until 2006, Oxacillin disc and agar screening methods were used for detection of MRSA, however, in January 2006, Clinical Laboratory Standards Institute (CLSI) recommended use of Cefoxitin 30 g disc as standard marker for MRSA identification. The shift towards use of Cefoxitin disc is emphasized because of its property to induce production of PBP2a in-vitro, thus it has better predictive value for detection of hetero-resistance in MRSA isolates. The gold standard method for antimicrobial susceptibility testing has been the minimum inhibitory concentration (MIC) test determined by dilution methods. In the recent years, MIC methods have been replaced by molecular methods which detect mecA gene as a gold standard for determining classical methicillin resistance in S. aureus. However, the use of molecular methods for detection of MRSA is largely restricted to reference laboratories and is not utilized in many microbiology laboratories as a routine test.
The aims and objectives of the study were:
- To detect the prevalence of Staphylococcus aureus and clinically significant CONS in various clinical specimens
2. Speciation of CONS
To isolate MRSA by easily available phenotypic methods: MIC level detection of Cefoxitin/Oxacillin, Disk diffusion of Cefoxitin 30 g disc and PBP 2a agglutination test.
To evaluate the sensitivity, specificity, positive predictive value (PPV) and negative predictive value (NPV) of these methods for identification of these strains.
Since PCR was not available for routine tests in the laboratory, MIC level detection of Cefoxitin/Oxacillin was considered as a gold standard.
II. MATERIALS AND METHOD
This prospective study was done in the Department of Microbiology in a tertiary care hospital in Delhi over a period of one year. Isolates of Staphylococcus aureus and CONS were collected from various clinical samples that were grown in routine cultures. The clinical specimens comprised of pus, blood, urine, high vaginal swab (HVS), body fluid, endotracheal (ET) tube secretion, discharge from eye and ear, joint aspirate and Central venous catheter line (CVP) tip. A total of 184 consecutive, non-duplicate, clinically significant isolates were collected for this study.
a) Bacterial identification and antimicrobial susceptibility testing
The clinical specimens were inoculated on 5% sheep blood agar and MacConkey's agar (HiMedia, New Delhi, India), incubated at C for 24-48 h, and examined for bacterial growth. The identification was done by manual as well as by Automated System (Vitek 2 Compact System, bioMérieux). Manual methods were based on colony morphology, Gram's stain, catalase test, mannitol fermentation, and coagulase test (slide and tube method). All the isolates were subjected to three methods of identification of methicillin resistance:
MIC breakpoints of oxacillin given by Vitek 2 Compact system or MIC level detection of Cefoxitin by E-test (Himedia). Staphylococcus aureus ATCC 29213 were used as control for MIC level detection.
Modified Kirby-Bauer disk diffusion method using Cefoxitin disks (30 g) on Mueller-Hinton agar (MHA). MHA plates were overlaid with clinical strain of the S. aureus with an inoculum of 0.5 McFarland turbidity standards. Cefoxitin 30 g discs were used and incubated at 35°C for 24 hours. Cut off zone diameters for Cefoxitin was according to CLSI 2015. For quality control, ATCC controls strains for MRSA and MSSA were placed on the same plate.
PBP2 Latex agglutination test. (Oxoid, ThermoFisher Scientific, Basingstoke, England).
b) PBP2 Latex Agglutination test
A loop-full of organisms was placed into a microcentrifuge tube with 4 drops of Extraction Reagent 1; the tubes were then placed in a heating block ( ), and after 5 minutes, the tubes were removed and allowed to cool to room temperature. A single drop of Extraction Reagent 2 was added to each tube, mixed well, and centrifuged at 1,500g for 5 minutes. The supernatant, 50 L, was used for testing with 1 drop of the latex particles. The supernatant and latex particles were mixed together with a stick, and the test card was rocked for 3 minutes. Tests were read visually. Agglutination of the test but not the control latex was considered positive, while no agglutination was considered negative.
The data obtained was recorded on Microsoft excel (2007 version) and analyzed. The results are explained in frequency (number) and in percentage (%).
III. RESULTS
Out of total 184 clinically significant, non-duplicate specimens, 150 (81.52%) isolates were Staphylococcus aureus and 34 (18.48%), were CONS. Among the CONS, the predominating isolate was Staphylococcus haemolyticus15 (44.12%), followed by Staphylococcus epidermidis10 (29.41%) (Fig1)
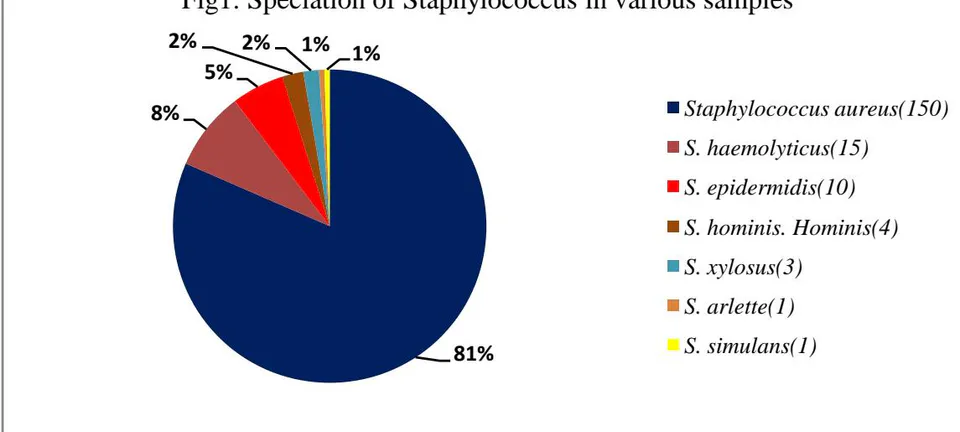
Out of total 184 Gram positive cocci, 104 (56.52%) were isolated from males and 80 (43.48%) from female patients. (Table 1)
Staphylococcus aureus strains were isolated from 106 (70.66%) indoor patients, followed by 29 (19.33%) intensive care unit (ICU) and neonatal ICU (NICU) patients. Among the clinically significant CONS, 23(67.65%) were isolated from indoor patients and the rest 11(32.36%) were from ICU and NICU patients. (Table1)
Table1: Distribution of isolates according to sex and hospital admission
| Isolates | Male | Female | ICU | NICU | Indoor | Outdoor |
| Staphylococcus aureus(150) | 84 | 66 | 16 | 13 | 106 | 15 |
| S. haemolyticus(15) | 8 | 7 | 2 | 4 | 9 | 0 |
| S. epidermidis(10) | 6 | 4 | 2 | 0 | 8 | 0 |
| S. hominis. hominis(4) | 3 | 1 | 0 | 2 | 2 | 0 |
| S. xylosus(3) | 3 | 0 | 0 | 0 | 3 | 0 |
| S. arlette(1) | 0 | 1 | 0 | 1 | 0 | 0 |
| S. simulans(1) | 0 | 1 | 0 | 0 | 1 | 0 |
| TOTAL(184) | 104 | 80 | 20 | 20 | 129 | 15 |
| Specimen Isolates | Pus | Blood | Urine | High Vaginal Swab | Body Fluid | ET secretion | Eye Discharge | Ear Discharge | Joint Aspirate | CVP tip |
| Staphylococcus aureus (150) | 86 | 45 | 9 | 4 | 1 | 2 | 2 | 0 | 1 | 0 |
| S. haemolyticus (15) | 9 | 4 | 0 | 0 | 0 | 0 | 0 | 0 | 1 | 1 |
| S. epidermidis (10) | 5 | 4 | 0 | 0 | 0 | 0 | 0 | 1 | 0 | 0 |
| S. hominis. hominis (4) | 2 | 2 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 |
| S. xylosus (3) | 2 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 |
| S. arlette (1) | 0 | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 |
| S. simulans (1) | 1 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 | 0 |
| Total | 105 | 57 | 9 | 4 | 1 | 2 | 2 | 1 | 2 | 1 |
| Phenotypic Methods | Result | MIC Level: Resistant | MIC Level: Susceptible | Sensitivity | Specificity | Positive Predictive Value (PPV) | Negative Predictive Value (NPV) |
| PBP2'a Latex Agglutination Test | Positive | 102 | 1 | 99% | 97.87% | 99% | 97.87% |
| Indeterminate/ Negative | 1 | 46 | |||||
| Cefoxitin 30 μg Disk Diffusion | Resistant | 99 | 0 | 100% | 92.15% | 96.12% | 100% |
| Susceptible | 4 | 47 |
IV. Discussion
Among the Gram-positive pathogens, S. aureus continues to cause skin and soft tissue infections (SSTI) in the community as well as invasive infections in the hospitalized patients. In our study, out of total 184 clinically significant, non-duplicate (except blood) specimens, 150 (81.52%) isolates were S.aureus. The most common clinical sample from which S. aureus have been isolated was pus or wound swabs 86 (57.33%). [Fig 1, Table 2] One similar finding corresponded S.aureus 165, out of which out of 131 (79.39%) were from pus samples. In a European survey, the most common organisms in skin and soft tissue infections (SSTI) were S. aureus (71% cases) with 22% being MRSA.
In a study from Germany, out of 1037 bacteraemic episodes in children over 10 years, Gram-positive bacteria accounted for two third of all episodes in paediatric patients. In another study from UK, out of 131 episodes of blood stream infection in a paediatric ICU over a period of 3 years, 63% was because of Gram-positive organisms. In our set up, bacteraemia due to Gram positive cocci have been isolated in 57(31%) cases over a period of one year which is corresponding with above mentioned studies. However, our finding is in contrast to one Indian study [7 (4.24%)].
Coagulase Negative Staphylococci (CONS) form a part of the normal commensal flora. To know the pathogenic potential, speciation of CONS is necessary. Out of total 184 clinically significant samples 34 (18.48%) were CONS. Among the CONS, the predominating isolate was Staphylococcus haemolyticus 15 (44.12%), followed by Staphylococcus epidermidis 10 (29.41%) [Fig1, Table 2]. This corresponds to other findings for S. epidermidis, 30.72% and 44.8% . Isolation rate of Staphylococcus haemolyticus 23.84% and 19.7% are not corresponding to our findings. Out of total 15 isolates of Staphylococcus haemolyticus, 9 (60%) isolates were from pus or wound swab, followed by blood 4(11.76%).[Table 2] This is almost similar to another study, Staphylococcus haemolyticus, 6 (13%) in blood and 7 (7.3%) in skin infection.
Our study shows isolation rate of MRSA by cefoxitin disc diffusion was 99 (66%).[Table 3] This is similar to the study done by R. Kaur in which out of 97 S. aureus strains, 53 (56.64%) were MRSA. The study done by INSAR also shows similar pattern of resistance, 42% in 2008 and 40% in 2009. The prevalence of MRSA varies between regions and between hospitals in the same region as seen in a study from Delhi, where the MRSA prevalence in nosocomial SSTI varied from 7.5 to 41.3% between three tertiary care teaching hospitals. The cause of varied prevalence rate of MRSA depends on multiple factors like proper sample collection, monitoring of infection control protocol implementations like hand hygiene protocol, barrier nursing or isolation policy, antibiotic policy of the hospital, prophylaxis policy protocol etc.
In our study, isolation rate of MRSA as per PBP2 a latex agglutination test was 102 (68%) [Table 3]; this is similar to findings of other studies, 42.4% and 45.36% .
In our study, cefoxitin disk diffusion test was found to have sensitivity 100%, specificity 92.15% and negative predictive value (NPV) 100%. [Table 3] This is similar to study (sensitivity 100%, specificity 96.23% and NPV 100%) but dissimilar to other studies (sensitivity 92% and specificity 98%) and (sensitivity 90.9% and specificity 98.2%).
Authors revealed in their study that low level Oxacillin resistance was detected better by Cefoxitin DD test.
PBP2a latex agglutination test was found to have sensitivity 99%, specificity 97.87% and negative predictive value (NPV) 97.87% in our study. [Table 3] This is in concordance with 97.6% sensitivity with this assay. In one study, the authors have mentioned PBP2a latex agglutination 100% correlation with the oxacillin MIC which is almost similar with our finding. Our finding is in contrast to another finding, sensitivity 100%, specificity 100% and NPV 100% .
LIMITATIONS OF THE STUDY
The limitation of the present study is that it mec A gene could not be detected among the isolates.
V. CONCLUSION
To know the prevalence of Gram positive cocci, Staphylococcus aureus along with MRSA in a hospital set up is an urgent need so that the spread of resistant strains can be controlled in that environment. Speciation of CONS, mainly in immunocompromised patients helps us to learn about diversity, epidemiological pattern and virulence. Correlation with patient's clinical status adds to the diagnosis. Proper quality control of the microbiological testing methods including Gram's staining to check the arrangements of Gram positive cocci, agglutination in coagulase testing, 0.5 Mac Farland Standard during Antimicrobial Susceptibility testing and measuring zone sizes according to CLSI guideline taking ATCC strains as control should not be subjective. Standardisation in each step can detect the resistant strains by these fast and effective methods which are easily available and applicable without having the facility of detection of mecA gene.
Conflict of interest: None



