
I. INTRODUCTION
Cerebral venous thrombosis (CVT) is a neurovascular emergency. It occurs about 1-2% causes of stroke. Its clinical presentation is non-specific, and often causes a delay in diagnosis. Headache is the most common onset symptom. This condition has benefited significantly from the development of CT and MR imaging techniques. MRI is the current gold standard imaging technique due to its high resolution and multiform contrast. MRI is not available in our developing country in terms of cost and coverage. CT is more available and stay on first line neuroimaging examination. It seems useful to use CT efficiently to not "miss" a CVT. The imaging examination must also consider the existence of possible risk factors amenable to etiological treatment at the same time as the thrombosis treatment. In this paper, we aim to remind semiology of headache in CVT, some risk factors, CT semiology, and some trap pictures.
II. Discussion
a) Headache in CVT
Most of the time, CVT occurs in young adults and females. Its clinical presentation is widely variable and non-specific, often causes a delay in diagnosis. Headache is the major onset symptom; 75 to 95% of lot of series [1, 2, 3, 4, 5, 6]. It may be the only manifestation throughout the disease. It is described as rapidly progressive but can be sub-acute (between two and 30 days) in 50%, acute (less than two days) in 30% or chronic (beyond 30 days) in 20%. The severity is variable but often moderate to severe, continuous, and often unresponsive to usual analgesics. Rough presentation "thunderclap" is also described. Headache is sometimes the only reason for admission into the emergency room. Sparaco et al. described it as typically severe and throbbing, with sudden onset, and non-remitting characteristics [4]. According to the IHS (International headache society) classification [7], headache caused by cerebral venous thrombosis has no specific characteristics: it is most often diffuse, progressive and severe, but can be unilateral and sudden (even thunderclap), or mild, and sometimes is migraine-like. Its pathophysiology lies in intracranial hypertension, venous distension, the venous infarction alone, or in association [2].
The headache could be associated with other symptoms such as coma, seizure, focal sign syndrome, intracranial hypertension. Tanislav noticed a strong association between headaches, seizures and CVT. Neurological deficit is another major symptom. These signs are not exhaustive. The paper of Ulivi et al. describes the clinical signs according to the affected venous structure .
b) Risk factors
Risk factors are numerous and meet Virchow's triad, an alteration of the venous wall, circulatory slowdown, and a thrombophilia condition. It is important, in real time imaging examination, to identify a regional risk factor such as cervical facial infection. It may be sinusitis, a tonsilar abcess, an otomastoiditis, facial cellulitis, a cholesteatoma etc. (figure 1). These infections must be considered as part of the thrombosis treatment. Anatomical and vascular relationship between sinonasal cavities and the endocranium on the one hand and neck spaces and the endocranium on the other are spreading factors of septic thrombosis in intracranial vein sinuses. Pregnancy and postpartum are frequent thrombophilia situation; unusual headache in these conditions must pay a special attention [6, 9].
The achievement of the superior sagittal sinuse seems predominant in most of series in the literature. And follow the lateral sinuse. Achievement of the deep veins and the cavernous sinuses is rare . Figure 1D shows thrombosis of the cavernous sinuses due to facial cellulitis associated with purulent eye and brain abscess in a young diabetic type 1 patient.
c) CT scan semiology
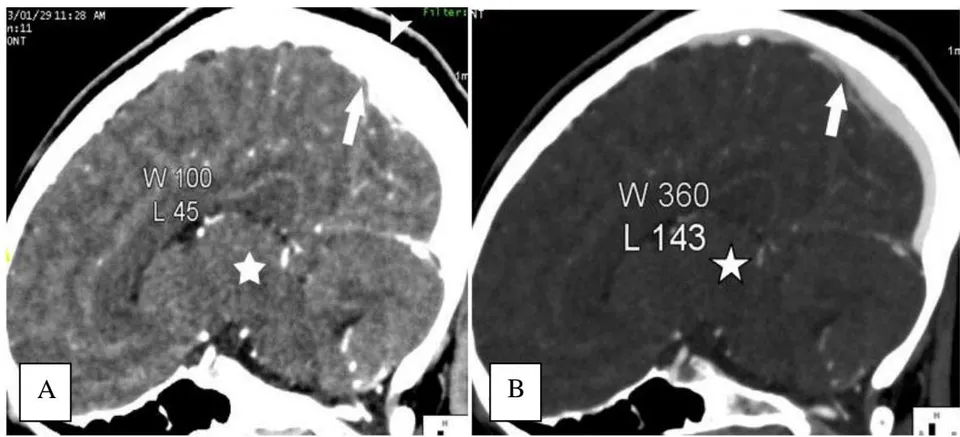
Post-processing images are more and more efficient and offer opportunities for multi planar reconstruction. Correct visualization of the venous sinuses requires a good window and level to dissociate the vein and parenchyma on the one hand and the sinuses and the vault of the skull on the other hand (figure 2).
i. Direct signs
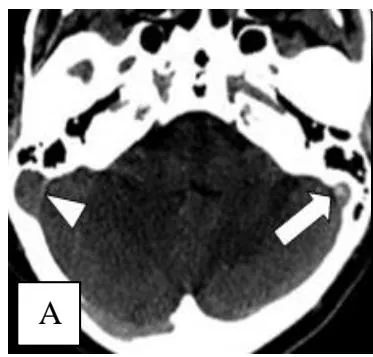
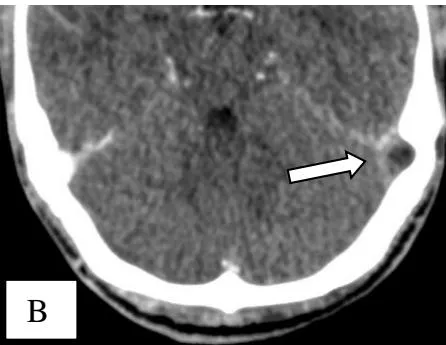
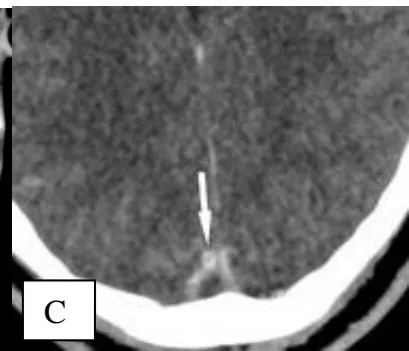
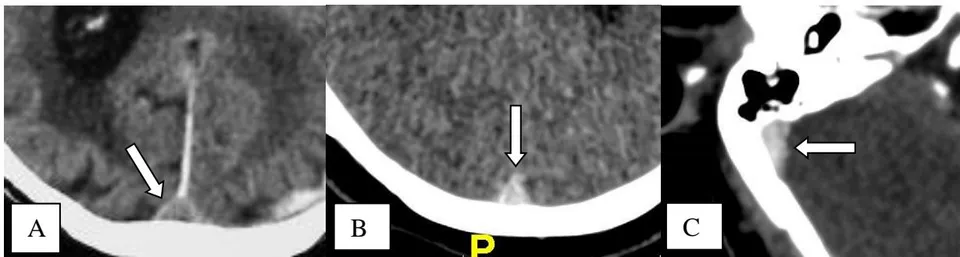
Hyperattenuating of the thrombosed sinus on unenhanced CT is the most important sign to look after (Figure 3A). It's due to the X-ray beam attenuation by the thrombus and gives to the sinus a triangular dense aspect (figure3B and 3C) and to a cortical vein a cord aspect called "cord sign". It is the protein fraction of the hemoglobin that is responsible for this hyperdensity. This aspect explains the possibility of spontaneous hyperattenuating in polycythemia or children without underlying thrombosis. And conversely, a thrombus can appear hypodense in case of anemia and induce a false negative [11]
Therefore, the objective measurement of density becomes of great importance in interpreting CT scan images. Linn et al. found mean values hyperdensity of HU and for sinuses and veins, respectively [10]. Garetier et al. report mean density values between 62.47 and 71.1 HU depending on the sinus affected [12]. Buyck et al. found an average density of HU.
Because of the hematocrit is directly related to the measured density of blood; Buyck introduced the H:H ratio (ratio between the density of the sinus and the percentage of the hematocrit). For an average density of 62 HU and a ratio of 1.52 the diagnostic efficiency of sinus hyperdensity is 95% and 97.5%, respectively [11, 13].
Can a thrombus be hypodense apart from anemia? Neal et al. recently reported an aspect of cerebral venous thrombosis with a hypodense thrombus without an underlying anemia for an acute cerebral venous thrombosis progressing for three days after onset. This observation underlines, in my opinion, the evolving aspect of the thrombus, which appeared subacute on the MRI data and very probably the relative delay of the onset headache .
Apart from the sinus content to analyze objectively, it's important to take into account the morphology of the thrombosed venous sinus. Normally triangular on a perpendicular slice (figure 4), it very often appears in event of thrombosis, enlarged with thickened hyperdense walls in addition to its content (figure 3B). After the injection of the iodinated contrast medium, the thrombus appears as an endoluminal defect surrounded by the contrast product and the inflamed and enhanced wall of the sinus (figure 3C).
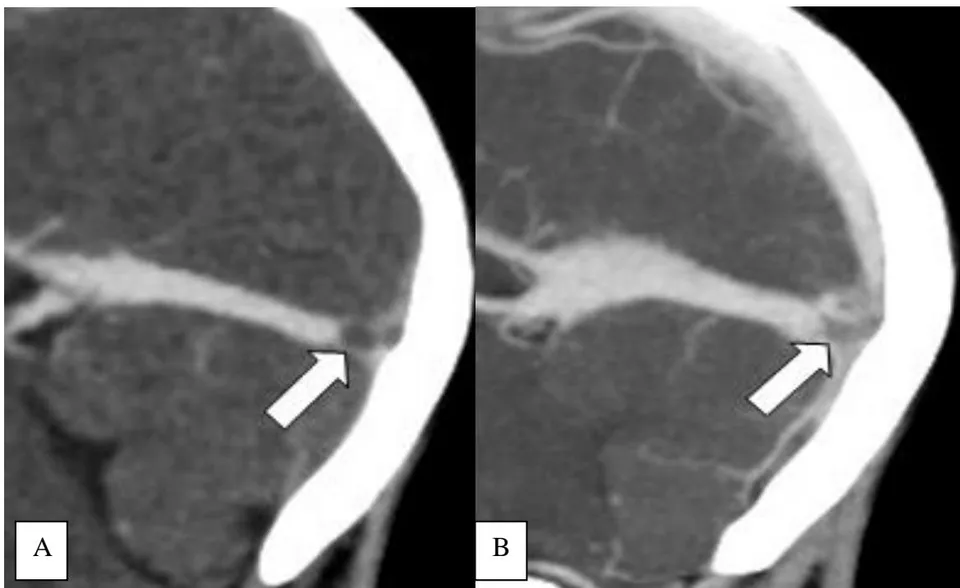
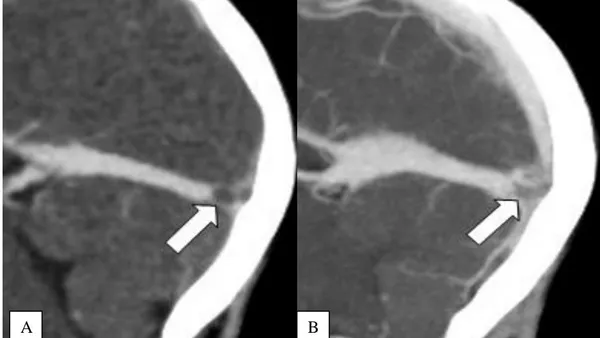
On miniMip (mini Maximum Intensity Projection) images, the thrombosed sinus appears with a circulatory defect (Figures 5A and 6A).
Parenchymal signs are important to consider but are non-specific such as subarachnoid hemorrhage, edema or, parenchymal hematoma [6, 10].
In summarize, hyperattenuating sign has reported with a high accuracy value (95%) diagnosis in acute CVT with the threshold of 62 HU, and increase to 97.5% when using the H:H ratio with the threshold of 1.52 [11]. Garetier et al. found that spontaneous hyperdensity had a high value of sensitivity, specificity, and negative predictive value (100%, 95%, and 99 to 100%) on the first two weeks after onset [12]. "Cord sign" has been reported to be insensitive [15]. Linn et al. reported that the sensitivity and specificity of attenuated vein signs are 100% and 99,4% respectively for the diagnosis of deep venous thrombosis less than for cord sign values; 64,6 and 97,2%. This study of Linn et al. evaluated the sensitivity and specificity value of non-contrast CT 93,7 and 98% [10]. On contrast-enhanced CT, the delta sign has been reported with a sensitivity of 73% [11]. Linn et al. [8] also demonstrate that multidetector CT venography had a 100% value of sensitivity and specificity in the diagnosis of CVT.
This, underlines the importance of this technique in our so-called "developing countries" where MRI is not available in terms of coverage and cost. If available, it should be the first-line examination if CVT is suspected.
The radiologist has important and exhaustive semiological data to integrate both clinically and radiologically (analysis of sinus morphology, sinus density, H:H ratio) to establish an evidence-based diagnosis and decide if the conditions allow him to continue his exploration by CT venography or MRI. This, would minimize the false negative rate estimated at 10 to 25% [16].
Given the importance of CT in the management of neurological emergencies, Kozic stressed the importance of training practitioners and trainers in neuroimaging to be able to detect early signs of CVT.
ii. Traps pictures
Provenzale et al. [15, 17] put a lot of emphasis on trap pictures. We just want to emphasize two points relating to our modest experience:
If a large thrombus cannot be missed, a very thin thrombus can be missed on multiplanar reconstruction (MPR) and mini-MIP images; it will be drowned by the contrast giving a false appearance of permeability of the sinus.
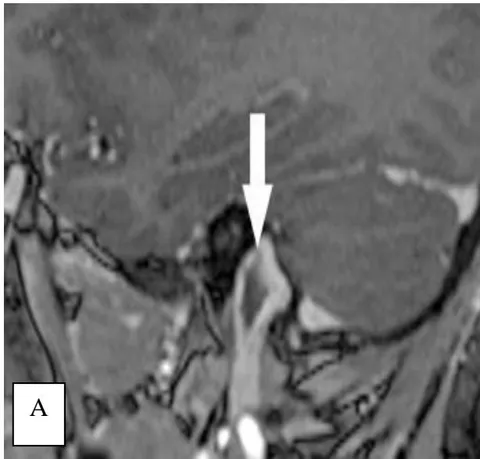
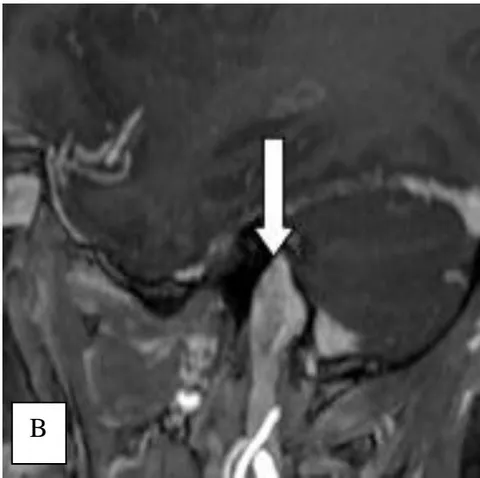
Secondly, the thrombus appears better defined on MPR images than on the miniMIP images (figure 5). Hence MPR images should be preferred for the diagnosis of CVT. Figures 5B and 6B show a thrombus embedded by the circulating part of the sinus and the inflamed and enhanced wall on Mini MIP images.
iii. Treatment of CVT
Treatment is mainly based on curative anticoagulation. Other therapeutic methods include an endovascular procedure (thrombectomy, endovascular thrombolysis), or neurosurgical procedure (decompressive craniotomy) and are part of a multidisciplinary management strategy [6].
III. CONCLUSION
CT scan (non-enhanced or CT venography) is an essential tool in neuroradiological emergencies. Its performance is sufficient in many cases to establish the diagnosis of CVT. However, MRI is more efficient and should be reserved in doubtful cases where it is available. The authors stress the importance of training practitioners to not overlook the diagnosis or conversely not to overdo it. Its management must be part of a practice of multidisciplinary consensus.
Conflict of interest: no