
I. INTRODUCTION
a) IoT in Healthcare
A step towards a sustainable healthcare system is the major concern of every government in the world. Currently enormous changes are occurring in this sector. Such nonstop changes as well as advancements demand an up to dated healthcare organizations with the medical information, organizational relationship as well as technological adoption. Stankovic (2014) argues that the better future of the healthcare sector is well enough blending with the globalization process. Even though the healthcare sector was highly evolving towards its advancement in the western world, about two centuries ago, still its advancement has just begun recently in the developing world. The public healthcare system is considered to be improved with the vast view of the sustainability of the population health. On the other hand huge portion of the healthcare sector in the developing countries is highly managed by private authorities.
The globalization of healthcare enables us with the lens to look at the future by two ways. First the economical globalization of the country helps to build up a better healthcare system as well as the infrastructure for a better mankind. Next, globalization of technological advancement in the healthcare sector through innovations from computerized machines to cloud systems. However the disadvantage is that the growing globalization had helped to make wealth distribution instead of solving the issues. Never less the increasing number of mobile apps and shortly of technology made the situation better by giving low expense technology sharing now than ever. The study by Lansisalmi et al. (2014) focused on the innovation in the healthcare system, where the need of adopting, generating, diffusing services as well as technological innovation in the sector as urgent. The study also indicated the major challenges for the growth of the sector including increasing number of elderly patients, retiring work force, cost efficiency as well as expectation of high quality care.
In general, innovation is defined as the introduction and application of processes, idea, products, and new unit of adoption within a group, role/organization which significantly benefit both individual and a group of society. Aalto and Ruoranen (2014) stated that innovation in the healthcare does not solely focus on innovation related to treating patients. It should enable the system to perform steadily as well as to improve work environment of the healthcare professionals (ex: data management tool, surgery assistance, training tools, alarm systems). According to Goyen & Debatin (2009) medical technology is defined as the equipment, procedures as well as the process by the means of medical care is delivered.
Healthcare innovations are numerous; the list is getting longer and longer for the betterment of the mankind. Even though the innovation in the healthcare can be viewed broadly, since this research's objective focused on IoT, the intervention of IoT in healthcare will be the subject matter. Since the final destination of the research is to understand the business applicability of IoT intervention on the healthcare innovation, this section will elaborate on the financial aspect of the healthcare sector. Sittig (2002) stated that continues intervention of technology innovation in the healthcare sector require higher cost. Even though majority of the countries allocate substantial amount of financial resources for heath care, still it seems insufficient. On the other hand, nerveless huge investments were taken place in some innovation of this sector where expected value is not delivered.
Healthcare innovation is highly expensive; mainly the medical technology becomes the dominant driver of the healthcare cost. thus the healthcare policy makers trying to overcome the cost-efficiency of the future advancement of healthcare. Lanseng and Andreassen (2007) stated nerveless some technology reduces the cost, they result in negative aisle on their long run. The cost efficacy issue still sustain even after the continuous effect of scientist, because the inability to take over previous technology that tend to be in the similar or lower cost in the real market. This issue with stand because the government cannot symbolize an operating system as out dated just there is a more expensive solution arrived.
Healthcare in modern era is more of a system that connects health technologies, services and application provided to public health. Ahokangas et al. (2015) offered 16 different scenarios for an individual connected health. According to them a connected health solutions attracts health professional to improve their attention towards public health. However this does not shows that all the implemented technologies will successes in healthcare sector, as there are many obstacles in the implementation and adoption in such technologies. On the other hand Atkins & Cullen (2013) stated that connected health become a central part in the healthcare delivery where patients will be able to access and control their own medical data.
b) Architecture of IoT in healthcare
Medical rehabilitation is referred as the healthcare services that help people who have suffered from injury or illness and enable to restore lost skills and to maximize the self-sufficiency. The smart rehabilitation based on IoT was introduced very recently mainly to overcome issues of scarce resource caused by growing aging population. Such concept can be viewed as a sub system of smart city (Nath, 2006).
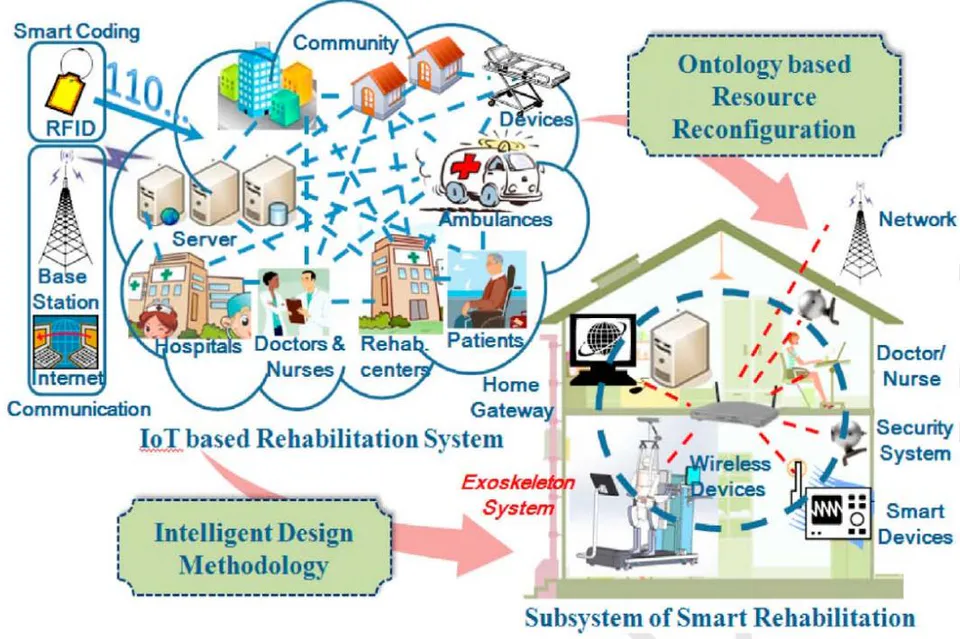
The IoT based healthcare system couples all the obtainable resources as a network to execute healthcare activities including monitoring, diagnosing and conducting remote surgeries through internet. Figure 1 implies on the frame work of the IoT- based rehabilitation system which extends the healthcare services from hospitals to homes (Le Gall, 2013). Wireless technology has been intragrated in the monitoring devices that act as a network manager of the system. As shown in figure 1 the centralized database is intragrates in a server that connects with all the available resources. An intermediary proxy involve in consolidation, data analysis, detection of critical events and responsible to create rehabilitation strategies. Finally an automated resource allocator act as identifier of solutions to meet specific requirement of individual patients of the network (Fan et al, 2014).
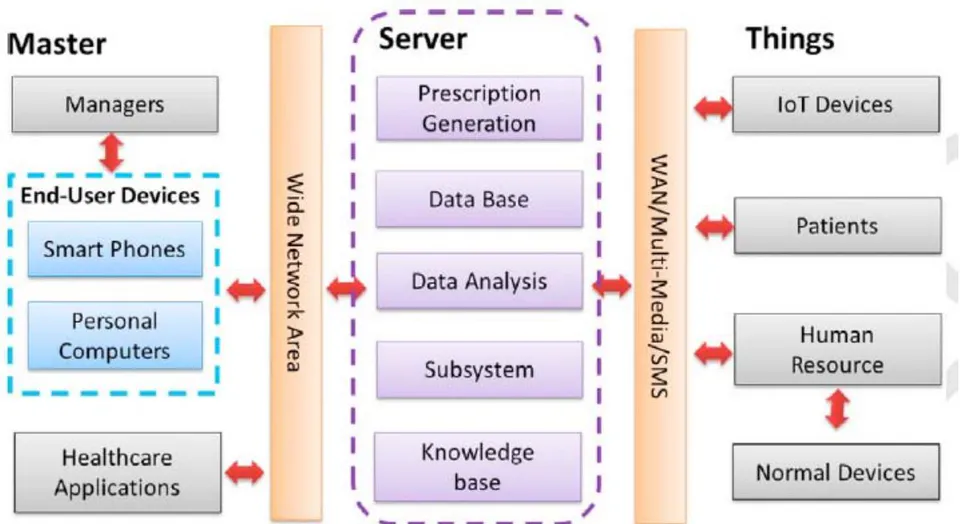
As shown in figure 2 the architecture of IoT based medical rehabilitation consists of 3 sections: Master, server and things (Feki et al, 2013). Master implies on people within the system who have specific permission to the system via the end-user devices, such users includes: 'Server' play the central role of the entire healthcare system, Its functions include data base management, prescription genentration, data analysis, knowledge base management as well as sub-system construction. 'Things' in the IoT paradigm refers to the physical objects that, via WAN, SMS and multimedia technology. Such objects include both patients as well as other human resources. This proposed architecture was verified and widely used in various study (Paré et al, 2010).
c) Electronic health (E-Health)
E- Health is wagly defined as a component of healthcare businesses over internet or as a new business model of healthcare using technology. Study by Orina et al (2005) provided 53 unique definitions as well as two universal themes such as health and technology, Even though the term 'Health' is presented in all the definition according to Orina et al (2005) only 21 out of 53 mentioned internet in its definition. Thus in addition to technology and health six additional themes where included in the frequently used definitions for e-health. There are commerce, stake holders, activities, places, outcome and perspectives.
Most of the definitions focus on the delivery of healthcare services while some centered on the expected outcome of the services. According to Pagliari (2005), e-health was defined with respect to its application as well as patients while other looks broadly in to its effect on all stake holders. However all definitions together substitute the idea of the impact of e-health in cost effectiveness and efficient service on time, with respect to emphasizing on the issue that e-health is not yet grown to take over conventional healthcare while it can assist the sector to move it further ahead through cohesive performance. On the other hand Norman & Skinner (2006) indicated even though western world have the ability to browse internet they lack the skill to utilize e-health platform. Thus with such existing skill gap it is difficult to understand the potential of E-health in up warding the public health.
d) Mobile Health
In recent decades numerous healthcare services have shifted toward patient centered care with main objective being quality of care (James & Harville, 2016). Historically disease centered care was followed where medical decisions with either limited or no patient involvement. In such model the communication between physician and patient is more of set of directives than a group decision on conversation with patient input. On the other hand patient centered care provides both input and inclusiveness to patient as well as family (Matthews, Rocchi, Wang & Gafni, 2001). Even though patient centered care model gives customer, service oriented enhancement, strategic application and confusion in definition due to lack of knowledge in medical terminology will have no real impact on care rather leading to perceived superficial efforts.
However, today the adoption of mobile communication technology and the concept of patient centered care becoming possible due to the progressive advancement of mobile application to both personal and population health management (Marufu & Maboe, 2017). Such new field of technology based patient centered care is known as mobile health (mHealth). The World Health Organization (WHO) defines mHealth as public and medical health practice aided by mobile devices, including mobile phones, personal digital assistants (PDAs), patient monitoring devices and other wireless devices.
Whereas mHealth Alliance has broadly stated that mHealth is either mobile based or mobile enhanced solution that can deliver health. They further said that high penetration of mobile devices in both developed and developing country enabled delivery of novel medical and health service to any point of globe (Serrano et al., 2016). Mobile applications are software programme that are specifically developed for mobile devices such as smart phone and tablets. In addition to mobile application (App), wearable activity monitors (WAM) are also included in mHealth. Today more than 400 WAMs are on market that can be worn on various body parts or clothing including wrist or pocket the most popular companies that currently offer these devices are Apple, Under Armour, Fitbit, Garmin, Pebble Time, and Misfit (James & Harville, 2015). mHealth is been wildly used to obtain primary healthcare, mainly in resource-poor areas to increase access to health services, like real time diagnosis, health education, data collection in disease surveillance and emergency medical response (Herrmann & Kim, 2017). mHealth is a easy accessible, low cost mechanism that act as a potential feasible solution to the healthcare needs of the population by creating quality healthcare more affordable as well as effective across the country.
e) Healthcare system in Sri Lanka
1) Physician recruitment and retention challenges in Sri Lanka
WHO defines doctor-population ratio as the number of doctors assigned for a specific group of population. According to WHO recommended doctor-population ratio of Sri Lanka, with reference to disease mobility and population density should be 6.2 per 1000 population (1 doctor for 150 persons). However the current estimated doctor -population ratio of Sri Lanka is 1.04 per 1000 population (1 doctor for 961 people) which is far below the global average (17 per 1000 population) and that of the recommended value. Also the specialist per 1000 population is very low as 0.04 (one specialist per 25000 people), (Ministry of Health, 2018).
As noted above up to date the demand for licensed physicians is high in Sri Lanka. According to Ministry of Health, Sri Lanka at least another additional 3500 doctors are need to fulfill the primary healthcare service of the country, However only 1200 doctors are able to graduate from Sri Lanka medical school and another 200-250 medical graduates return from foreign (Ministry of Health, 2018). Among the 1500 active registered doctors only 70% are employed under health ministry to practice as physicians and above in public hospitals. It was noted 15% of active registrants are migrating overseas each year. Analyzed data of last 10 years by Sri Lanka Medical Council confirmed these percentages are still applicable. Kessel et al., (2017) indicated doctors are migrating to more rewarding countries which offer better remuneration than Srilankan hospitals. No private medical college in the country also another contributor for the shortage of physicians. Thus the required human resources in the healthcare service are not fulfilled yet in Sri Lanka.
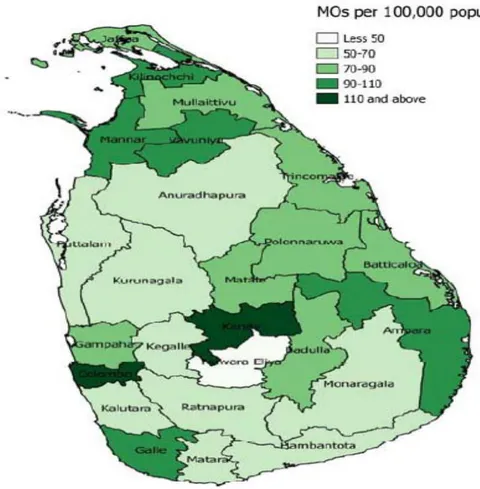
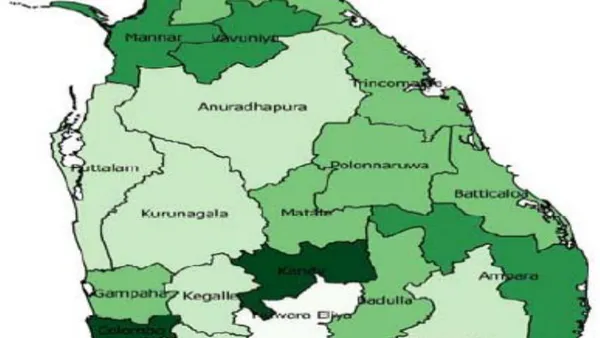
Shortage of doctors is a much critical issue where the crowded hospitals and long waiting list to seek doctors as well as less time spend for consultation are because of mal distribution of doctors. Statistical estimated by Sri Lanka Health Ministry showed that the capital of the country, Colombo (western province) enjoys 2.5 per 1000 population ratio followed by major cities including Kandy, Ampara and Galle (Ministry of Health, 2019). Whereas rural side of the country like Nuweraliya and Kurunagala recorded lowest value such as 0.37 and 0.5 doctors per 1000 population ratios respectively. Figure 3 indicates the level of distribution of physicians and other medical officers within the country. These concepts illustrate the need of more clinician in those regions as well as highlight the need to seek out alternative methods of healthcare, communication and access. One such alternative can be adoption of mHealth via IoT.
2) Healthcare system of rural population
Mobile technology is not always restricted to geographic boundaries and distances, neither weather nor traffic conditions. Rural population as well as busy people in urban area who never find time to get appointment can get healthcare services by the use of technology. However irrespective to urban, rural healthcare system is more focused on patients under remote conditions. Ganapathy et al, (2016) stated that rural population is geographically dispersed as well as faces limited access to specialized health providers. Nevertheless as shown in figure 4, the rural internet access and cell coverage of Sri Lanka increasing rapidly. Thus introduction of IoT will have a greater benefit for rural areas of Sri Lanka who suffer from scarce healthcare consultants.
3) Information technology and Mobile application penetration in Sri Lanka
Mobile phone is the fastest spreading technology of this millennium. Its penetration is becoming deeper in mostly every industry in the world. In 2017 nearly 68% global population is using mobile phone which has increased nearly 15 fold since 2010 (Sri Lanka Telecom communication, 2019). According to intertelivestats.com currently 6,087,164 people of Sri Lanka are using internet which accounts for 48.7% of total population and 0.2% of worldwide internet users more than 3.5 million face book users and 60K Instagram users are Srilankan. Up-to-date the mobile penetration level of Sri Lanka has risen from 97% in 2012 to 136% in 2017(Sri Lanka Telecom communication, 2018). Currently numerous mobile networks are providing service to Sri Lanka. This includes Mobitel, Diolog Axita, Hutchison Lanka, Etisalt Sri Lanka, SLT, Bharthi Airtel and Lanka bell.
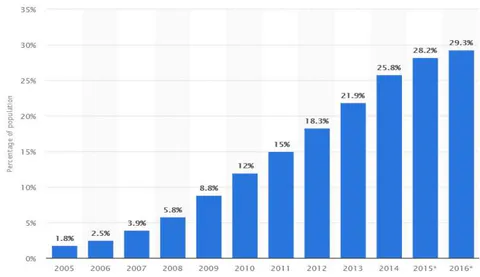
Figure 4: Mobile internet penetration in Sri Lanka, (www.statista.com, 2018)
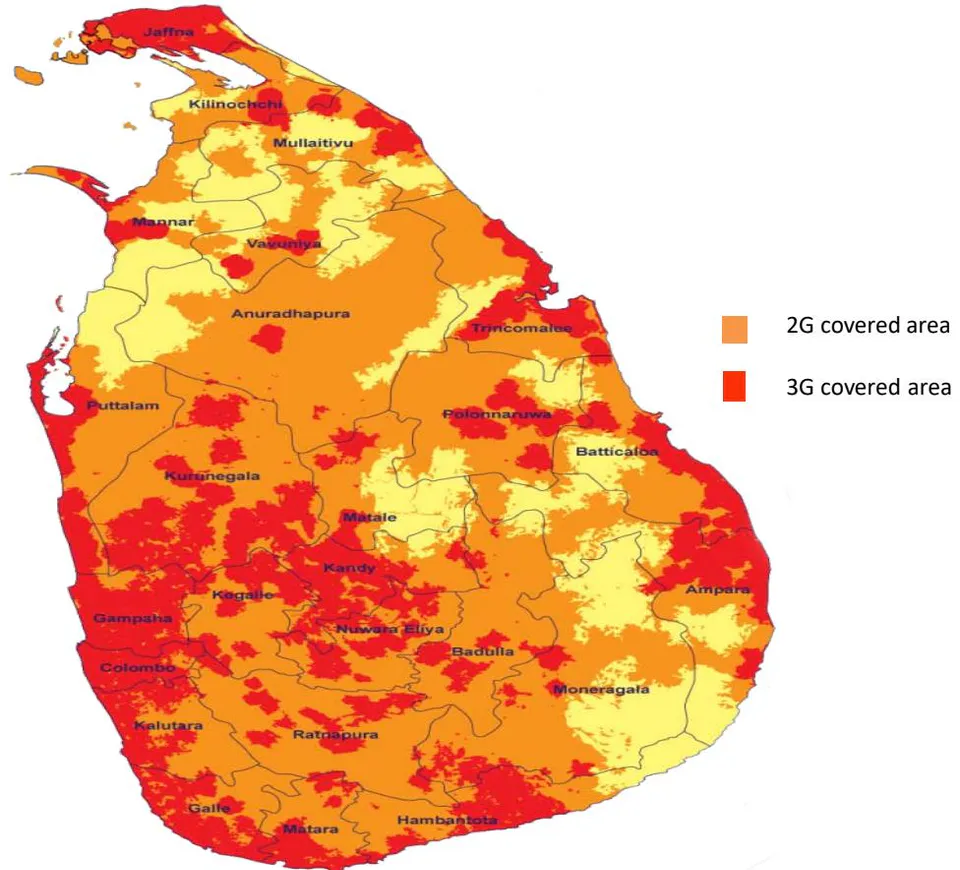
According to the International Telecommunication Union, 2G covers 90% Nation whereas 3G covers 70%. The 3G population coverage has grown from 45% in 2012 to 70% in 2015 covering 30% of the rural area of the country. Major mobile networks have introduced 4G in Srilankan market that currently covers 20% of the population (www.statista.com, 2019). In contrast to 3G, 4G technology is almost four times faster. The Sri Lanka Telecom communication provider updated their network system to fiber which current the fastest net speed providing technology in the world.
Moreover the knowledge to use internet and computer literacy rate is 48% among residents of urban sector. Whereas it is about 19.9% among population of rural sector this shows that not only mobile penetration also the literacy on information technology is higher and adequate enough to adopt IoT among both urban and rural population of Sri Lanka (Ministry of Education, 2019). Social media being the first runner among mobile application enables healthcare to join hands by giving notable opportunity such as appointment scheduling, medical record access, reminders and mobile sites utilizing such as connections from brick and motor locations many healthcare institution, begun to facilitate relative communication between patient healthcare providers from vast distances (Sheerin, Stonebanks, Jeffery & Schouten, 2016).
The level of technology plays a key role for a successful adoption of IoT (Hoque, 2016). Even though studies on IoT showed improved patient outcomes severe there are still few may be connected with the use of such technology including providing clinical decision support and protected health information quality of service. Being a developing country Sri Lanka endures from various healthcare related issues such as shortage of physicians, uncontrolled epidemic diseases and limited healthcare resources in rural areas. Various literatures (Abd Ghani & Jaber (2015); Adebara et al, (2017); Fayaz-Bakhsh & Rostami Golmohamadi, (2012) have shown that adoption of IoT can overcome such obstacles.
The objectives of the research were (1) To evaluate the impact of the proposed technological acceptance determinants on adoption towards IoT in the healthcare system, (2) To evaluate the moderating effect of provincial area in adoption towards IoT in the healthcare system, (3) To evaluate the moderating effect of Gender in adoption towards IoT in the healthcare system, (4) To evaluate the moderating effect of Age in adoption towards IoT in the healthcare system. The primitive purpose of this study is to provide Healthcare departments and agencies including; hospitals, pharmacies, pharmaceutical companies to develop a balanced idea of the expectations of the users of IoT. The findings of this study will redound to the benefit of society by analyzing the level readiness as well as awareness of the society towards IoT. This study reviewed all the possible literature based on the above mentioned concepts and will provide assessments of the researcher. The research provided useful information for various stake holders including, private hospital investors, economists, policy makers and academic researchers to identify the significant factors in the adoption of the Internet of Things in by Sri Lankan doctors. For the researcher, the study will help to gain knowledge and uncover critical area in IoT that many researchers were not able to explore. In addition this research will serve as a theoretical model for future studies of the same nature and the researchers will benefit from this study, and it will provide them the facts needed to compare their study during their, time and usability.
f) Adoption of IoT
Marks et al. (2011) discuss the adoption of IoT across the intention and behavior stages of the adoption method. They found that perceived uncertainty shows a stronger impact on intention than on adoption behavior. However, uncertainty affects each intention and behavior of adoption of innovation, though in numerous ways that (Arts et al., 2011). Whereas intention is mirrored in distant future adoption choices, behavior is mirrored in close to future adoption choices. Uncertainties concerning advantages are additional necessary, as adoption are additional distant (intention). Once the behavioral amendment is significant (near future), customers focus additional on value uncertainties, related to change and new learning (Castaño et al., 2008).
This has become the truth for many customers in numerous contexts, together with work, family, and college (D L. Hoffman, Novak, & Venkatesh, 2004). Many technologies like transportable (Licoppe & Heurtin, 2001), on-line video games (Lo, Wang, & Fang, 2005) and also the web (Hadlington, 2015) will increase customer dependency. It's been explicit that dependency is coupled to "technostress" (Shu, Tu, & Wang, 2011), which means the negative impact of technology on customers' attitudes, thoughts, behavior, and physiology (Weil & Rosen, 1997). Technological dependence might produce isolation because communication with devices substitutes communications with humans. In addition, technology dependency may also produce addiction, thanks to the abuse or overuse of a given technology (Charlton, 2002). Addiction may be seen as an additional severe sort of dependence because it will represent a status (Dhir, Chen, & Nieminen, 2015). Mani and Chouk (2016) analyzed if dependence absolutely influenced shopper resistance to sensible merchandise and if dependence was a predictor of privacy issues. The authors found proof for dependence being a predictor of privacy issues, a barrier that is mentioned higher than. However, they failed to realize a significant impact of dependence on shopper resistance. However, this will be explained by their sample, consisting of digital natives, which can have difficulties in perceiving their dependence. Older shoppers are on the opposite hand additional doubtless to understand dependence as a result of they will compare their lives before and when the adoption of digital innovations. Besides, it is tough to judge dependence while not owning the device that is being tested. It will thus be fascinating to examine if this thesis finds proof of dependency being a barrier against IoT adoption. Note that this thesis is testing thrush dependency could be a barrier for adoption, whereas Mani and Chouk (2016) tested thrush dependency cause shopper resistance.
Kim et al. (2007) define worth as "the trade-off between total edges received and total sacrifices". It has any argued that the majority shoppers do not have the necessity (D L. Hoffman & Novak, 2015, or interest (44%) in owning AN IoT device (Assurant opposition, 2017). This makes it tough for corporations to achieve several shoppers. Marketers have conjointly struggled to seek out the correct worth proposition to speak to shoppers (D L. Hoffman & Novak, 2015). As an example, increasing numbers of devices are adscititious to the IoT scheme. This raises questions about the utility and adscititious worth of those innovations (Mani & Chouk, 2016). This can be necessary as Atzori et al. (2010) suggest that perceived edges play a significant role in explaining why shoppers use IoT services. In addition, as Piwek et al. (2016) discuss in their analysis, several wearable devices do not add the useful worth that's expected, and that they need an excessive amount of effort, that ruins the user expertise. Similarly, Atzori et al. (2010) state that if shoppers do not understand the usage of devices as useful, they are unlikely to use the devices still. On the opposite hand, perceived edges provided by IoT devices are also seen as raising the standard of users' lives in an exceedingly wide selection of domains.
g) Suitable theory to study IoT adoption
In the case of IoT adoption there is lack of research on suitable constructs to study IoT adoption. Besides there was one using modified TAM by Gao and BAi (2014). However the study evidence that the adoption of IoT differs from other information technology. Also a more complicated IT adoption model needed to be applied to investigate IoT adoption. On the one hand adopting IoT is relatively east to customers, as a potential user looks on the benefit of their use, especially in facilitating life, like eliminating wired connections between used devices and reduction of labor-intensive activity in managing such system. Moreover today using modern technology is well perceived social, and by time IoT becomes cheaper, that favors the use of them. However, on the other hand, numerous objections mainly related to privacy issues make IoT adoption slower and harder.
Many researchers have attempted to investigate factors that affect the IoT acceptance by customers. Guo and Bai (2017), on their study, developed an integrated model to determine the factor that influences customer's acceptance of IoT. The model adopted TAM theory and included three technological factors (perceived usefulness, trust, and perceived ease of use), two individual user's characteristics (perceived behavioral control and perceived enjoyment), and social context factor (social influence). The study carried out on 36778 Chinese consumers, and the data were analyzed using structural equation modeling. Among the factors studied, except 'trust,' other factors had strongly influenced the intention to accept IoT, whereas 'trust; did not have any influence on predicting the intention. Author reasoned that due to lack of intention between consumers and IoT system the 'trust' become insignificant predictors of user's intention to use IoT. He further stated that IoT is relatively a new technology that's consumers hardly know the technology is less familiarized. Therefore they may not willing to assess either security or trustworthy of it. this lights out that the relationship of trust to behavioral intention is moderate on the usage of the technology. The result of the study showed that consumer expects to achieve fun or leisure related characters from the interaction with IoT which in turn give rise to highest intention to use IoT.
According to the authors the developed model can be used both in work place and market place. However they did not provide any validation values which can be trustworthy for future users of the model. Moreover the study does have many limitations. Firstly it was a cross-sectional study that failed to lighten insight more in-depth. This is to analyze the time sequence of the relationship among the construct, a logistical study needed to be carried out in future. Another drawback of this research is only forced on one economy (i.e., China) as there are different business norms, government regulation and social-cultural beliefs with other developing countries. It is better to validate the model of the study on other countries to implement this model as the universal IoT acceptance model for developing countries. Group (2014) investigated customer concern toward adopting IoT. The survey around 2000 customers in limited a state. The result of this research showed that awareness of usefulness; technology, security, privacy, and price are primary concerns of customers.
Venkatesh (2008), on his paper extends the UTAUT model to study use of technology and acceptance in a consumer context. The proposed UTAUT2 integrates three constructs, such as hedonic motivation, habit and price value. Individual differences (age, gender, and experience) were hypothesized to moderate the effects of these three constructs on technology use and behavioral intention. 1,512 mobile Internet consumers in Hong Kong were studied in this research, using a two-stage online survey.
This showed that rather UTAUT, the extensions proposed in UTAUT2 produced a significant improvement in the variance in behavioral intention as well as technology use. Since Hong Kong is a land that has a high penetration rate for mobile phones, thus finding of this study may not apply to less technologically advanced countries. Moreover the study was conducted on mean age of 3, hence may not be applied to significantly older population. This study was conducted only on one type of technology (mobile Internet). Thus future research needs to be built on this study by testing UTAUT2 model of different ages, different countries, and different technologies.
Macik (2017), on their study focused on both positive and negative factors that influence the adoption of IoT. They studied nearly 200 students of economic department of public university of eastern Poland using online structured questionnaire. The data were analyzed using univariate analysis (variance UNI ANOVA) and conserved based structural equation modeling (CBSEM). Here a modified conceptual framework combining both UTAUT2 and PIIT was used. The result of the study showed even though majority of the participate (78%) was not aware of IoT concept, their usage looks rather high, showing high levels of adoption of IoT. Macik (2017) stated that young consumers prefer usage of connected things (through WIFI, Bluetooth) than conscious IoT usage. However this study only focused on four groups of IoT, including wearable devices, smart home appliances, smart consumer electronics, and intelligent building automation. Thus concluding the adoption rate of young consumers on IoT is not acceptable. The concluding remarks of the study stated as IoT can influence the intensiveness of its usage which does not require any awareness to use the technology.
On the other hand the finding of this study turns out to be more useful information and a valuable discovery that can be considered and implemented in future studies. Among the factors studied by Macik (2017), PIIT, habit and performance expectancy have very high positive impact on the behavioral intention to use IoT. However interestingly the study denied the negative impact of the lack of funds to use IoT and pointed out it has no relevance to the adoption of IoT, even though some IoT applications seem to be costly. The cause for lack of awareness is that the consumers even use IoT devices. They use different work technologies to connect to them. They did not imagine the 'umbrella' concept because they tend to integrate them which may eventually lead to underutilization of IoT. In the light of declared reasons the author shows that young consumers do not see the real usefulness of IoT and have no intention to purchase IoT enabled devices in future. The study had several significant limitations. Firstly it uses UNI ANOVA, where the intercept did not capture all the influencing factors of the model giving rise to severe questions where only the concluded factors have impact on adopting IoT. Next the study lack adequate construct reliability thus failed to validate the UTAUT2 model for IoT adoption. Even though the model fitted data and had ethical explanatory values it failed to incorporate other possibilities relevant to adoption factors.
As studies on IoT are still new, many attempts to do qualitative researches to identify the factors that impact the intention to use new technology. Kowatsch and Mass (2012) study the intention to use IoT in Spain. When they interviewed 31 people who are experts in IoT, with the motive to validate a conceptual framework for IoT, that includes expected usefulness, perceived IoT privacy, personal interest in IoT, and trust in IoT services. The study showed that perceived privacy risk, legislation, personal interest, transparency of user information, and data security have a more significant influence on the intention to use IoT. In a similar study, Caughlan et al. (2012) conducted exploratory research on IoT adoption, where using both qualitative and quantitative approaches. Data were collected from 35 respondents. The results showed that usefulness, privacy, ease of use, awareness of the technology and knowledge were the critical factors of IoT adoption.
II. METHODOLOGY
a) Conceptual framework
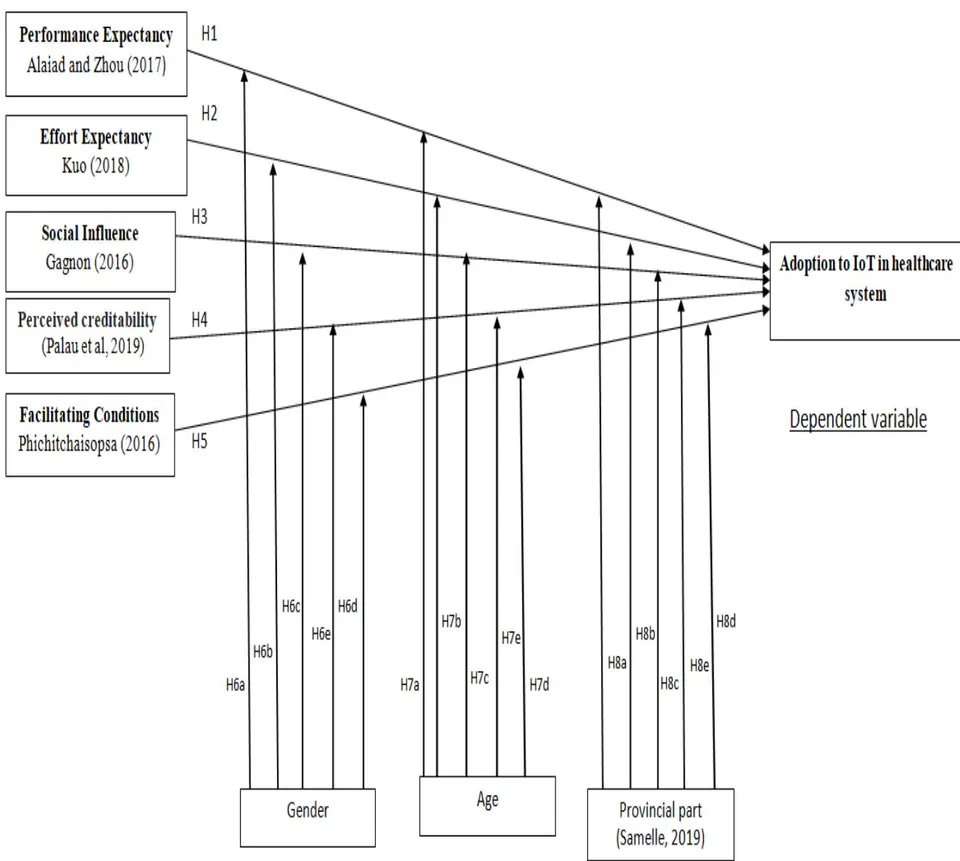
In this study figure 2.5 present the conceptual framework (research model) of the study. The framework was adopted by combining UTAUT and UTAUT2 models. Along with main UTAUT factors (Effort expectancy, Performance Expectancy, Facilitating Conditions, Social Influence). Also this model is expanded by the addition of provincial areas and employee demographics.
b) Sampling of the study
The target population is physicians who work in different provinces of Sri Lanka. The focus of the study was on the physicians, who are registered at Sri Lanka Medical Council (SLMC), the authorized government body of the country. According to the Ministry of Health (2019), there are 33,116 physicians of 995 hospitals working in the country. In 2017 Information and Communication Technology Agency (ICTA) of Sri Lanka; the Specialty Board in Biomedical Informatics, Postgraduate Institute of Medicine, University of
Colombo (PGIM); and the Health Informatics Society of Sri Lanka (HISSL) collaboratively published the number of hospitals that use IoT technology in each province of Sri Lanka in their booklet named "Digital health in Sri Lanka". The population for this study is considered to be 16,558. Krejcie and Morgan, (2010) table cited by Connaway and Powell (2010) was used in determining the sample size of the population. Therefore, the sample size of this study was taken as 375.
c) Survey Instrumentation
The survey instrument of the present study is a questionnaire administrated personally by an allocated data collection team. This enabled us to collect the completed responses within the allocated period. It also enabled the respondents to clarify any doubts at the same time if there was any. The questionnaire that was prepared by the researcher was to be answered within not more than ten minutes of the respondent's time. Furthermore, it ensured is to be completely anonymous and confidential, in case if there were any particular questions the respondents did not want to answer. The entire questionnaire was constructed in English and in layman terms to ensure that it would not cause any inconvenience and time consuming to the respondents. The subjects for this study include physicians who work for hospitals in each provincial area of Sri Lanka. Initially, 45 questionnaires were distributed to the participants for the pilot study in two hospitals and 40 responses were received (92% response rate for the pilot study). Finally 480 questionnaires were distributed to physicians, 394 questionnaires were returned. Eight questionnaires were discarded due to invalid responses (many incomplete answers). Thus, 386 usable questionnaires were yielded which resulted in 77.4% response rate across the 28 hospitals (Table 3.3).
d) Hypotheses Testing
Byne (1989) described the objective of a structural model is to explain the direct or indirect relationships with other constructs. Thus, the purpose of the structural model in this study is to test the research objectives and the hypotheses of the study. The final structural model was developed after reviewing the final measurement model. The sturtral model of the research were generated using SPSS V26 an D AMOS V26. Hypotheses were tested through the proposed final model of the study, which was developed by the final structural model. Summary conclusions for the nine hypothesized relationships are provided in Table 6.
III. RESULTS
a) Demographic Profile
Employee demographics are referred as the characteristics of the healthcare professional. Along with the UTAUT hypothesis, three main factors determine the relationship with other moderators. They are of gender, experience, and age. According to Venkatesh et al., (2003); Burtonjohes and Hubona (2006); Yu et al. (2009), and Kijsasnoyotin et al. (2009), this moderator have more significant impact on behavioral intention to adopt new technologies.
This study considers eight demographic factors (as per the questionnaire Appendix -2A) as follows. The job status of the 375 respondents; 48.5% are Medical officers, 34.5% are Resident officers 34.5%, 11.5% Full-time General physician and 5.5% are Full-time Surgeon/Specialist. The composition of the sample indicated that 46.9% of respondents are represented by females while the remaining 53.1% are represented by male respondents. The study reveals that the largest group of respondents fell into the 30-35 years age group (38.5%). Of the rest, 23.5% are of 35-40 year age group, followed closely by the 41-45 age groups at 21% and only 8 respondents are above the 50 year age group. The work experience of the studied 375 respondents, 44.5% have below 2 years of experience and 25.5% have 3-5 years of experience. Out of the total respondents, 17% have more than 7 years of experience in the existing health care organization. The type of occupied hospital of the 375 respondents. Out of the total respondent 52.3% are working in the community hospital, 11.7% are working in private hospital and 9.3% are working in government hospitals. The duration spend in mobile by the 375 respondents, shows 44.5% use mobile for more than 3 hours whereas only 26% rarely use mobile, followed by 17.6% of the respondents use less than one hour. The work experience of the 375 respondents, 68.8% uses mobile health, 15.2% uses patient record access and 13.9% uses Hospital in build RFID.
| Frequency | Percent | |
| Hospital in-build RFID patient monitoring | 52 | 13.9 |
| Mobile health | 258 | 68.8 |
| Patient record access | 57 | 15.2 |
| Others | 8 | 2.1 |
| Total | 375 | 100.0 |
b) Testing the Moderating Effect
1. Testing the moderating effect of Gender (Hyphothesis-1)
The moderating effect for the model with latent constructs (Gender) was analyzed using Multi-Group CFA. The procedure will estimate the two models separately. One is the constrained model while the other one is the unconstrained model. For the test to be significant, the difference in Chi-Square value must be higher than the value of Chi-Square with 1 degree of freedom, which is 3.84.
| Effort Expectancy | Model | Chi-square | df | Change in Chi-square | Change in df |
| Male | Unconstrained | 1194.8 | 717 | 58.4 | 1 |
| Constrained | 1253.2 | 718 | |||
| Female | Unconstrained | 1130.63 | 717 | 76.65 | 1 |
| Constrained | 1207.28 | 718 | |||
| Performance Expectancy | Model | Chi-square | df | Change in Chi-square | Change in df |
| Male | Unconstrained | 1194.8 | 717 | 16 | 1 |
| Constrained | 1210.8 | 718 | |||
| Female | Unconstrained | 1130.63 | 717 | 21.9 | 1 |
| Constrained | 1152.53 | 718 | |||
| Social Influence | Model | Chi-square | df | Change in Chi-square | Change in df |
| Male | Unconstrained | 1194.8 | 717 | 7.32 | 1 |
| Constrained | 1201.9 | 718 | |||
| Female | Unconstrained | 1130.63 | 717 | 8.21 | 1 |
| Constrained | 1138.84 | 718 | |||
| Facilitating Conditions | Model | Chi-square | df | Change in Chi-square | Change in df |
| Male | Unconstrained | 1194.8 | 717 | 6.8 | 1 |
| Constrained | 1201.6 | 718 | |||
| Female | Unconstrained | 1130.63 | 717 | 3.67 | 1 |
| Constrained | 1134.3 | 718 | |||
| Perceived creditability | Model | Chi-square | df | Change in Chi-square | Change in df |
| Male | Unconstrained | 1194.8 | 717 | 9.46 | 1 |
| Constrained | 1204.26 | 718 | |||
| Female | Unconstrained | 1130.63 | 717 | 7.07 | 1 |
| Constrained | 1137.7 | 718 |
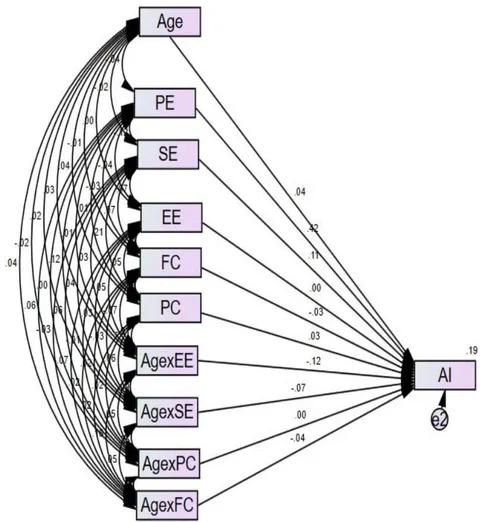
2. Testing the Moderating Effect of Age (Hyphothesis-2)
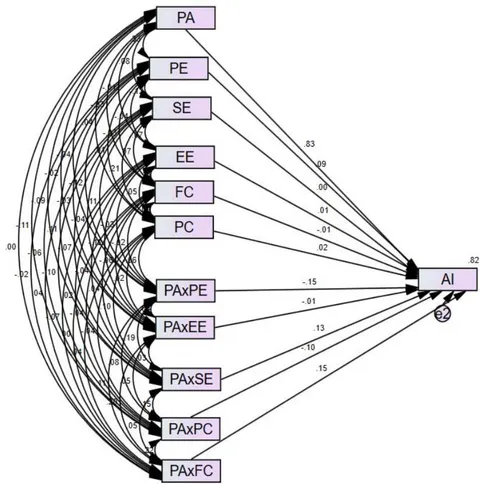
To test the moderator effect for observed variables (Age, provincial part), in addition to the variable X(independent), M (moderator), and Y(dependent), a new variable namely XM from the product of X multiply M was created. Thus, the variables involve will be X, Y, M, and XM. The information can be modeled in the following regression equation:
Using AMOS the regression coefficient and P value were generated. If the P-value for XM is less than 0.05 then the moderator has significant effect on the relationship between independent and dependent variables.
3. Testing the moderating effect of Provincial area (Hyphothesis-3)
Before testing the moderating effect, provincial part constructs were assessed with the internal consistency reliability (Cronbach's alpha), the descriptive summary and the inter-item correlation values. Each item in the construct was measured on a Likert scale of 1 to 5, where a response of 1 indicates strong disagreement while a value of 5 indicates strong agreement to the statements. There are eight items in this construct (Append -2 A). The statements are formulated as positive. Cronbatch's alpha was 0.916. The highest correlation for each item with at least one other item in the construct is between.3 and.9 (Table 4.31). Thus, all the items correlate adequately in the construct.
| Descriptive statistics | Inter-Item Correlation Matrix | ||||||
| Item | Mean | Std. Deviation | PA1 | PA2 | PA3 | PA4 | PA5 |
| PA1 | 3.68 | 1.238 | 1.000 | .887 | .714 | .652 | .677 |
| PA2 | 3.66 | 1.263 | .887 | 1.000 | .656 | .566 | .578 |
| PA3 | 3.38 | 1.300 | .714 | .656 | 1.000 | .695 | .691 |
| PA4 | 3.58 | 1.238 | .652 | .566 | .695 | 1.000 | .756 |
| PA5 | 3.61 | 1.200 | .677 | .578 | .691 | .756 | 1.000 |
The provincial areas in the country have a significant impact on the level of IoT acceptance. For instance, healthcare in the capital usually is updated technology with the support of healthcare administrators. This might have a considerable positive impact on the ease of technology. Also difference toward technology acceptance can affect behavioral intention in different provincial areas. Studies conducted in United States as well as in India showed the relationship between different provincial areas and different technological cultures. Kakoli and Soumava (2008), in their study, showed that the provincial area impacts the behavioral intention toward use of technology.
They future stated that cultural identity of difference in provincial areas as well as different countries could invoke drastically on people. Li and Kirkup (2007) showed that use of technology varies between Chinese and British students. Mainly on use of internet, their level of perceived usefulness, and their ability to access knowledge. Moreover cross-cultural differences also have a considerable effect on IoT acceptance factors.
Research by Oshlqansky et al. (2007) indicated that social influences have a significant impact on all country samples, where cross-cultural differences to affect the actual results. Thus studying the impact of cross-cultural differences in technology acceptance is suitable enough. This may be useful to comparatively analysis countries with numerous provincial areas such as China, Thailand, India or Sri Lanka. Also, Sri Lanka, a country with multiple ethnicities has different cultures in different provincial areas. These provinces have differences in various fields, including local dialect, local foods, and, more importantly access to technology. Furthermore the doctor-patient ratio drastically varies among these provinces. For example Western province (i.e., Colombo) has average of 2.5 doctor/patient ratio, whereas in Central province (i.e., Nuwaraliya) has 0.37 of that. Therefore the research is interested in study the provincial area as a modulator of technology acceptance factor.
There are numerous studies carried out concerning the relationship between province areas and technological acceptance Yu et al., (2009) studied user acceptance with respect to the prepayment between United States and India. Because these two countries are different and opposite poles with respect to culture, the study found that Effort expectancy, Social influence, Performance expectancy positively impact the intention of user toward use of prepayment system of these countries, whereas different cultures within the countries affect behavioral intention. A study by Mun Lee (2014) investigated the technology another acceptance level cross-culturally. They studied nine countries, including Malaysia, South Arabia, New Zealand, South Africa, Czech Republic, United States and India, United Kingdom, and Greece. The study showed that website acceptance is influenced by social influence more than in other countries.
| Results | ||
| H1a | Gender moderate Performance Expectancy in adoption towards IoT in the healthcare system | Supported |
| H1b | Gender moderate Effort Expectancy in adoption towards IoT in the healthcare system | Supported |
| H1c | Gender moderate Social Influence in adoption towards IoT in the healthcare system | Not Supported |
| H1d | Gender moderate Facilitating Conditions in adoption towards adopt IoT in the healthcare system | Not Supported |
| H1e | Gender moderate Perceived Creditability in adoption towards IoT in the healthcare system | Supported |
| H2a | Age moderate Performance Expectancy in adoption towards IoT in the healthcare system | Not Supported |
| H2b | Age moderate Effort Expectancy in adoption towards IoT in the healthcare system | Supported |
| H2c | Age moderate Social Influence in adoption towards IoT in the healthcare system | Supported |
| H2d | Age moderate Facilitating Conditions in adoption towards IoT in the healthcare system | Supported |
| H2e | Age moderate Perceived Creditability in adoption towards IoT in the healthcare system | Not Supported |
| H3a | Provincial area moderate Performance Expectancy in adoption towards IoT in the healthcare system. | Not Supported |
| H3b | Provincial area moderate Effort Expectancy in adoption towards IoT in the healthcare system | Not Supported |
| H3c | Provincial area moderate Social influence in adoption towards IoT in the healthcare system | Supported |
| H3d | Provincial area moderate Facilitating Condition in adoption towards IoT in the healthcare system | Supported |
| H3e | Provincial area moderate Perceived Creditability in adoption towards IoT in the healthcare system | Supported |
IV. DISCUSSION
a) Impact of gender as moderator in adoption towards IoT
The five hypotheses (H1a-H1e) as revealed in Table 3, examine the impact of gender as moderator in adoption towards IoT. For performance expectancy, the research results differ from the UTAUT findings for the moderator of gender. Consequently, females who are part of the healthcare staff should focus on explaining the benefits of IoT technology rather than the processes involved.
Besides, the male group was affected by these modulators with regards to effort expectancy. This suggests that they should demonstrate an understanding of healthcare technology usage, as well as its convenience, ease of use, and lack of complications; until they would like for it to be usable. Almost all those surveyed who were male and in the older age group were physicians. Physicians mainly have a critical role in treating patients. The researcher expects that physicians' time is limited. Therefore they want their work with technology to be easy.
Sometimes, physicians want to be able to find information by themselves. Therefore, many reasons provide motivation for studying healthcare technology.
Gender was found insignificant in modulating the relationship between effort expectancy and the adoption of IoT in hospitals, which is the opposite of much previous research including the findings from Hu, et al. (1999), Kuan and Chau (2001), Zhu, et al. (2006a), Lin and Lin (2008), Alam (2009) and Ramdani et al. (2009), all of whom have suggested that gender is significant for the adoption of technology in both the individual and the organizational contexts; but in line with Chau and Tam (1997), Thiesse et al. (2011,
Partially) and Wang et al. (2016). Chau and Tam (1997) argued that adopters and non-adopters 'are not (pp14). Wang et al. (2016) argued that the insignificance was caused by the fact that the adopters and non-adopter think almost the same regarding the advantages technology brings, and this study reflected the same.
Contrary to the findings of Anne, et al. (2010), Zhu, et al. (2016a), Alam (2019), Ramdani et al. (2013) and Wang, et al. (2016), but in line with the findings from Lin and Lin (2018), Ramdani et al. (2019), Thiesse et al. (2011), Oliveira et al. (2014) and Gutierrez et al. (2015), compatibility is found to be insignificant. Lin and Lin (2018) argued that adopters might already have made the changes necessary for adoption. Ramdani et al. (2019) explained that the insignificance might be because the adopters do not have many things to integrate with the new adoption. Thiesse et al. (2011) think the reason for insignificance in their research lies with the sample, as the sample used contained only adopters. Oliveira et al. (2014) attributed the result to the nature of the technology being adopted in their research.
b) Impact of age as moderator in adoption towards IoT
The hypotheses (H2a-H2e) examine the impact of age as moderator in adoption towards IoT. This study presented that the intention to adopt IoT by physicians is higher in younger people. In UTAUT2, age is a moderator of performance expectancy to behavioral intention, concluding that performance expectancy's effect is stronger for younger respondents. The average age of respondents in this study is 27.75 (SD=6.7). In correlation analysis, age did not show significant correlations to any constructs, but the highest correlation was demonstrated with facilitating conditions. This relation explains that younger people, with an average age of 27, are the ones who have supported conditions to adopt IoT by physicians. This is because the new generation of physician works with colleagues of same age who always use updated healthcare technology like IoT.
c) Impact of provincial areas as moderator in adoption towards IoT
The hypotheses (H3a-H3e) examine the impact of provincial areas as moderator in adoption towards IoT. The study revealed that the provincial area has a positive impact over facilitating conditions towards behavioral intention of the physicians, this result is in line with the study carried out by Kakoli and Soumava (2018), there were different regarding the access of technology (i.e., prepayment acceptance) between countries such as India and USA. They conclude that country or provincial areas have serious impact on acceptance of technology, on all the dimensions of the technology acceptance, refereed in UTAUT. However this study showed positive moderator of provincial area only in social influence and facilitating conditions.
Concerning Sri Lanka, the availability of healthcare technology varies among the provincial area. On the one hand the western province enjoys hospitals utilized with high technology, whereas, on the other hand, Central province has district hospitals with simple technology settings. It has widely complained that the government of Sri Lanka did not diffuse healthcare technology (i.e., IoT) equally to all province of the country, causing significant adoption toward novel healthcare technology like IoT. The differences in such availability of technology might reason the moderate effect of the provincial area towards adoption of IoT.
The study by Kavin (2017) also showed that personal attitude perceived behavioral control as well as Social influence is moderated positively by the cross-cultural difference between different provincial areas. This is in line with the Srilankan context because Sri Lanka is a country with multiple cultures and languages. It could be reasoned that differences in norms, believes among multi-culture may impact the behavioral intention towards IoT. The study by Manassis (2016) interpreted a case study, showing that cultural differences of the patient have a more significant impact on physician patient relationship. Mainly when there is a difference in patient's cultural background from physician'. This, in turn, causes poor communication as well as unsatisfactory treatment results leading to dissatisfaction of physicians toward the use of treatment strategies, including IoT technology.
Social influence also incorporates the hospital culture. Moreover, study by Chen et al. (2016) showed that variation in hospital culture among difference provinces of China has positive effect on clinical physicians; this is in line with the result of this study.
Facilitating conditions of each provincial area must provide equal support to all provincial areas of the country, including software, hardware, IT staff and patient awareness towards IoT technology. To overcome these issue administrators need to define policy to IT staff regarding salary and benefit which could also promote IoT among healthcare staff.
In conclusion, the result is in line with the statement made by Jeyaraj et al. (2006) that the provincial area is one of the best predictors in organizational adoption research; the provincial area has also been found by Ramdani et al. (2009) as the most significant variable. Alam (2009), Thiesse et al. (2011), and Oliveira et al. (2014) all found provincial area to be an essential factor that influences the adopting of IoT. Most of the studies tend to agree with Jeyaraj et al. (2006) by reporting it as an impacting factor in an adoption decision (Zhu and Kraemer 2005; Zhu et al. 2006a, 2006b; Ramdani et al. 2009, 2013; Oliveira et al. 2014 and Wang et al. 2016). Thong (1999) argued that firm residence is the most influential factor in determining the adoption of IoT.
V. CONCLUSION
An extensive amount of literature has been published related to technology acceptance or adoption. However, a very lack of studies covered the topic of IoT at hospital adoption. As an example, from 92 references used to study the adoption of IoT in the healthcare industry, using UTAUT, only one paper discussed a similar field (Park et al., 2018). Regarding the theoretical implications, this study contributed to the development of the UTAUT2 model, specifically in the field of IoT at hospital adoption. By extending UTAUT2 with other significant variables, such as perceived creditability and attitude, this study brought the novel insights into consideration for further research. UTAUT2 argued that the most influential antecedent to adoption intention was performance expectancy. This study gave a new perspective to identify trust as an influential factor driving intention to adopt IoT technology.
This study provided insights for companies, to understand better what the determinants of adopting IoT products are. From the result of the study, it could be concluded that, firstly, the company might gain more consumers' intention to adopt IoT by building trust. This trust concept consisted of two, namely trust to the company and trust in the product. In order to get trust in the company, it might be essential to establish proper relationships with users, offer friendly customer service, create a pleasant customer journey or convince that the company has excellent quality products. Furthermore, trust in the product might be earned by highlighting that the product is secure and created to help users.
Secondly, marketers should consider the strategical ways to promote the usefulness of the product. This could be achieved by utilizing the social influence or communicating the message through the right channels. This study argued that family, friends, and colleagues might contribute to consumers' intention to adopt IoT products. It was also substantial to note that people who are important to consumers or people who influence their behaviors played a critical role in shaping their minds.
Another finding in this study discovered that younger and innovative people are more likely to adopt IoT products. Hence, marketers might consider to target young people and reach consumers who like to explore new technologies. Besides, this study also implicated that consumers who have sufficient resources and knowledge toward IoT at home have a higher intention to adopt. The company could help to provide these facilitating conditions, such as providing the easy-to-read information about the product, the ease to deliver products to home, or guidance when consumers find difficulties.
The research suggests that increasing physician's adoption towards IoT and healthcare organizations should create awareness of IoT products. This could be done in two comprehensive stages; first increase awareness among healthcare staff, which should be focus on the way to bring business benefits to the organization. Secondly awareness should be created among the patients, the final customers of IoT technology, which should be focused on enhancing both novelty and quality of IoT enabled healthcare products (i.e., Smart watch).
However, the IoT technology is still in its early premature stage of development and requires an intense evangelization. To a certain extent, this research had identified the critical factors that impact adoption towards IoT in healthcare industry in the Sri Lankan context. Then results were supported by the empirical study of the research and can be implemented both theoretical as well as managerial context to impose radical change in the field of technology adoption of healthcare industry.