



I. INTRODUCTION
Hypohidrotic Ectodermal Dysplasia (HED) is included in a large and heterogeneous group of hereditary diseases that affect the ectodermal tissue, affecting 1 in every 100,000 births. It is a X-linked pattern disease and also recessive, being more common in males, not presenting a complete phenotype when present in females.
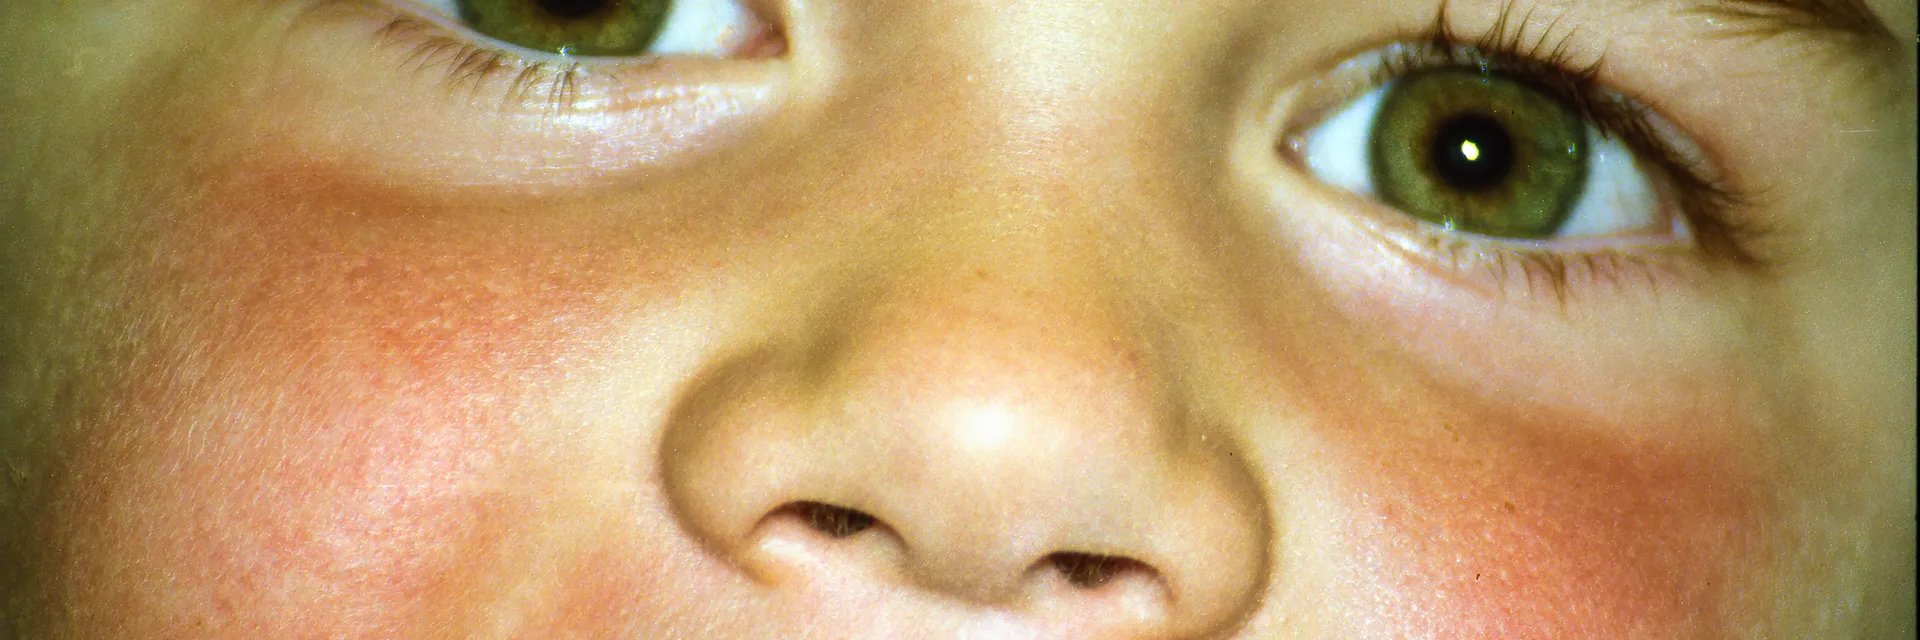
Hypodontia, hypotrichosis and hypohidrosis form a classic triad of characteristics of HED, which are manifested in clinical signs such as the dry aspect of the skin, the presence of thinning hair, absence of primary teeth and permanent dental germs. In addition, there is a typical facial concavity, the prominence of the frontal region of the face, the presence of the saddle nose, and thick and everted lips. As a result of the absence of dental elements, there is an underdevelopment of the gnathic bones, resulting in a decrease in the vertical dimension of the face, as well as a projection of the chin, giving the patients an aged appearance. Among the oral manifestations of this dysplasia, in addition to hypodontia, there is the presence of conoid teeth and hyposalivation, which can generate the clinical condition of xerostomia. It is important that the dentist knows how to identify these characteristics and that the oral rehabilitation of this patient is performed early, in order to reduce its impacts on masticatory function, speech and esthetics.
II. LITERATURE REVIEW
HED is a syndrome with signs and symptoms that can be seen since the individual's birth, such as the presence of dry mucous membranes and the absence of sweat glands, while others develop as the child grows. In the first months it is possible to observe the non-eruption of some dental elements and after the first year, facial characteristics become more evident.
Multidisciplinary monitoring of patients with HED is fundamental to their quality of life, even though it is an irreversible condition, it is possible to mitigate the effects of their signs and symptoms. When performing routine consultations from early childhood (0 to 5 years old), the dentist is able to identify the main oral manifestations and plan an appropriate conduct, according to the patient's needs. In this phase, it is already possible to observe absences and or changes in the shape of dental elements that can directly interfere in the development of speech, food and even in the social relationship during the beginning of the school phase.
The case reports found in the literature described oral rehabilitation as an option to reestablish the esthetics and function of the stomatognathic system, assisting in the musculoskeletal development of patients with HED. The different techniques analyzed varied according to the previous planning carried out in each clinical case. From the earliest age (3 years) to the later reported rehabilitation (16 years) it was seen that when reestablishing the patient's oral function, the impacts of HED manifestations were minimized. There was less bone resorption from the alveolar crest, with lesser changes in the vertical dimension of occlusion and a lesser tendency to develop Angle class III malocclusion.
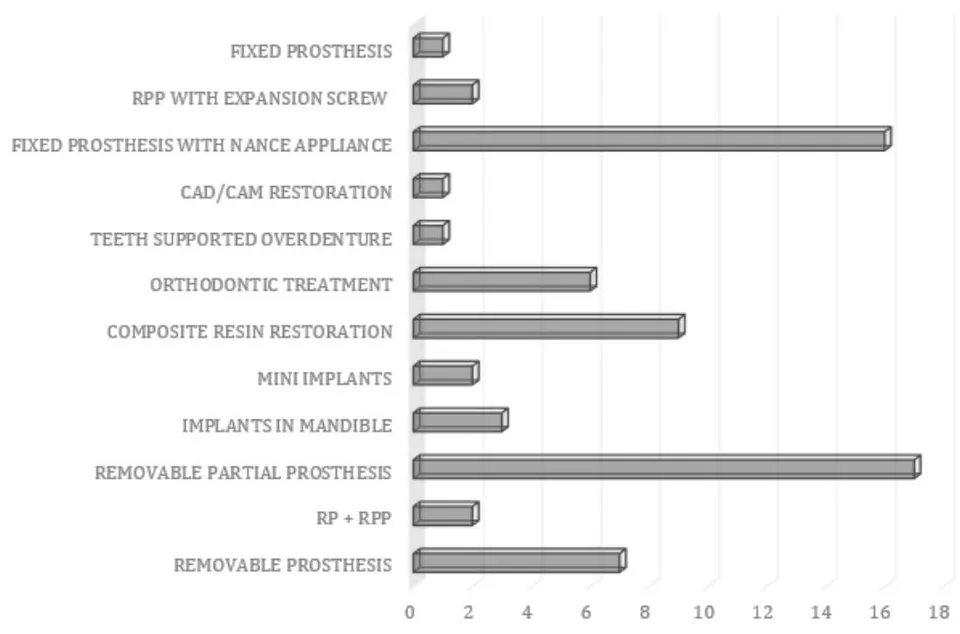
Currently, the development of materials and techniques in Dentistry offers a variety of prosthetic rehabilitation options. However, removable prosthetic devices are still the most indicated in cases of early manifestation of HED (Table 1), as they are easy to make options, have a satisfactory cost-benefit ratio and are easy to replace during peak periods of bone growth in child and adolescent patients. The limitations found to rehabilitate these patients with conventional removable prostheses are largely associated with the difficulty in fitting for their use 15, the presence of hyposalivation due to changes in the exocrine glandular pattern, causing discomfort and lack of adhesion of the prosthesis to the oral mucosa. The set of limitations linked to continuous bone growth in this age group, leads to the need for frequent replacement of these prostheses.
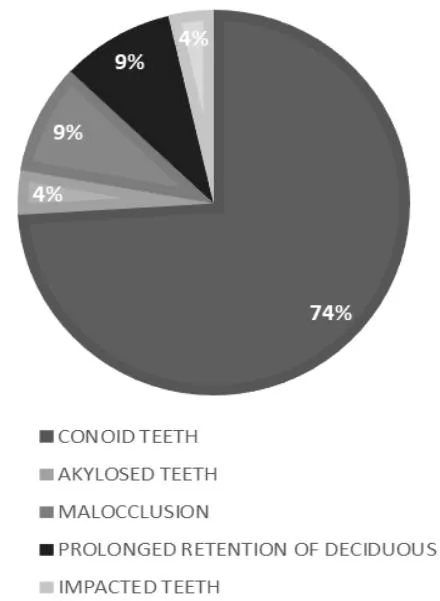
Most of the patients in the analyzed studies had conoid teeth during primary dentition. The pointed shape of these elements gives the smile a vampiric appearance, and re-anatomization with light polymerizable composite resin was the most used option for these cases. Esthetic procedures like these, require a thorough restoration technique, generally requiring a longer clinical time. In these cases, the patient's age and his/her degree of collaboration are the main limiting factors found, and are not directly related to specific manifestations of HED. A study presented the making of crowns in the CAD/CAM system as an alternative to ensure the proper anatomy for conoid teeth, which overcomes the disadvantages of direct composites, avoiding the adverse effects resulting from polymerization, such as contraction.
After the eruption of the first permanent tooth, the phase that begins on average at 6 years old, the individual begins to have a mixed dentition, that is, he has permanent and deciduous teeth in his oral cavity. In patients with HED, this fact will depend on the existence of permanent dental germs, and in most cases due to hypodontia or anodontia they are absent. Thus, there is a prolonged retention of primary teeth , which should exfoliate naturally, allowing the eruption of permanent teeth. In some prosthetic rehabilitation, extraction of these retained elements is necessary, as it is considered as a limitation by some reported cases, since this step may involve a more invasive surgical procedure, as these dental remnants may be ankylosed. Due to the limitations in retention and stability of conventional removable prostheses, it is possible to use the remaining teeth in order to guarantee these properties, an alternative mentioned were the protheses known as overdentures . The prosthetic device is stabilized by a fitting system, which can be made on remaining teeth or on intraosseous implants. Tooth supported overdentures can be made if the dental element has sufficient bone insertion to guarantee the support of the prosthesis. Its greatest disadvantage is the need for invasive dental preparations and elective endodontic treatment in child and adolescent patients.
Overdentures when retained by intraosseous implants require prior surgery to install them. The preservation of alveolar bone is its greatest advantage in relation to conventional prostheses, a subject that was widely discussed in the Delphi International Consensus . Different types of implants with varying sizes and shapes can be used for oral rehabilitation, mini implants were alternatives reported in some clinical cases, as they guarantee the same advantages as the conventional implant, presenting less amplitude, being less invasive and therefore more suitable for child and adolescent patients .
According to Schnabl (2018), orthodontics can be considered a good option to redistribute toothless spaces and modify alveolar and maxillomandibular growth, through functional devices. Of the clinical reports analyzed, 83% included orthodontic treatment as a phase of oral rehabilitation, some of them used maxillary expanders associated with removable dental prostheses . (Graph 2)
The fit for the use of these devices by the patient and the greater accumulation of bacterial plaque may be limitations of this treatment, requiring more effective oral hygiene and greater effort for its continuous use.
PROSTHETIC REHABILITATION PRIMARY DENTITION MIXED DENTITION PERMANENT DENTITION TOOTH SUPPORTED OVERDENTURE 4 3 REMOVABLE PROTHESIS 2 4 2 REMOVABLE PARTIAL PROTHESIS 3 8 1 FIXED PROTHESIS WITH NANCE 1 RP WITH EXPANSION SCREW 9 8 CAD/CAM RESTORATION 1 MINI IMPLANTES 1 1 ORTHODONTIC TREATMENT 4 1 COMPOSITE RESTORATION 3 2 FIXED PROTHESIS 1 1 IMPLANTS WITH MANDIBLE 1 1
III. DISCUSSION
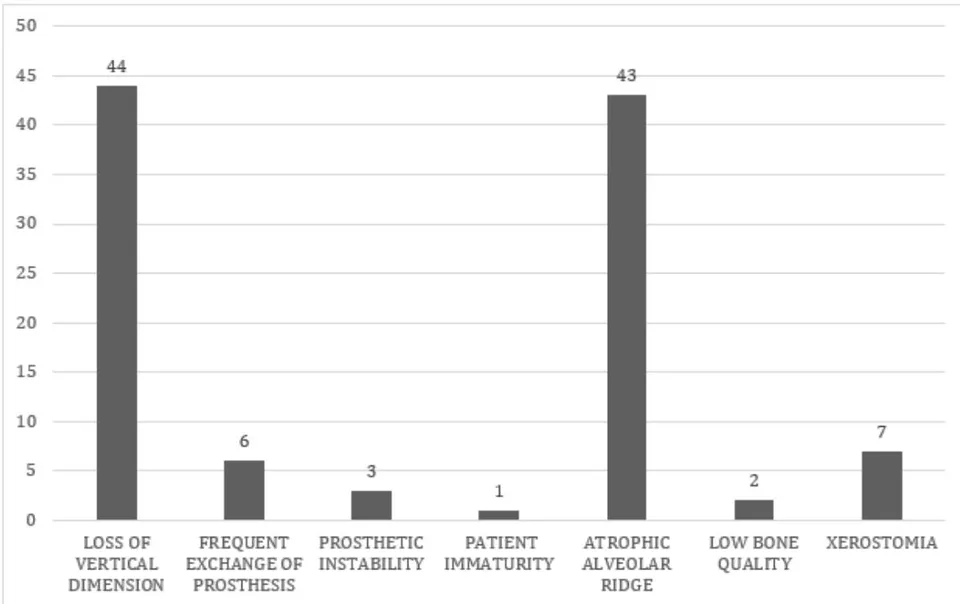
Among the main characteristics of HED, the one that most interferes in the oral rehabilitation of these patients, consists of the underdevelopment of the mandible and maxilla bones (Graph 3), resulting in the difficulty of guaranteeing retention and stability of the prostheses. This is due to congenital hypodontia seen in individuals with the disease. The difficulties encountered in the management of these patients are similar to those of an elderly edentulous patient (Table 2), but in child and adolescent patients there is the challenge of reconciling rehabilitation treatment with the continuous development of craniofacial bones, making it difficult to carry out long-term treatment, and leading to need for regular adjustments .
Retention of removable prosthetic devices is one of the essential biomechanical principles to ensure stability in the oral cavity. It is facilitated by the presence of a film of saliva capable of creating a surface tension, between the mucosa and the base of the prosthesis, keeping it in position. Patients with HED can report dry mouth, most often caused by hyposalivation , and consequently may compromise retention in cases where there is the use of removable prosthetic devices.
In relation to maxillomandibular occlusion, a greater tendency is observed for these patients to present Angle class malocclusion . This factor is a challenge in prosthetic rehabilitation, since surgeries capable of reversing this condition are generally invasive and are not indicated for patients in the analyzed age group.
When making dental prostheses, the step of impression of the bone edge and dental structures is of paramount importance to reproduce plaster casts with intraoral references. The difficulty in selecting appropriate impression trays for the patients' anatomy, and finding stock teeth with ideal size and shape, has been reported in the literature as one of the factors that could limit prosthetic rehabilitation. However, it can be considered that they are more associated with the early age of rehabilitated individuals, than with HED itself.
Family support for the patient's rehabilitation treatment is an indispensable factor for their success. The lack of good oral hygiene and encouragement of the use of prosthetic and orthodontic devices were seen as limitations during oral rehabilitation. In individuals at an early age, especially, the role of family members is of utmost importance both in helping to insert and remove the prosthesis properly, as well as in cleaning and encouraging its continued use.
Intraosseous implants have been described by some researchers as a treatment option for growing patients due to physiological bone conservation. The recommendation is that the patient has completed his bone growth phase, which can be observed through radiographic examinations of the hand and wrist. However, in children with conditions such as HED, the alveolar bone does not develop in the region of congenital tooth absence. According to the Delphi Consensus (Klineberg et al, 2013), it is possible to install implants before the pubertal growth spurt, in cases of severe anodontia and oligodontia, as long as there are no adjunct teeth.
Implants in the maxilla region are contraindicated for these patients, as they grow through sutures, and there is no safe area for placement. Although there are reports of implants placed in this region, clinical or experimental data, especially in the long term, are insufficient to support this indication. On the other hand, they can be placed in the anterior region of the mandible when clinically justified, from 7 to 8 years old (Klineberg et al, 2013). The mandibular posterior region should be avoided until the end of childhood, due to its anteroposterior, transversal and vertical growth. In this area, bone growth can generate infra-occlusion and multidimensional dislocation of the implants.
In contrast to natural teeth, implants do not allow the compensatory movements that are provided by the periodontal ligament. They behave like ankylosed teeth, and can prevent bone growth around them. Thus, rehabilitation with implant-supported prostheses can impair the continuous growth of the mandible and maxilla in child and adolescent patients, as they are in the bone development phase. According to the literature, the installation of intraosseous implants is preferable in patients with complete anodontia, as they do not present dental germs susceptible to eruption, and consequently bone growth occurs on a smaller scale, decreasing the chances of unwanted movements in the regions of the implants.
| LIMITING FACTORS IN THE PROSTHETIC REHABILITATION | PRIMARY DENTITION | MIXED DENTITION | PERMANENTE DENTITION |
| LOSS OF VERTICAL DIMENSION | 6 | 24 | 15 |
| FREQUENT EXCHANGE OF PROSTHESIS | 2 | 4 | |
| PROSTHETIC INSTABILITY | 1 | 1 | |
| PATIENT IMMATURITY | 1 | ||
| ATROPHIC ALVEOLAR RIDGE | 6 | 22 | 15 |
| LOW BONE QUALITY | 1 | 1 | |
| XEROSTOMIA | 1 | 4 | 1 |
IV. CONCLUSION
Through this literature review, it can be concluded that the underdevelopment of gnathic bones is the greatest limitation for the oral rehabilitation of patients with HED, hindering the retention and stability of prosthetic devices. As a first treatment option, as it is a less invasive technique, the use of conventional prosthesis should be considered, especially in patients at an early age. The use of intraosseous implants is preferably indicated after bone maturity and in cases of severe anodontia, due to bone growth on a smaller scale. Mini-implants can be considered effective and less invasive options when compared to conventional ones. The other reported rehabilitation options can be indicated according to the needs of each clinical case.



