
I. INTRODUCTION
Lumbar spinal canal stenosis is the most common spinal disorder in elderly patients, which may lead to low back and leg pain, and paresis. Hypertrophy of the ligamentum flavum contributes in canal narrowing.
In 1913, Elsberg first reported the case showing sciatica caused by the ligamentum flavum hypertrophy. Afterward, many clinical reports followed to indicate that ligamentum flavum hypertrophy was the main pathology inducing significant clinical symptoms in patients with lumbar spinal canal stenosis.
Since then, others have suggested that the ligamentum flavum contributes to spinal disease, most prominently spinal stenosis. Furthermore, it is postulated that the ligamentum flavum hypertrophy may lose its elasticity and, thus, fold into spinal canal, which leads the compression of the dural tube.
It is reported that in clinical and anatomical biomechanics, in extension the ligamentum flavum bulges inside the spinal canal or foramen and compresses nerve tissues.
Thus, the morphological changes of the ligamentum flavum that are due to the change of lumbar spine alignment, as well as decrease in disc height associated with degeneration, may result in compression on nerve tissues. Fibrotic and chondrometaplastic changes occur in ligamentum flavum with aging.
The present study was undertaken to know about morphological and histological changes that occur in ligamentum flavum with aging, in a spinal stenosis.
II. MATERIALS AND METHOD
a) Study Design
This prospective multidisciplinary study involving clinical, radiologic and histologic assessment using human samples of the lumbar ligamentum flavum was carried out in the department of Orthopaedics, Jawaharlal Nehru Medical College Wardha from October 2012 to April 2015. Total 47 patients enrolled in the study of those who came to our hospital after fulfilling the inclusion criteria. Out of these 47 patients, 28 were males, and 19 were females.
b) Protocol And Technique
Forty-seven patients were diagnosed with Lumbar spinal canal stenosis (males - 28, females - 19), mean age - 50.51 years, (minimum- 41 years, maximum - 72 years).
Patients with a spinal deformity such as scoliosis or kyphosis, fracture spine or infection of spine were excluded from this study.
The study protocol was approved by the institutional ethics committee and, consent form signed by each subject.
| Spinal stenosis patients | No. of patients |
| Males | 28 |
| Females | 19 |
| TOTAL | 47 |
In standardized format, data concerning patients' history and clinical symptoms collected. The clinical complaint of low back pain was present in 42 of 47 patients five patients were without low back pain. 40 of 47 patients showed additional radicular symptoms. In all, 47 patients complained of neurogenic claudication (40 in combination with low back pain, seven without low back pain) with an average pain-free walking distance of 100 metres. All patients underwent MR Scan to confirm lumbar spinal stenosis, and that was consistent with pain pattern and level of neurologic deficit. All patients were clinically examined completely, including the neurological examination.
| Neurogenic claudication | |
| with low back pain | 40 |
| without low back pain | 7 |
| Low back pain | |
| with radicular symptoms | 35 |
| without radicular symptoms | 7 |
| Neurologic Defects | |
| Motor | EHL weakness - 15 |
| Ankle weakness - 1 | |
| Sensory | 14 |
| Reflexes | 10 |
| Lasegue's | 7 |
c) Measurements of the Ligamentum Flavum
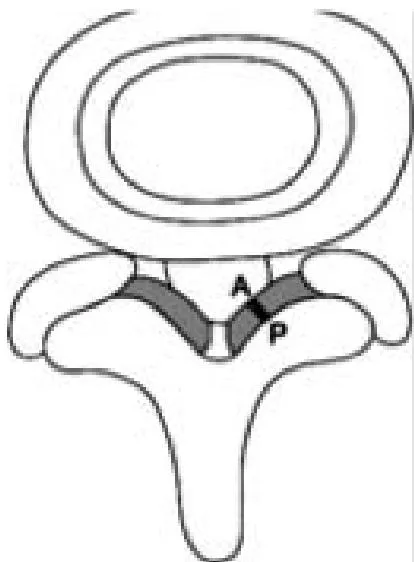
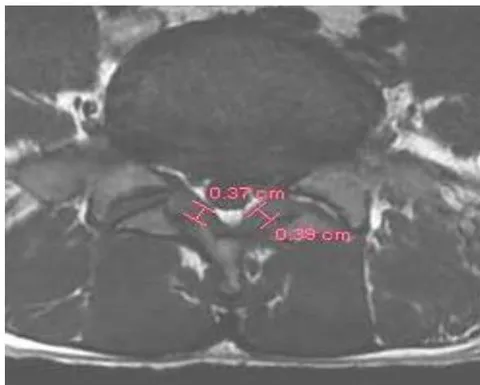
All patients who were clinically diagnosed with having spinal canal stenosis in the lumbar region were sent for an MRI scan. Measurements of ligamentum flavum were taken as follows.
We used PACS software and a PACS workstation (GE Medical Systems, 1.5 Tesla) to measure the thickness of ligamentum flavum. The measurements were taken independently by two different persons including one radiologist.
A Total of 180 ligamentum flavum was measured in 47 patients.
The right and left ligamentum flavum (LF) for the involved vertebral level was measured. Thickness at the middle portion of ligamentum flavum was measured. All measurements were taken by two persons separately and mean was calculated.
A total of 87 ligamentum flavum were harvested, using a standardized technique. Ligamentum flavum tissue was harvested at L3 - L4 in 13 patients, L4 - L5 in 38 patients and at L5 - S1 in 36 patients (Table. 5) from total of 47 patients (men - 28, women -19) (mean age -50.51 years).
| S NO. | LEVEL | NO. OF LIG. FLAVUM HARVESTED |
| 1 | L3 - L4 | 13 |
| 2 | L4 - L5 | 38 |
| 3 | L5 - S1 | 36 |
| TOTAL | 87 |
d) Histopathological analysis
The harvested ligamentum flavum samples were fixed with 10% buffered formalin for 48 hours and then paraffin blocks were prepared.
Serial 4 m thick sections were taken after being deparaffinized with xylene and replaced by ethanol. Stains used were hematoxylin and eosin stain, Trichrome stain and Verhoeff stain using standard methods. A light microscope (Olympus CH 21) was used.
- Trichrome Stain: The degree of fibrosis was evaluated and graded according to its severity(range 0-4).
Grade 0 – indicates normal tissue with no fibrosis Grade 1 – fibrosis ≤ 25%
Grade 2 – between 25% and 50%
Grade 3 – between 50% - 75%
Grade 4 - ≥ 75%.
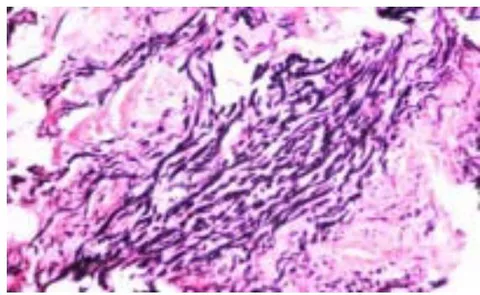
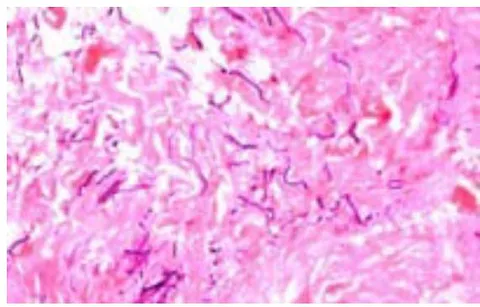
- Verhoeff Stain: The elastic fibers were stained. The loss of elastic fibers was also graded; the same scoring system was used as for the fibrosis score.
Grade 0 – black color stained all area of the ligamentum flavum, indicating rich elastic fibre content.
Grade 1 – loss of elastic fiber ≤ 25%
Grade 2 – loss of elastic fibre between 25% and 50%
Grade 3 – between 50% - 75%
Grade 4 - ≥ 75%.
3) Haematoxillin & Eosin stain (Calcification)
In H & E stain calcification stains bluish in color with the pink eosinophilic background. In slides with extensive calcifications, the areas stained bluish in color at many sites.
Two persons (R.A., an orthopaedic surgeon, and S.S., a pathologist) simply estimated these gradings. The relationships of these fibrotic, loss of elastic fiber scores, and calcification with the thickness of ligamentum flavum measured by T1 – weighted axial magnetic resonance imaging (MRI) examination before the surgery were evaluated at each site of the ligament.
III. RESULTS
a) Gross
The surface of ligamentum flavum on the ventral side is not uniform and smooth always. It ranges from smooth to eroded, creases in the ligamentum flavum as results of folding of the ligament. The dorsal side was never smooth it was in all cases irregular, thick, rough, and hypertrophied.
b) Clinical study
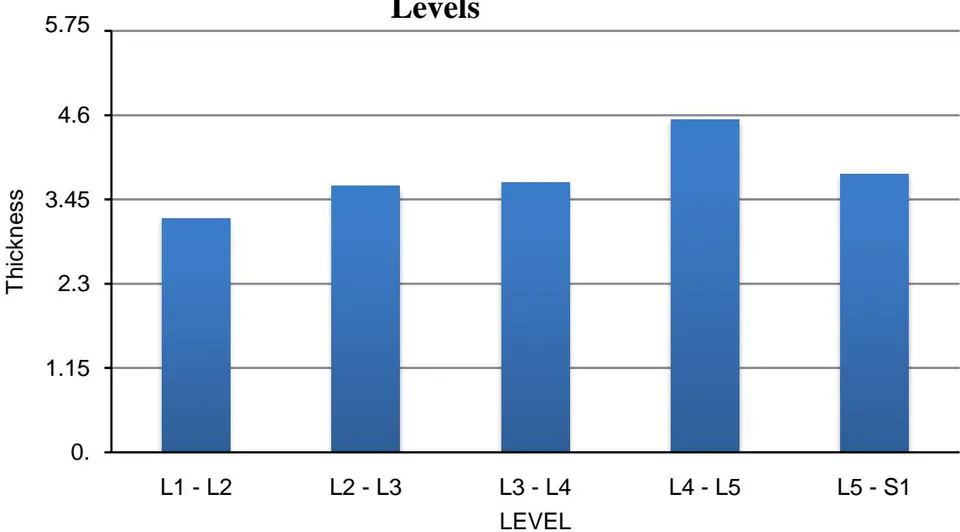
Ligamentum flavum thickness was measured in total of 180 ligaments on T1 weighted axial images on plain MR Scan. Overall the thickness increased with age at all levels however, the increase was most pronounced at L4/L5.
| SPINAL LEVEL | NO. OF LIGAMENTUM FLAVUM | MEAN THICKNESS (mm) |
| L1/L2 | 2 | 3.1875 |
| L2/L3 | 5 | 3.63 |
| L3/L4 | 14 | 3.680 |
| L4/5 | 33 | 4.535 |
| L5/S1 | 33 | 3.8 |
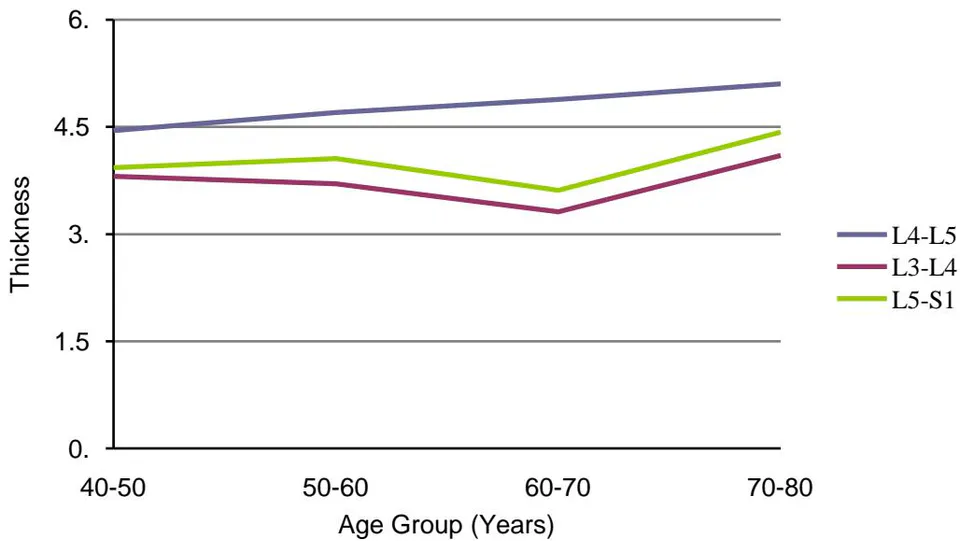
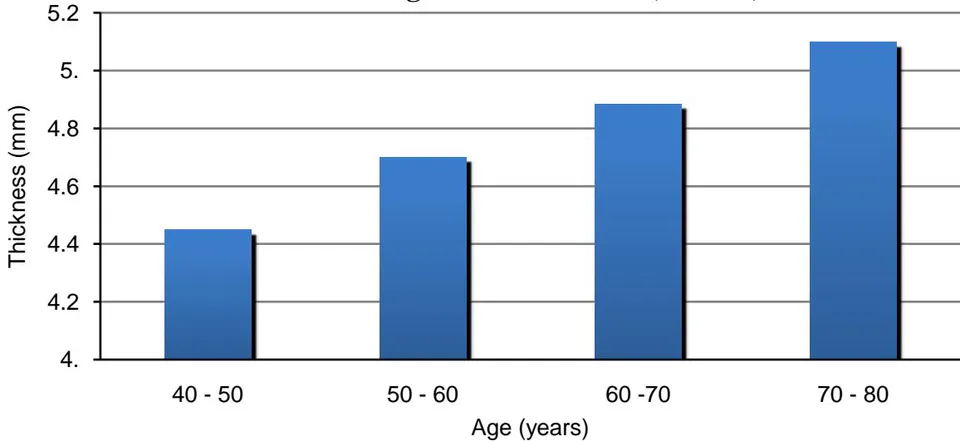
AGE (years) NO. OF PATIENTS MEAN THHICKNESS (mm) MINIMUM THICKNESS (mm) MAXIMUM THICKNESS (mm) 40 - 50 5 3.81 3.125 4.775 50 - 60 4 3.706 3.375 4.225 60 - 70 4 3.312 2.925 3.6 70 - 80 1 4.1 — — AGE (years) NO. OF PATIENTS MEAN THICKNESS (mm) MINIMUM THICKNESS (mm) MAXIMUM THICKNESS (mm) 40 - 50 19 4.510 3.2 5.25 50 - 60 10 4.7525 4.0 5.5 60 - 70 5 4.838 4.45 5.0 70 - 80 1 5.1 —— 5.1
AGE (years) NO. OF PATIENTS MEAN THICKNESS (mm) MINIMUM THICKNESS (mm) MAXIMUM THICKNESS (mm) 40 - 50 17 3.930 2.355 5.075 50 - 60 9 4.055 2.825 4.675 60 -70 5 3.61 3.025 4.4 70 - 80 1 4.425 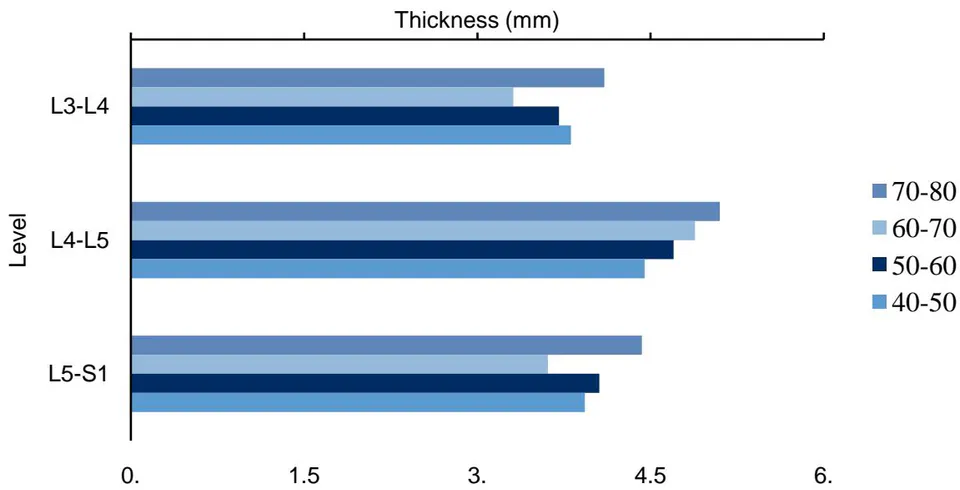
The thickness of ligamentum flavum at L4/L5 levels continuously increased with age. The mean thickness of the ligamentum flavum in all patients was 3.1875 mm, 3.63 mm, 3.680 mm, 4.535 mm and 3.8 mm for L1/L2, L2/L3, L3/L4, L4/L5 and L5S1 levels, respectively. The thickness of the ligamentum flavum was highest at the L4/L5 level.
The ligamentum flavum at L5 - S1 level increased with age except in the age group 60 - 70, less number of subjects may be a reason. However, ligament thickness at L3 - L4 level do not show an increasing trend with age, may be a larger number of subjects at this level can give a more accurate result.
However, an increasing trend was found between increasing age groups and thickness of ligamentum flavum at L4 -L5 level as the thickness of ligamentum flavum at L4 - L5 level continuously increased with age though the correlation was not statistically significant.
c) Histological Evaluation of the Ligament
A total of 87 ligamentum flavum were harvested. Ligamentum flavum tissue was harvested at L3 - L4 in 13 patients, L4 - L5 in 33 patients, and L5 - S1 in 33 patients from total of 47 patients (men - 28, women -19) (mean age - 50.51 years) (Table. 5).
| S NO. | LEVEL | NO. OF LIG. FLAVUM HARVESTED |
| 1 | L3 - L4 | 13 |
| 2 | L4 - L5 | 38 |
| 3 | L5 - S1 | 36 |
| TOTAL | 87 |
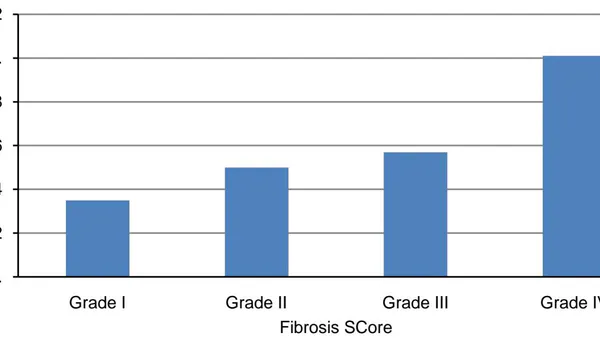
| FIBROSIS SCORE (GRADE I - IV) | MEAN THICKNESS (mm) | MINIMUM THICKNESS (mm) | MAXIMUM THICKNESS (mm) |
| GRADE - I | 4.35 | 3.2 | 4.95 |
| GRADE - II | 4.50 | 4.0 | 4.875 |
| GRADE - III | 4.569 | 4.025 | 5.25 |
| GRADE - IV | 5.01 | 4.25 | 5.75 |
The Mean thickening of the ligamentum flavum increased with increasing grade of the fibrosis, showing a strong linear correlation, which is also statistically significant (p - value < 0.05).
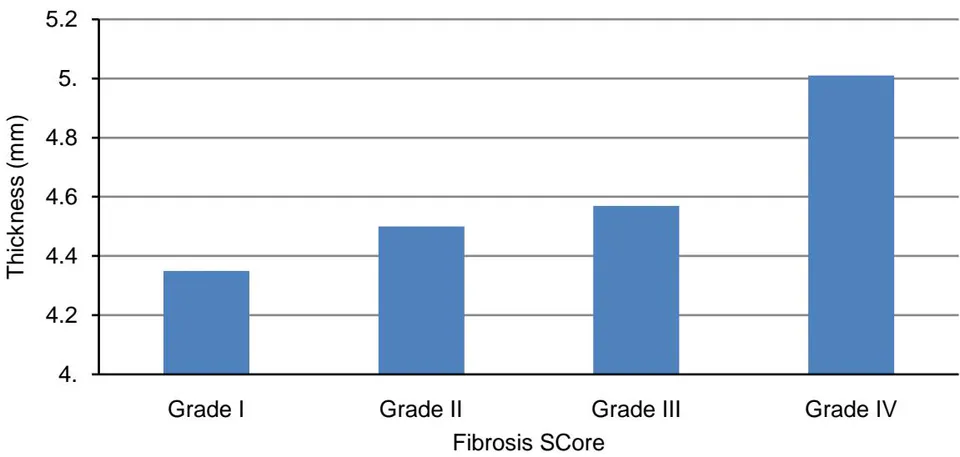
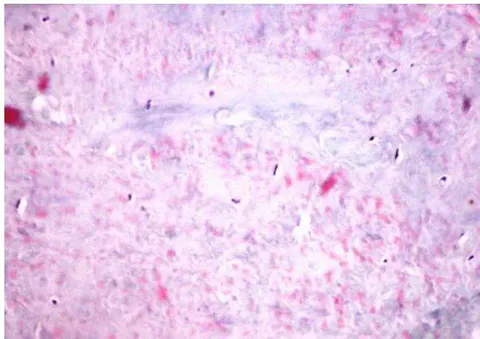
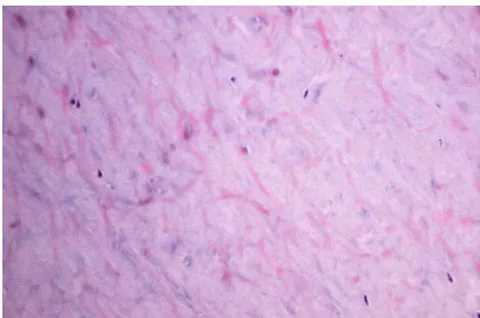
Fig. 10. & Fig. 10.1 In grade I all area of the ligamentum flavum was stained an eosinophilic pink colour, and a blue color stained the minimum area, indicating fibrosis. On the other hand, in grade IV, blue - stained most of the areas, indicating that most of the area showed fibrosis.
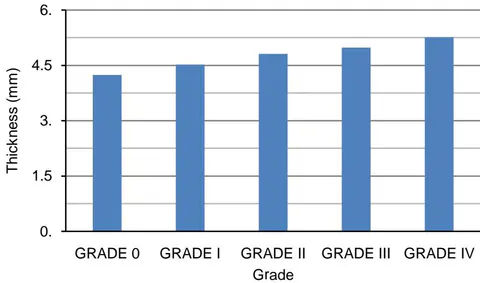
| LOSS OF ELASTIC FIBER SCORE | MEAN THICKNESS (mm) | MINIMUM THICKNESS (mm) | MAXIMUM THICKNESS (mm) |
| GRADE - 0 | 4.13 | 3.2 | 4.95 |
| GRADE - I | 4.41 | 3.825 | 5.25 |
| GRADE - II | 4.70 | 4.325 | 5.0 |
| GRADE - III | 4.870 | 4.65 | 5.25 |
| GRADE - IV | 5.15 | 4.85 | 5.65 |
An increasing trend was found when Loss of elastic fibre score was compared with the mean thickness of the ligamentum flavum. The thickness of
e) Calcification
In patients with lumbar spinal stenosis, 83 of 87 ligaments were calcified.
All patients in whom calcification was found in the ligamentum flavum were divided into three groups.
Patients were classified into three age groups as follows:
1. Those aged 40 - 50 years (19 biopsies)
- Those aged 50–60 years(26 biopsies)III - those aged above 60 years(18 biopsies).
| AGE GROUP | NO. OF PTS | NO. OF LIG FLAVUM | CALCIFICATION |
| I (above 60 years) | 6 | 18 | 18 |
| II (50 - 60 years) | 10 | 26 | 24 |
| III (40 - 50 years) | 19 | 43 | 41 |
| TOTAL | 35 | 87 | 83 |
The percentage of calcification increased with age across the three groups (I> II > III) (Table 3). An increasing trend could be seen in the calcification as the percentage of calcification increases with the increasing age. However, it is statistically not significant.
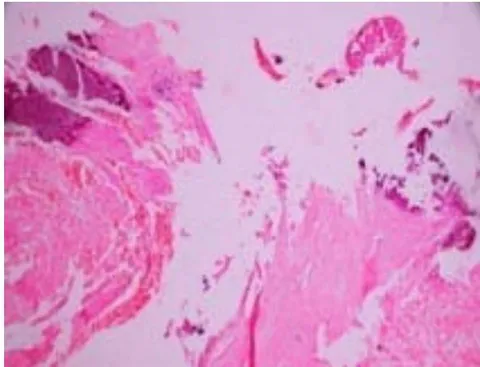
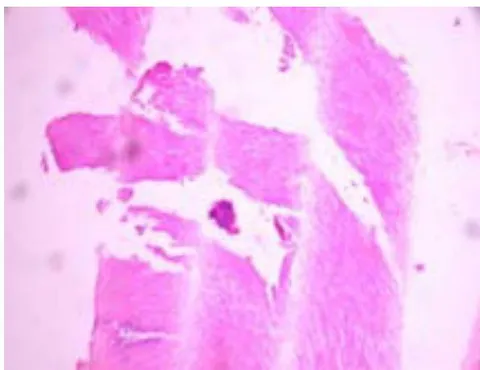
A relationship between age and degree of calcification could only be seen as a trend (the older, the more calcified), but was statistically not significant (P > 0.05).
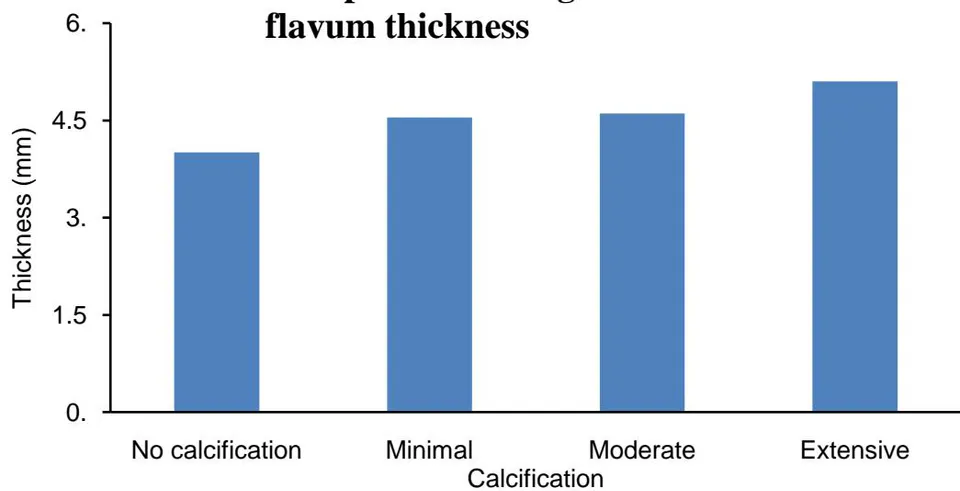
| CALCIFICATION | MEAN THICKNESS (mm) | MINIMUM THICKNESS (mm) | MAXIMUM THICKNESS (mm) |
| NO CALCIFICATION | 4.005 | 3.0 | 4.75 |
| MINIMAL | 4.545 | 4.0 | 4.95 |
| MODERATE | 4.606 | 4.125 | 5.3 |
| EXTENSIVE | 5.103 | 4.325 | 5.875 |
IV. DISCUSSION
The ligamentum flavum covers the posterior wall of the spinal canal. Thus as the ligamentum flavum hypertrophies, it will compress the spinal cord, cauda equina, or nerve root. Hypertrophy of ligamentum flavum is one of the major factors of canal narrowing in lumbar spinal canal stenosis. Numerous studies have investigated the mechanism of ligamentum flavum hypertrophy from the view points of anatomy, histology, and biology.
To date, few viable hypotheses have been established regarding the pathomechanism of ligamentum flavum hypertrophy.
In our present study, we have carried out a clinical, radiological, and histological study on ligamentum flavum.
The causes of ligamentum flavum hypertrophy are multifactorial, including activity levels, age, and mechanical stress. To elaborate on these causes in detail, several attempts have made in the literature to clarify the pathomechanism of the ligamentum flavum hypertrophy.
a) Clinical study
GROSS: The surface of ligamentum flavum on the ventral side is not uniform and smooth it always ranges from smooth to eroded, creases in the ligamentum flavum as results of folding of the ligament. The dorsal side was never smooth. It was in all cases irregular, thick, rough, and hypertrophied. These findings are consistent with Teruaki Okuda et al. In the present study we measured the thickness of 180 ligamenta Flava from 47 subjects in the age groups ranging from 40 to 80 years age (Mean age - 50.51 years) in Lumbar spinal stenosis patients. The thickness of ligamentum flavum was found to increase with age. A trend can be seen that the thickness of ligamentum flavum increases with age; however statistically, r it was not significant. However, the changes with age showed spinal level dependence. The increase in thickness with age was largest at L4/L5, probably because of increased mechanical stress at this level. These findings are consistent with the results of Koichi Sairyo et. al (2005).
The lumbar spinal canal varies in shape and may be an oval, rounded triangular or trefoil configuration. The trefoil configuration usually is more common at the fifth lumbar level, making L4-L5 the narrowest level.
Although factors like body weight, activities of daily living, could affect the ligamentum flavum the thickness but not considered in the present study. The purpose of the present study was to understand the natural course of the variations in thickness of the ligamentum flavum. Koichi Sairyo, Vijay Goel et. al discovered the loading mode that will relatively induce the most tensile stress. They observed that maximum stress was observed in flexion mode. Thus, a mode that requires flexion, such as lifting, may lead to ligament hypertrophy.
In 1938 Naffziger et al. was the first to state that hypertrophy of the ligamentum flavum was the result of injury with scar formation.
Similarly, in 2005, Koichi Sairyo, Vijay Goel et al. reported that the dorsal side of ligamentum is highly stressed during the activities of daily living. During lumbar motion, mechanical stress causes damage in the ligament, and the repairing process in the ligament fibrosis occurs similar to scar formation.
b) Histologic study
In our study, we also focussed on major histological changes. A total of 87 ligamenta Flava were harvested during surgery from the spinal canal stenosis patients and subjected to the histological examination. The following stains were used 1) Haematoxillin and Eosin stain 2) Masons Trichrome stain 3) Verhoeff stain. Eighty - seven ligaments were stained with H & E staining and Trichrome stain, whereas 30 ligaments were stained with Verhoeff stain.
c) Fibrosis (Trichrome stain)
The fibrosis score showed a positive linear correlation with ligamentum flavum thickness, and statistically, it was significant (p - value < 0.05). In our histological study using Mason's trichrome staining the fibrosis appeared in all areas of a hypertrophied ligamentum flavum. Fibrosis is a type of scarring that occurs as a result of an injury. Scar formation has been reported in the repair process following injuries in ligaments such as medial collateral ligament of the knee joint therefore hypertrophied ligamentum flavum could have suffered a stress - related injury leading to scar formation.
These findings are consistent with the results of Koichi Sairyo et. al. . They reported in their study that the accumulation of scar tissue could be an important factor in the development of ligamentum flavum hypertrophy. The dorsal layer showed the most pronounced fibrotic damage.
d) Elastic fibers (Verhoeff stain)
It has been reported that in young ligamentum flavum, the elastic fiber content is high, and it decreases with aging.
This collagen/elastin conversion is considered to be one of the pathomechanisms of ligamentum flavum hypertrophy. In our study, the histologic results with Verhoeff staining showed that the loss of elastic fibers correlated with ligamentum flavum hypertrophy. Thus it supports the theory that increased collagen (fibrosis) could be the main factor in collagen/elastin conversion without decreasing the elastic fiber content.
It was noted in our study even in Grade I, the elastic fibers was not parallel as it is noted in non-degenerative ligamenta Flava, i.e. the fibers should appear parallel. This was consistent with Menson and Fender.
Our study also showed that this parallel order was disturbed in the ligamenta flava in a lumbar spinal stenosis. These findings are consistent with the results of Yoshida et al.
Also, Peter K. Schräder et. al measured every fiber angle in the ligament; they proved that the parallel order of the elastic fibers is lost in a degenerative lumbar spinal stenosis.
e) Calcification
Calcification of the ligamentum flavum is reported to appear more often in combination with other degenerative changes of the spine. Avrahami et al. indicate an incidence of 80% in a group of 30 patients with radiologically confirmed lumbar spinal stenosis. Calcification of ligamentum flavum is a rare entity, reported more commonly in patients from Japan and the French Antilles. It is usually seen in middle-aged women and most commonly affects the cervical spine. It is thought to be due to deposits of calcium pyrophosphate within the ligamentum flavum. The calcification may be symptomatic if it abuts the spinal cord, and surgery usually helps for symptomatic patients. Although this fact is considered a manifestation of degenerative disease of the spine.
Calcification is common in the Asian population in the lower thoracic and cervical spine and rare in the western population. In our study 80 of 87 ligaments were calcified ranging from extensive calcification to minimal calcification.
Our findings confirm that clinical symptoms of lumbar spinal canal stenosis are associated with calcification of the ligamentum flavum. Patients with symptoms that were severe and surgery were indicated showed moderate to severe calcification in the ligament.
Baba et al. reported in five patients who underwent lumbar decompressive surgery for cauda equina syndrome and radiculopathy secondary to degenerative stenosis and were associated with calcium deposition in the ligamentum flavum. Histology proved degeneration in elastic fibers and calcium deposition in the ligamentum flavum. This was interpreted as being associated with the degenerative process in the ligament, and changes were suspected as causing or aggravating the neurological symptoms also quantitative analysis of calcification was not performed in their study. No information is given to describe the degree of degeneration of elastic fibers.
Yoshida et al. studied 45 cases of lumbar spinal stenosis by CT and pathologic and immunohistochemical studies. The control group included, ten cases of acute disc herniation. Statistically significant differences in thickness and transverse area of ligamenta flava were found compared to the controls. The pathogeneses of the hypertrophied ligamentum flavum were divided into three major groups: (1) fibrocartilage change due to proliferation of type II collagen, (2) ossification, and (3) calcium crystal deposition.
Postacchini et al. examined ligamenta flava obtained from nine lumbar disc herniation patients and ten patients with lumbar spinal stenosis. The ligaments were studied histologically, histochemically, and at ultrastructural levels. Controls comprised ligaments from six patients undergoing surgery for thoracolumbar fractures. In lumbar spinal stenosis, degenerating elastic fibres were seen occasionally, calcification could also be seen often. Histological findings of degeneration were observed in controls aged 50 or older.
Schrader et al. evaluated twenty-one patients (13 men, 8 women, age range 44 - 80) who underwent decompressive surgery of the spinal canal due to signs and symptoms of degenerative lumbar spinal stenosis. In patients with lumbar spinal stenosis, 35 of 38 ligaments were calcified. As the distribution of age was heterogeneous, the degree of calcification about the age was set. The percentage of calcification increased with age across the three groups. The control group, 3 of 20 ligaments showed minimal calcification.
Due to the close proximity of ligamentum flavum to the dura and spinal nerves, it is obvious that ligamentum flavum may contribute considerably to the pathogenesis of lumbar spinal stenosis.
Our analysis of calcification of the ligamentum flavum proves that this degenerative process can cause sciatic or neurological clinical findings in a lumbar spinal stenosis. These findings are consistent with the results of Schrader et al.
Postacchini et al found age-related changes in the ligamentum flavum. These findings are consistent with our results.
Thus it can be assumed that apart from reduced elasticity of the ligamentum flavum a concomitant increase of volume of the ligament due to calcification and reduction of elastic fibers may contribute to the pathogenesis of lumbar spinal canal stenosis. Many authors in the past have described an association between changes in the ligamentum flavum and degenerative lumbar spinal stenosis.
In the present study, we have described the role of calcification in ligamentum flavum hypertrophy, these findings are consistent with the results of Schrader et al.
Kazuo Miyasaka, Kiyoshi Kaneda, et al. reported that ossification and calcification of the ligamentum flavum have different clinical, radiologic, and histologic presentations.
The etiology and mechanism of calcification remain unclear, but probably are distinct from those of ossification.
Hypertrophy of LF is considered an important causative factor in the development of lumbar spinal stenosis (compression of the dural sac and roots) and significantly contributes to low back pain and sciatica.
However, there are multiple factors leading to Lumbar canal stenosis. In our study in patient no: 19 though the clinical symptoms were severe the ligamentum flavum hypertrophy was fewer as compared to other patients who had less symptoms so it can be stated that LF hypertrophy is not the only factor leading to lumbar canal stenosis, other factors like the shape of the canal, bony spurs, facet joint arthropathy, spondylolisthesis, and other degenerative processes are also responsible for Lumbar canal stenosis. Hence during the surgical decompression for lumbar canal stenosis, the exact cause of the symptoms should be considered, so that the symptoms of the suffering patient are taken care of.
V. CONCLUSION
We can conclude from our study.
Ligamentum flavum hypertrophy compresses the spinal cord, cauda equina, or nerve root and is one of the major factors of canal narrowing in lumbar spinal canal stenosis. The causes of ligamentum flavum hypertrophy are multifactorial aging (degenerative process) being one of them.
Fibrosis (scarring) occurs in hypertrophied ligamentum flavum, or it can also be proposed that accumulation of scar tissue can lead to ligamentum flavum hypertrophy. Scar formation occurs as a repair process following injury.
The elastic fiber content decreases with aging (degenerative process).
Calcification was noted the majority of hypertrophied ligaments, and it was more extensive in the spinal stenosis patients. It can also be proposed that calcification (as a degenerative process) can cause neurological clinical findings in a lumbar spinal stenosis.