





I. INTRODUCTION
Addiction can be defined as a relapsing and chronic illness that is characterized by the obsessive seeking of drugs and its continued use regardless of its harmful effects. [1].. Addiction totobacco, alcohol, and other drugs is the main reason for disability and death globally[2].
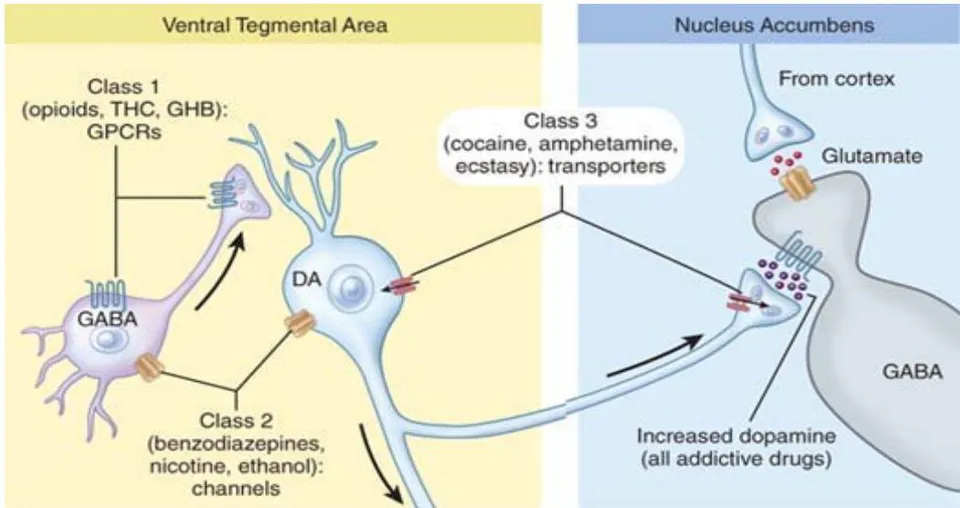
Most addictive drugs facilitate the dopamine function in the CNS [3]. The mesolimbic dopamine system was considered as their primary target of addictive drugs. The mesolimbic dopamine system starts in the ventral tegmental area (VTA), It projects to accumbens nucleus, hippocampus, amygdala, and the prefrontal cortex) Addictive drugs can be classified broadly into three classes based on their specific molecular target and cellular mechanisms for activating the mesolimbic system. 1 class targets the Gio protein-coupled receptors, The cannabinoids, opioids, hallucinogens, and Jama-hydroxybutyric acid (GHB), exerts their action via this pathway 2 class interacts with ion channels or ionotropic receptors, they include dissociative anesthetics, alcohol, nicotine, benzodiazepines, and some inhalants. And the 3 class interacts with dopamine transporter includes amphetamines, cocaine, and ecstasy. These three classes of drugs loosely map onto three distinct cellular mechanisms to increase dopamine levels. The first is the direct stimulation of the dopamine neurons (e.g., nicotine). The second mechanism is the interference with the reuptake of dopamine or the promotion of non-vesicular release (e.g., amphetamines). The third mechanism is indirect, whereby the drugs inhibit γ-aminobutyric acid (GABA) neurons that act as local inhibitory interneurons (e.g., opioids) [4].
II. LIMITATIONS OF CURRENT TREATMENTS FOR ADDICTIONS
Several pharmacological and behavioral treatments have been developed that target specific aspects of addiction. However, the effects of most currently available treatments remain disappointingly not optimal [2]. Therefore, there an increasing interest to search for new medications and revolution in the management of addiction. In this context, natural products represent a wealthy resource. The objectives of the current review are to summarize the progress in utilizing natural products in the management of addiction.
a) Methodology
Searching PubMed 2009-2019, for herbal medicine, natural products, nutraceuticals, special emphasis was given for use of Psychedelic, or psychoactive substances for management of addiction. The results are summarized below.
b) Results
History and definition of Psychedelic substances
Psychedelics are psychoactive compounds whose primary action is to alter the cognition and perception by affecting the neurotransmitters of the brain. Interestingly they are not likely to produce dependence nor addiction. The recent history of these compounds began with the isolation of mescaline, the psychoactive alkaloid produced by the peyote cactus, by Heffter in 1898, and the discovery of the effects of LSD by Hoffman in 1943.
The pharmacological effect of these compounds have been studied in a wide range of animal models [5].
c) Structure and chemistry
A-indoleamines include indolealkylamines such as dimethyltryptamine (DMT), psilocybin, lysergic acid diethylamide (LSD). B-phenylalkylamines include mescaline)[6]. (Update the structure, chemistry, clear figures).
d) Characteristic features
Many natural PSY possesses features that might encourage research regarding their utility as an anti-addiction drug: [2].
1) Absence of the addictive effects.
Their molecular target supports anti-addiction effects.
Their psychological effects, changes in behavior and personality which is persistent, likely to participate in natural addiction recovery.
e) Clinical studies
Clinical trials utilized Natural PSY has been recently reviewed. These compounds vary widely in their structures, and pharmacological profile but all relatively non-addictive, and exhibited similar subjective effects' & [2].
1. LSD & psilocybin
A meta-analysis of data on LSD as a treatment for alcoholism from the 1950s to 1960s showed its beneficial effect on alcohol abuse. A clinical trial demonstrated the effectiveness of psilocybin on smoking cessation and found that of patients were smoke-free 6 months after receiving two or three doses of psilocybin along with cognitive-behavioral therapy (CBT). Another study demonstrated the utility of psilocybin as an adjuvant in the management of alcoholism. (psilocybin-assisted psychotherapy,). These studies highlighted the preliminary efficacy of natural PSY in the treatment of depression, anxiety, addiction. They are thought to exert their main effect via partial agonist or agonist activity at the serotonin 2A (5HT2A) receptors [7]. [8].
2. DMT (Ayahuasca)
Ayahuasca is a decoction prepared using two plants: Psychotria Viridis and the vine of Banisteriopsis caapi. The 1 contains DMT (which is destroyed in GIT by MAO) and the 2 contains (MOA inhibitor) beta-carboline alkaloids and harmala alkaloids (tetrahydroharmine, harmaline, and harmine). This combination allows DMT to be effective orally [9]. ()[6]
Several animal studies using ayahuasca demonstratedits include antidepressant effect [10].[11], anti-addictive properties in an animal model for alcoholism [9, 12].
Studies in humans to demonstrate the utility of Ayahuasca—assisted therapy showed promising results., An old study showed its efficacy in the management of alcoholism Halpern et al. (2008)-Reported remission of drug or alcohol abuse or dependence, Fabregas et al. (2010)-demonstrated lower several drugs of abuse and improved psychological status Thomas et al. (2013)-, demonstrated Statistically significant reductions in cocaine use. And Improvements in some psychological parameters or quality of life
Regular ayahuasca users frequently reported a decrease in consumption of cocaine, alcohol and other addictive drugs long-term use of ayahuasca are not related with loss of cognitive function ayahuasca do not cause its tolerance and also marked it to have an inadequate dependence potential.
Ayahuasca increases the levels of stress hormones prolactin and cortisol in the blood., It may cause moderate increases in systolic (SBP) and diastolic blood pressure (DBP) was observed, with minimal change in heart rate. Ayahuasca's use for healthy individuals seems to be practically safe in the context of physiological effects. The side effects commonly observed with ayahuasca use are vomiting and nausea, which is related to the dose [13].
3. Ibogaine
Ibogaine is anindole alkaloid with psychoactive effect, it is an active constituent of an African rainforest shrub Tabernanthe Iboga. Its efficacy in the management of addiction is well documented, surprisingly after a single dose. However, ibogaine's serious toxicity that leads to fatality is one of the major causes of concern. [14].
Efficacy should be more clear
Pharmacokinetics
Ibogaine is metabolized into Noribogaine(O-desmethylibogaine or 12-hydroxyibogamine) by CYP2D6 with exhibit genetically based variable metabolizing capacity. The half-life of noribogaine is longer than ibogaine. (about?)[15, 16].
Mechanism of action
Ibogaine and noribogaine are thought to act via several pathways. They are an agonist of - and -opioid receptors and an antagonist of the N-methyl-D-aspartate (NMDA), glutamate and nicotinic acetylcholine receptors, [17].
Adverse effects Ex-Vivo and animal model
Studies in animals demonstrated serious toxicity, including cerebellar damage and abnormal cardiac function [15].
Ibogaine showed neurodegenerative effects in the rats in high doses with excitotoxic effects on Purkinje cells in the cerebellum. Dose lower than 25 mg/kg did not exhibit neurotoxicity, Besides noribogaine may be less neurotoxic than ibogaine [16].
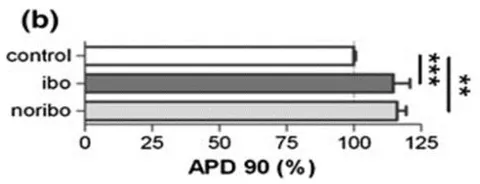
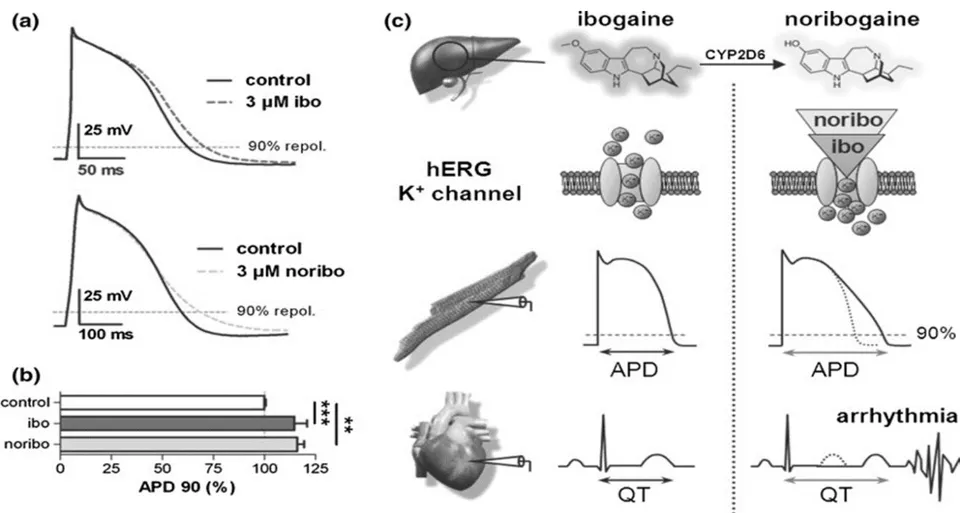
In our opinion, the dose used in human is not likely to cause neurotoxicity Support by data or ref In human cardiomyocytes, the therapeutic levels of ibogaine and noribogaine significantly decreased the action potential repolarization. Therefore their use may evoke cardiac arrhythmia.A genetically based alteration in certain cardiac (hERG) potassium channels which is blockade by ibogaine predisposes the patient for serious QT intervalprolongation, serious arrhythmias, and sudden cardiac arrest (Fig 1).. Cardiac toxicity to noribogaine is thought to be similar to ibogaine [18].
4. Salvinorin A
Salvinorin Ais an active constituent of sage, Salvia divinorum. Structurally, it is not an alkaloid. It does not affect the 5-HT serotonin receptor,)[19].
Mechanism of action
Salvinorin A is acting as a selective agonist of the kappa-opioid receptor (KOR). It retains its anti-addictive property of traditional kappa-opioid receptor agonists with many enhancements such as decreased side effects. Many studies showed that salvinorin A can modify the dopaminergic pathway via decreased dopamine levels in the caudate-putamen and dopamine neurotransmission levels in the dorsal striatum, basically by regulating the release of dopamine instead of its uptake[19, 20].
Lake of studies on human & limitations
At present, there are no studies regarding the therapeutic usage of salvinorin A on humans its intense hallucinatory effects (accompanied by dissociation, dysphoria, and motor effects) represented a major limitation of its use in humans[19].
It is metabolized by CYP450 and has a very short half-life of about 75 min [20].
f) Non psychedelic natural products
Thymoquinone (TQ)
It is one of the main bioactive ingredients of Nigella Sativa, family Ranunculaceae TQ possess protection against oxidative stress, inflammation, and infections. and, neuroprotective effect. It exhibited beneficial effects against toxin-induced neuroinflammation and neurotoxicity[21].
In the animal model, TQ attenuated the development of tramadol tolerance and dependence. El-Shamy et al. (2013 A study also reported that Nigella sativa possesses the ability to modulate neurotransmitters release and reuptake (dopamine, serotonin, gamma-aminobutyric acid, and acetylcholine and gives a beneficial effect on the decrease of drug tolerance[22]).
Safety and limitation of Psychedelics
A comprehensive study of risk and safety matters was described by Johnson and colleagues [23]. Here we abstract a brief description.
1. Potential adverse effects
Classical hallucinogens may be used in unsafe ways, but they normally do not impose addiction. Psychosis, though it is rarely observed in medical places. classical hallucinogen has very minimum physiological toxicity.
No evidence of neuropsychological deficits or damage of organ the most important concern was the anxiety and fear,[24][2].
2. Safeguards against risks
Screening for a history of psychiatric behavior; administration under medic observation and availability of measures for the management of any cardiovascular abnormality may improve the Risk/ benefit ratio.[2, 23]
III. CONCLUSIONS
Using some natural psychedelics for example DMT for management of drug addiction is a very promising approach and research should be encouraged to optimize their clinical utilization. More work needs to be done on mechanisms of action, e.g., psychological mediators and persisting psychological change, neuroimaging studies of persisting effects, other biomarkers, and the possible role of genetics in moderating response to psychedelics should be manipulated. Conclusively, as all the drugs have some associated risks, constant care of safety for the patient is important, including the optimization of screening, preparation, debriefing, and follow-up sessions.



