
Loading menu…

Should We Change the Therapeutic Algorithm of Type 2 Diabetes Based on Accumulating Evidence?

§ Endocrinology unit, Internal Medicine Department, Sc...
‡ Nephrology unit, Internal Medicine Department, Schoo...
Rheumatology and Rehabilitation Department, School o...

Send Message

To: Author

Should We Change the Therapeutic Algorithm of Type 2 Diabetes Based on Accumulating Evidence?

Article Fingerprint

ReserarchID

097P8

Should We Change the Therapeutic Algorithm of Type 2 Diabetes Based on Accumulating Evidence? Banner

Key Research Insights

Synthesized scholarly intelligence & interactive research assistant
  • English
  • Afrikaans
  • Albanian
  • Amharic
  • Arabic
  • Armenian
  • Azerbaijani
  • Basque
  • Belarusian
  • Bengali
  • Bosnian
  • Bulgarian
  • Catalan
  • Cebuano
  • Chichewa
  • Chinese (Simplified)
  • Chinese (Traditional)
  • Corsican
  • Croatian
  • Czech
  • Danish
  • Dutch
  • Esperanto
  • Estonian
  • Filipino
  • Finnish
  • French
  • Frisian
  • Galician
  • Georgian
  • German
  • Greek
  • Gujarati
  • Haitian Creole
  • Hausa
  • Hawaiian
  • Hebrew
  • Hindi
  • Hmong
  • Hungarian
  • Icelandic
  • Igbo
  • Indonesian
  • Irish
  • Italian
  • Japanese
  • Javanese
  • Kannada
  • Kazakh
  • Khmer
  • Korean
  • Kurdish (Kurmanji)
  • Kyrgyz
  • Lao
  • Latin
  • Latvian
  • Lithuanian
  • Luxembourgish
  • Macedonian
  • Malagasy
  • Malay
  • Malayalam
  • Maltese
  • Maori
  • Marathi
  • Mongolian
  • Myanmar (Burmese)
  • Nepali
  • Norwegian
  • Pashto
  • Persian
  • Polish
  • Portuguese
  • Punjabi
  • Romanian
  • Russian
  • Samoan
  • Scots Gaelic
  • Serbian
  • Sesotho
  • Shona
  • Sindhi
  • Sinhala
  • Slovak
  • Slovenian
  • Somali
  • Spanish
  • Sundanese
  • Swahili
  • Swedish
  • Tajik
  • Tamil
  • Telugu
  • Thai
  • Turkish
  • Ukrainian
  • Urdu
  • Uzbek
  • Vietnamese
  • Welsh
  • Xhosa
  • Yiddish
  • Yoruba
  • Zulu
Reading Preferences
Font Size
Line Spacing
Background
This converted HTML version may contain rendering inconsistencies. Please refer to the PDF for the authoritative version, or click here to provide feedback.

Abstract

In the last two decades, a dramatic shift in the paradigm of management of type 2 diabetes has been settled. Reduction of diabetic complications became the primary target instead of focusing on the mere glycemic control. The tight blood sugar control among type 1 (T1DM) and type 2 (T2DM) diabetes mellitus patients aimed at avoidance of long- term complications of diabetes. In spite of the significant impact of this approach on the incidence of these complications, the outcome is still not satisfactory. The frequent failure to achieve tight blood sugar control and the lack of hypoglycemic agents that are capable to combat the underlying pathogenic mechanisms of diabetic complications underlie this unsatisfactory outcome. These drawbacks are overcome in the newly introduced hypoglycemic agents. In this review, we are going to discuss these mechanisms and highlight the therapeutic value of the early use of these agents instead of the long-standing traditional approach.

I. INTRODUCTION

Diabetes mellitus is a pandemic disease that has exponentially increasing prevalence. In 1980, 108-million persons had diabetes worldwide while in 2014, 430-million persons were affected [1]. In spite of the increased awareness about this disease and the worldwide efforts to give optimum care, 3.7 million diabetic patients lost their lives in 2012 because of diabetes and its complication [2]. This figure exceeded 5 million deaths annually in the last few years [3]. The hazard of cardiovascular mortality among diabetic patients is 2.3 folds that in non-diabetic personnel [4]. The average life span of the diabetic patients is 10-15-years shorter than non-diabetic subjects [5]. Besides, diabetes is the cause of many disabling Besides, diabetes is the cause of many disabling morbidities. In spite of the optimal management of the established cases of diabetic retinopathy that reduces the risk of visual loss by 60%, diabetes remains the leading cause of blindness among working-age adults worldwide [6]. Diabetes is the leading cause of non-traumatic lower-extremity amputation [7]. Diabetic peripheral neuropathy (PN) is the most frequent cause of sensory neuropathy [8]. Diabetic kidney disease (DKD) is the most common cause of end-stage renal disease (ESRD). One-third of T1DM develop ESRD, while only 10-20% of type 2 diabetes mellitus (T2DM) patients progress to ESRD [9, 10]. The prevalence of congestive heart failure (CHF) among diabetic patients aged 55 to 64 years is 5.5 folds the prevalence among nondiabetic personnel of the same age [11]. Diabetes is an independent risk factor for the development of ischemic heart disease (IHD). CHF and IHD are the commonest causes of death in T1DM and T2DM patients [12]. Diabetes mellitus confers a high risk of cerebrovascular stroke [13]. Endothelial dysfunction is a common pathology underlying the etiopathogenic mechanism of all these complications [14]. This endothelial dysfunction is a sequel to many metabolic changes encountered in hyperglycemic personnel. These metabolic changes include increased oxidative stress [15], hyperuricemia [16], stimulation of sodium hydrogen exchangers (NHE) [14], and stimulation of renal sodium glucose transporters (SGLT) [17].

Twenty-five years ago, the Diabetes Control and Complications Trial (DCCT) research group announced 50% reduction of microvascular complications among T1DM patients in the tight blood sugar control group compared to poorly controlled cases [18]. Five years later, the United Kingdom Prospective Diabetes Study (UKPDS) group announced similar findings among T2DM patients [19]. However, tight blood sugar control only had a marginal impact on cardiovascular disease and all-cause mortality among diabetic patients [20]. Additionally, blood sugar control using sulphonylurea compounds and insulin carries increased risk of severe hypoglycemia and weight gain [18,19]. IN UKPDS study, T2DM patients allocated to metformin had 32% reduction for any diabetes-related endpoint, 42% for diabetes-related death, and 36% for all-cause mortality when compared with those prescribed sulphonylurea or insulin [21]. These favorable effects of metformin were attributed to body weight reduction and the almost absence of hypoglycemic attacks. According to these results and others, the American College of Endocrinology (ACE), and the American Association of Clinical Endocrinology (AACE) recommend that the choice of anti-diabetic therapies must depend on many attributes that include antihyperglycemic efficacy; risk of inducing hypoglycemia; and risk of weight gain [22]. The last 15 years have witnessed the introduction of three new hypoglycemic agents, namely, glucagon-like peptide-1 receptor agonists (GLP-1RA), dipeptidyl peptidase 4 inhibitors (DPP4Is), and sodium glucose co-transporter-2 inhibitors (SGLT2Is). These three agents carry unique features, namely, the minimal incidence of hypoglycemic events and the favorable impact on body weight. GLP-1RA and SGLT2Is are associated with body weight reduction, while DPP4Is are weight neutral [23, 24]. Compared to older hypoglycemic agents, these newer groups carry potential favorable protective effects on endothelium, and can significantly reduce adverse cardiovascular events of diabetes in case of SGLT2Is and GLP-1RA, and are reno-protective. SGLT2Is may also prevent or withhold diabetic retinal complications [25]. This review will highlight the possible new strategy to prevent the development and progression of diabetic complications, the main target of this disease management.

a) The Endothelium in Diabetes

The first report on the role of the endothelium as an important regulator of local vascular tone was in 1980 [26]. The vascular endothelium is an important component of diabetic complications. Endothelial dysfunction is eminent not only in diabetic patients but also in patients suffering obesity or metabolic syndrome. Decreased synthesis of nitric oxide (NO), a potent vasodilator, is the salient feature of endothelial dysfunction. Decreased NO underlies insulin resistance by reducing insulin access to target cells [27]. Insulin has also to cross endothelial cells to reach target tissues [28, 29]. Hyperglycemia can lead to endothelial mitochondrial fragmentation and increased production of reactive oxygen species (ROS) [30]. Increased endothelial ROS is associated with increased breakdown of NO [31]. Impaired endothelial function was demonstrated within visceral fat [32], cardiac and skeletal muscles [33]. Endothelial dysfunction is associated with accelerated atherosclerosis in an animal model [34], diabetic retinopathy [35], nephropathy [36], neuropathy [37], and cerebral dysfunction [38]. To affirm the role of endothelial dysfunction in the development of diabetic nephropathy, two separate studies have disclosed that endothelial nitric-oxide synthase (eNOS) deficient mice robustly develop diabetic nephropathy [39, 40].

b) Sodium Hydrogen Exchangers

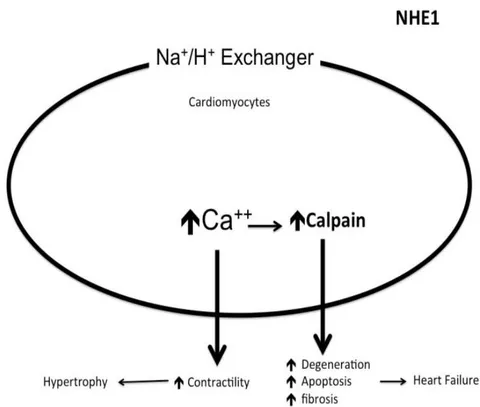
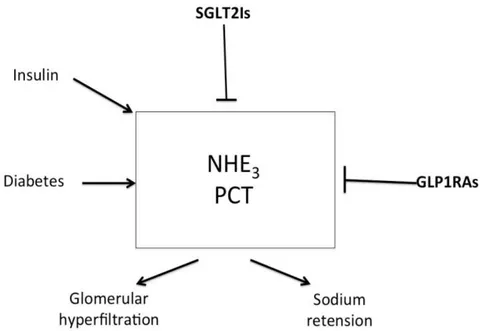
The sodium hydrogen exchangers (NHE) are trans-membrane ion channels that are responsible for intracellular pH regulation through the extrusion of hydrogen in exchange with sodium influx [Fig. 1]. NHE exist in nine isoforms [41, 42]. NHE1 is present on the surface of endothelium, vascular smooth muscle cells (VSMCs), cardiomyocytes and platelets, while in case of renal tubular and intestinal epithelium NHE3 is encountered. Activation of the NHE1 within endothelium, VSMCs, and cardiomyocytes may underlie microvascular and macro-vascular complications of diabetes. It can also have a role in insulin resistance and systemic hypertension. These exchangers cause increased sodium influx that stimulates sodium-calcium exchanger with consequent increase of intracellular calcium. Within endothelium, increased cytoplasmic calcium inhibits eNOS and thus decreases NO synthesis (Fig. 2). Increased intracellular calcium is also associated with increased intracellular and mitochondrial activity of calpain, the cysteine protease, that can damage the inner mitochondrial membrane, a process that ends with cell apoptosis [43]. Activation of NHE1 in diabetic patients is a consequence of high blood glucose, insulin, angiotensin, or adipokines [44]. Endothelial NHE1 activation increases the influx of calcium into the cytoplasm and mitochondria associated with increased calpain enzyme activity. These changes lead to endothelial dysfunction and senescence. The development of systemic hypertension, increased insulin resistance, diabetic retinopathy, nephropathy, and neuropathy are consequences of decreased eNOS activity and accelerated endothelial senescence. It can also explain the increased frequency of vascular calcification, peripheral vascular disease, and diabetic cerebrovascular dysfunction [45]. Mitochondrial injury is associated with impaired antioxidant defense [46]. Inhibition of NHE1 using cariporide was associated with increased NO release; eNOS activity simultaneously decreased ROS production, decreased nuclear factor-κB (NF-κB) activation and decreased the production of tumor necrosis factor-α and intercellular adhesion molecule-1 [47]. Increased intracellular calcium induced by NHE1 isoform on the surface of cardiomyocytes leads to cardiac hypertrophy. Peripheral coronary ischemia secondary to endothelial dysfunction can further activate cardiac NHE1. Active NHE1 increases intracellular and intra-mitochondrial calpain that contributes to degeneration, apoptosis, and fibrosis of myocardium [44] [Fig. 3]. Activation of renal NHE3 within PCT and ascending loop of Henle causes sodium retention and can thus contribute to the development of systemic hypertension in diabetic patients [44, 48] [Fig. 4]. Activation of NHE1 on the surface of platelets plays a significant role in platelet activation. This effect is mediated through increased intracellular calcium and can contribute to the pro-coagulant state in diabetes [49]. Accordingly, activation of NHE1 on the surface of endothelial cells, VSMCs, platelets, and cardiomyocytes beside the activation of renal NHE3 share in the pathogenesis of systemic hypertension, microvascular complications and macrovascular complications of diabetes that finally result in heart failure and ESRD.
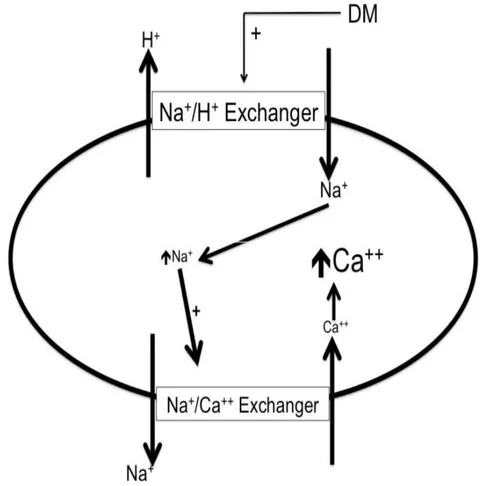
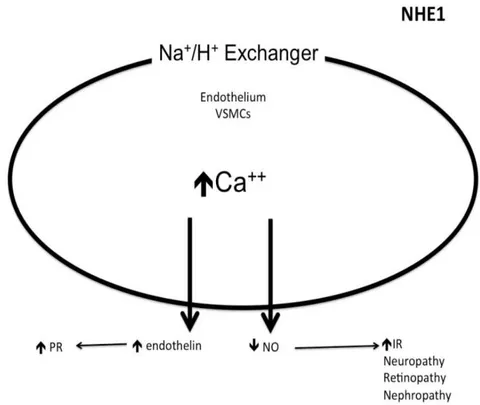
Fig. 1: Diabetic state increases the activity of the sodium/hydrogen exchanger on the surface of endothelial cells, vascular smooth muscle cells, cardiomyocytes, and tubular epithelial cells. Consequently, intracellular and mitochondrial calcium.
Fig. 3: Increased cytosolic calcium within the cardiomyocytes leads to ventricular hypertrophy, and increased activity of the digestive enzyme calpain. This lysolethicin digests mitochondrial membranes and results in myocardial damage that finally leads to heart failure.
Fig. 4: Increased activity of NHE3 isomer within the proximal convoluted tubules increases sodium absorption from the lumen of these tubules in exchange with the secreted hydrogen. Decreased sodium delivery to the distal nephron segments results in glomerular hyperfiltration. Diabetic state and insulin administration increase NHE3 activity while SGLT2Is and GLP1RAs inhibit it. NHE=sodium hydrogen exchanger; SGLT2Is= sodium glucose transporter-2 inhibitors; GLP1RAs= glucagon like peptide receptor agonists.

c) Oxidative stress

Increased oxidative stress is one of the metabolic disorders encountered in diabetes. Diabetic patients have overproduction of free oxygen radicals and decreased wash out of these radicals. Increased production of free oxygen radicals is the sequel to increased activity of nicotinamide adenine dinucleotide phosphate (NADPH) oxidase [50, 51], cyclo-oxygenase [52], and lipoxygenase [53] enzymes. Hyperglycemia stimulates all these enzymes. Sodium-glucose cotransporter 2 (SGLT2) within the brush border of the proximal convoluted tubular epithelium (PCT) is another pathway of free oxygen radicals' overproduction. Increased intracellular uric acid (UA) induces NADPH oxidase [54]. Mitochondrial damage results in impaired antioxidant defense [46]. Increased free oxygen radicals activate NF- κ B [55]. When NF- κ B is free from its inhibitor, it translocates from the cytoplasm to the nucleus where it triggers the genes encoding transforming growth factor- β 1 (TGF- β 1), and monocyte chemo attractant protein-1 (MCP-1) and Intercellular Adhesion Molecule 1 (ICAM1) [56-58]. Reactive oxygen species (ROS) stimulate overproduction of protein kinase C (PKC) and mitogen-activated protein (MAP) kinase within mesangial cells (MCs) and pericytes. All these factors stimulate overproduction of extracellular matrix proteins [59].

d) Uric acid

Serum uric acid (UA) is a strong predictor for the development of proteinuria in T1DM patients. The risk for proteinuria increases by 80% with every 1mg/dL rise in serum UA [60]. The risk of decline of glomerular filtration rate (GFR) is significantly higher (2.4 folds) in T1DM patients with serum UA>6.6 mg/dL when compared with candidates with lower level [61]. In T1DM patients followed-up for more than 18 years, serum UA was an independent predictor of overt proteinuria [62]. In T2DM patients, 68% of the hyperuricemic versus 41.5% with normal serum UA had diabetic nephropathy (DN) [63]. Further prospective studies confirmed the increased risk of development of proteinuria and accelerated decline of GFR among hyperuricemic T2DM [64, 65]. Serum UA>7mg/dL in males and >6mg/dL in females were associated with a higher rate of DN progression, and overall mortality among T2DM patients that have the disease for fifteen years or more [66]. Treatment of T2DM patients suffering DN and high serum UA with allopurinol was associated with a significant decrease of urine albumin excretion (UAE) and serum creatinine and a significant increase of GFR over three years of follow-up [67]. A recent meta-analysis of 19 randomized controlled trials has confirmed the significant favorable effect of urate-lowering therapy on the rate of GFR decline. These 19 trials enrolled 992 patients [68].

Increased level of Serum UA is associated with endothelial dysfunction. High mobility group box chromosomal protein 1 (HMGB1) is a pro-inflammatory mediator synthesized and secreted by activated phagocytes or monocytes. When secreted extracellular, HMGB1 can interact with the receptor for advanced glycation end products (RAGE), inducing the production of multiple cytokines, and the induction of vascular adhesion molecules [69]. In a recent in vitro study, high UA concentration inhibited eNOS expression and NO production in human umbilical vein endothelial cells (HUVECs), increased extracellular HMGB1 secretion, up-regulated RAGE expression, activated NF- κ B, and increased the level of inflammatory cytokines. Blocking RAGE significantly suppressed the DNA binding activity of NF- κ B and the levels of inflammatory cytokines [70]. HighserumUA is also a significant predictor of systemic hypertension [71].

e) Role of glucagon like peptide-1 receptor agonists (GLP-1RA)

Glucagon-like peptide-1 (GLP-1), is a peptide hormone secreted by the neuro-endocrine cells within the mucosa of the small intestine [72]. In healthy individuals, GLP-1 activates insulin secretion, inhibits glucagon secretion and slows gastric emptying and controls apetite [72]. The susceptibility of this peptide hormone to enzyme breakdown by the dipeptidyl peptidase-4 enzyme (DPP-4) is responsible for the very short plasma half-life of GLP-1. It cannot be used therapeutically except as continuous intravenous infusion [73]. GLP-1RA are exogenous GLP-1 analogues with variable sequence similarity to the human GLP-1 [74]. The variability involved mainly two sites in the GLP-1 molecule susceptible to cleavage by DPP4; namely, alanine and lysine at positions 8 and 34 respectively. These changes, beside other modifications, have helped to find out many peptides that simulate GLP-1 action but with longer half-life [73]. GLP-1RAs were found to decrease body weight, and some cardiovascular morbidity, without increasing the risk of hypoglycemia [75]. Robust indications for GLP-1RAs in T2DM patients not responding to metformin monotherapy, dual therapy, or insulin include overweight, inability to control appetite, high risk of cardiovascular disease, and the need of high doses of insulin [73]. The use of GLP-1 RAs can also lower systolic, and to a minor degree, diastolic blood pressure [76]. However, long term use of GLP-1 RAs was frequently reported to be associated with increased heart rate [76, 77]. The current evidence does not support any beneficial effect of GLP-1RAs in patients with heart failure and/or impaired ventricular function [78, 79]. The Evaluation of Lixisenatide in Acute Coronary Syndrome (ELIXA) trial was the first cardiovascular outcome trial (CVOT) of GLP-1RAs in T2DM. Based on this trial, treatment with lixisenatide in addition to conventional therapy had no impact on the cardiovascular risk in patients with T2DM and recent acute coronary syndrome [80]. In the Liraglutide Effect and Action in Diabetes: Evaluation of Cardiovascular Outcome Results (LEADER) trial, that appeared in 2016, liraglutide use significantly decreased mortality from any cause and cardiovascular events in patients with T2DM at high risk for cardiovascular events. The benefit of liraglutide treatment is more pronounced patients with eGFR <60 mL/min/1.73 m2 and patients aged 50 years or more. In spite of these benefits, hospitalization rate for heart failure was not different between liraglutide and placebo groups [81]. Although the incidence of retinopathy was similar in this trial, the chance of development of nephropathy was significantly lower in patients treated with liraglutide [81]. In SUSTAIN-6 trial, semaglutidewas associated with a significant decrease in the incidence and progression of nephropathy. However, a higher percentage of patients in semaglutide group developed retinopathy. Semaglutide was also associated with a 26% reduction in the hazard of cardiovascular mortality, non-fatal myocardial infarction, or nonfatal stroke [82]. In EXSCEL trial, extended release exenatide failed to show favorable cardiovascular impact [83]. This result could be due to the broader T2DM population studied in EXSCEL trial as regard to age and cardiovascular risk, the shorter follow-up period, the lower HbA1c levels and the concomitant hypoglycemic treatment (SGLT2Is were frequently used in the placebo group) [84]. A meta-analysis including nine randomized trials with dulaglutide in 6010 T2DM patients has shown that 0.67% of patients treated with dulaglutide vs. 1.18% of the placebo group developed one of the endpoints. This difference was not significant [85].

Other glucose-independent effects of GLP-1RAs include favorable effects on blood pressure, dyslipidemia, inflammation, and fibrosis. Through inhibition of renal NHE3, GLP-1RAs can promote natriuresis and diuresis. Additional effects include inhibition of the intrarenal renin-angiotensin system, inflammation, and apoptosis. The mechanism of these effects is still not recognised. Recent studies suggest important antioxidant and anti-apoptotic activities of GLP-1RAs [86] [Fig. 5].
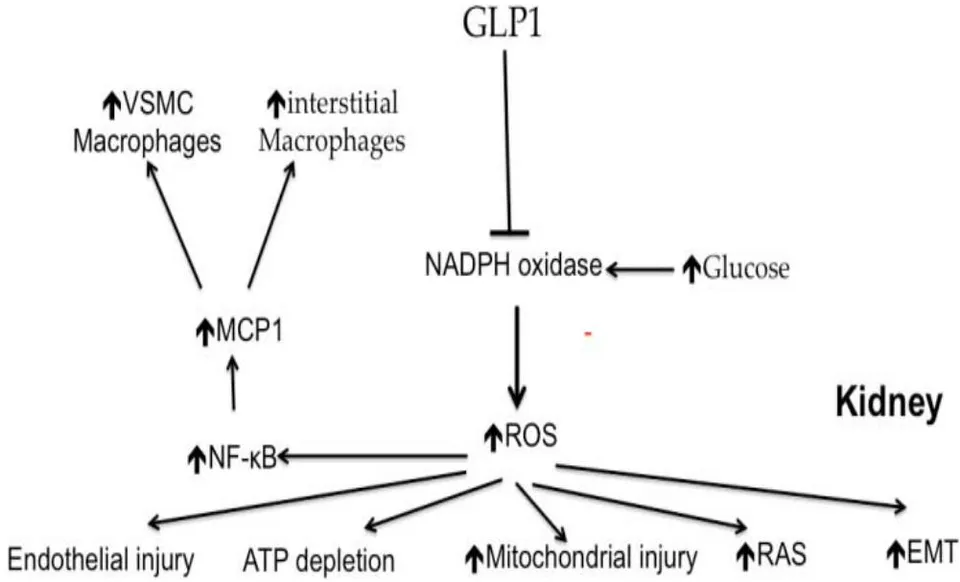
Fig. 5: Hyperglycemia stimulates NADPH oxidase enzyme within different organs including the kidney. Consequent increased production of free oxygen radicals results in increased cascade of degenerative and inflammatory processes that underlie pathology of the diabetic kidney. Glucagon like peptides inhibit NADPH oxidase and thus can muffle development or progression of diabetic nephropathy. GLP1= Glucagon like peptides; NADPH= nicotinamide adenine phosphate; ROS= reactive oxygen species; NF-κB- nuclear factor kappa B; MCP1= macrophage chemo attractantfpeptide; VSMCs=vascular smooth muscle cells; ATP=adenosine triphosphate; RAS= renin-angiotensin system; EMT= epithelial mesenchymal transition.

f) Dipeptidyl peptidase 4 inhibitors

The discovery of non-enzymatic functions for DPP4 within the kidney has attracted the attention for the reno-protective action of this hypoglycemic agent especially after disclosure of the antiproteinuric effect of saxagliptin in T2DM patients during "Saxagliptin Assessment of Vascular Outcomes Recorded in Patients with Diabetes Mellitus - Thrombolysis in Myocardial Infarction 53" (SAVOR-TIMI 53) trial [87-91]. Experimental pharmacologic and genetic inhibition of DPP4 had also proven efficacy in preventing progressive renal damage in animal models of acute and chronic kidney disease [92, 93].

The glucose-lowering action of DPP4Is is through inhibition of breakdown of endogenous GLP and glucose-dependent insulinotropic peptide (GIP). These incretins improve the sensitivity of pancreatic β cells to glucose [94]. DPP4 exists in 2 forms; membrane-bound and soluble forms [95]. Membrane-bound DPP4 is present on the cell membrane of epithelial cells in the kidneys, lungs, and small intestine. It also exists on endothelial, and immune cells [96-98]. DPP4 on the surface of immune cells is also known as cluster of differentiation 26 (CD26) [97, 98]. The soluble form (sDPP4) is the consequence of shedding of the membrane-bound form. sDPP4 level increases in obese subjects and T2DM patients and may participate in increased insulin resistance in these cases [99]. Membrane-bound DPP4 expression is triggered in case of hypoxia as well as its' shedding [100,101].

Within the kidney, DPP4 in S1-S3 segments of the proximal convoluted tubules (PCT) are linked to NHE3 and plays a role in salt and water retention through stimulation of this exchanger, NHE3 activity decreases on inhibition of angiotensin II synthesis by captopril [102], or inhibition of DPP4 [103]. Angiotensin II inhibits megalin receptor endocytosis protein expression. This process is reversed by DPP4Is [104]. Treatment with DPP4 inhibitors may reverse reduced uptake of albumin and other low molecular weight proteins by PCT [105]. DPP4 was also discovered on the glomerular endothelium and the base of the foot processes of podocytes [106]. DPP4 is expressed on T-cells, B-cells, macrophages, and dendritic cells in the kidney [98]. Stimulation of DPP4 on the surface of different immune and inflammatory cells may mediate inflammation within the kidney in diabetic patients. DPP4Is decrease inflammation in diabetes. This finding suggests inflammation as an eminent player in DPP4-mediated kidney injury [107].

However, in spite of the reduction in urine albumin excretion observed in 3 randomized controlled studies (RCT) in T2DM patients treated with DPP4Is [108-110], the only study that specifically looked for the anti-proteinuric effect of linagliptin failed to find a significant impact [111]. Moreover, DPP4Is failed to have a significant impact on doubling of serum creatinine, change in GFR, or ESRD [108-110]. On the other hand, administration of linagliptin to T2DM patients that had renal dysfunction and were prescribed ACE inhibitors or ARBs has led to additive significant reduction in albuminuria [112].

In normoglycemic milieu, microRNA-29 (miR29) suppresses DPP4 gene. In hyperglycemic state, this suppression is lost. As a consequence, cell surface DPP4 activity increases [113]. In diabetic mice, activated endothelial DPP4 induces phosphorylation of adjacent integrin β1 on the surface of the endothelium. The activated DPP4, together with the phosphorylated integrin β1 form a complex that up-regulates TGF β receptor and activates the surface vascular endothelial growth factor receptor type 1(VEGFR1). Up-regulated TGF β receptor and VEGFR1 stimulate endothelial-mesenchymal transition (EndMT) that increases transition to fibroblasts with subsequent increased fibrogenesis [114] [Fig.6]. However, the lack of significant impact of DPP4Is on GFR in human studies would cast doubts on their favorable effect on renal fibrosis in humans.

The effect of DPP4Is treatment on the retina is debatable. While some investigators reported an increase in retinal endothelial leakage and vascularity [115], others have reported a significant reduction in the risk of diabetic retinopathy progression [116].

The lack of the expected favorable effect of DDP4Is on diabetic microvascular and macrovascular complications of diabetes in spite of the proven molecular and experimental mechanisms can be attributed to potentiation of the stem cell chemokine, stromal cell-derived factor-1 (SDF-1), which promotes inflammation, proliferation and neovascularization [117]. SDF-1 enhances atheromatous plaque growth and instability, cardiac inflammation, and fibrosis [118]. The renal effects of DPP4Is are mainly through potentiation of SDF-1 leading to podocyte injury and glomerulosclerosis. SDF-1 also induces natriuresis in the distal tubules, contrary to SGLT2Is and NHE3 inhibitors that act on PCT. Hence, SDF-1 cannot utilize tubuloglomerular feedback to modulate the glomerular hyperfiltration [117,119] [Fig.7]. SDF-1 may also aggravate both retinopathy and neuropathy [117,120].

g) Sodium glucose co-transporters inhibitors

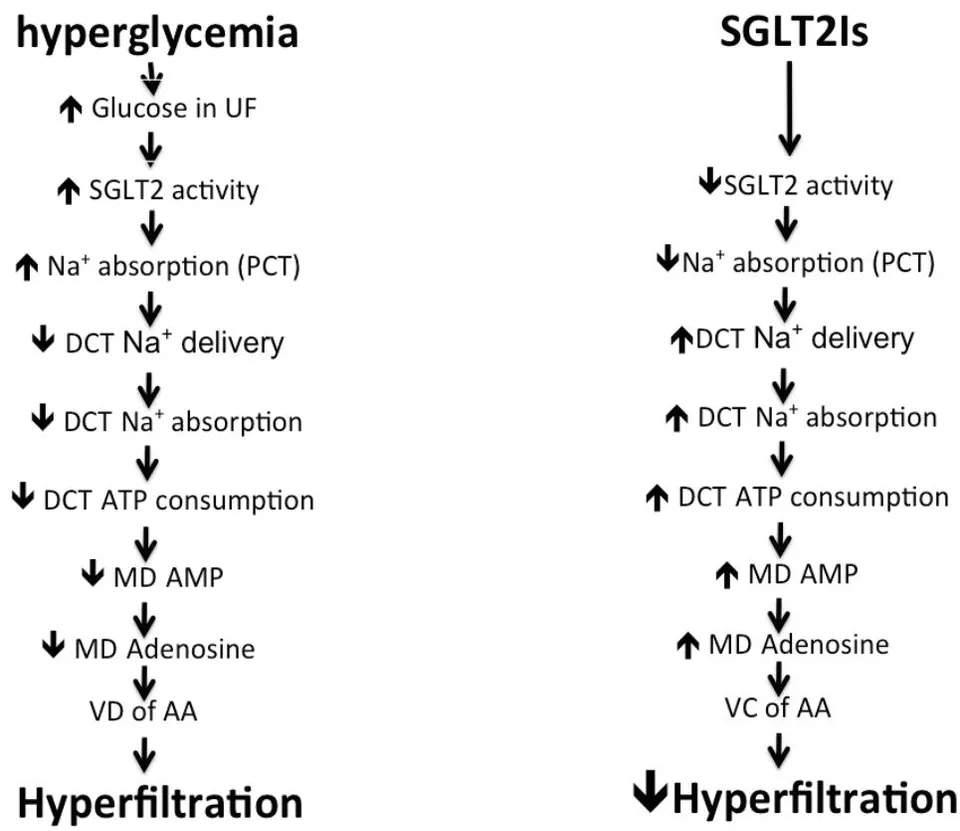
SGLT2Is constitute a recently introduced group that has insulin independent hypoglycemic effect. Three members of this group, namely empagliflozin, canagliflozin, and dapagliflozin are FDA approved and are now used worldwide. By inhibiting the upregulated SGLT2 co-transporters in the brush border of the S1 segment of the PCT, SGLT2Is can reduce the renal threshold for plasma glucose from 196 to 22 mg/dL, thereby enhancing urinary excretion of glucose [121]. They also increase distal sodium delivery and hence distal tubular sodium absorption. Increased adenosine triphosphate (ATP) consumption during sodium absorption with a consequent increase of adenosine production, causes afferent arteriolar vasoconstriction and fall in renal blood flow, reverses hyperfiltration, and accordingly reduces renal injury [Fig. 8]. In addition, SGLT2Is exert other beneficial effects, including reductions in body weight, serum UA, and blood pressure [122]. Excess glucose within the tubular lumen triggers the uric acid transporter GLUT9 within the S3 segment of the PCT and in the collecting duct to excrete UA in exchange with glucose [123]. The antihypertensive effect of SGLT2Is is related to volume depletion, loss of body weight, inhibition of endothelial NHE1 and renal NHE3, and reduction in serum UA [71].
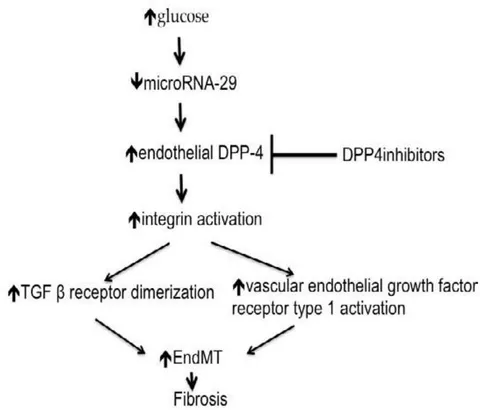
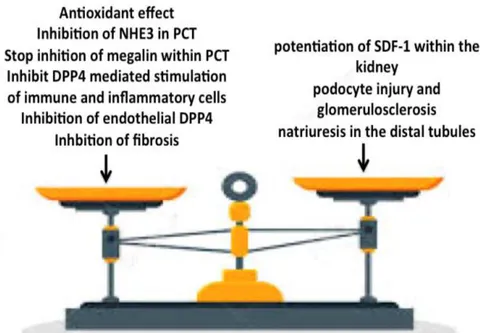
Fig. 6: MicroRNA-29 is a natural inhibitor of endothelial DPP-4 within renal vasculature. Hyperglycemia inhibits microRNA-29 and thus stimulates endothelial DPP-4. DPP-4= dipeptidyl peptidase; TGF= transforming growth factor; EndMT= endothelial mesenchymal transition.
Fig. 7: The beneficial effects of DPP4Is on the kidney are muffled by the bad effect induced by stromal cells derived factor 1(SDF-1). DPP-4= dipeptidyl peptidase; TGF= transforming growth factor; EndMT= endothelial mesenchymal transition.

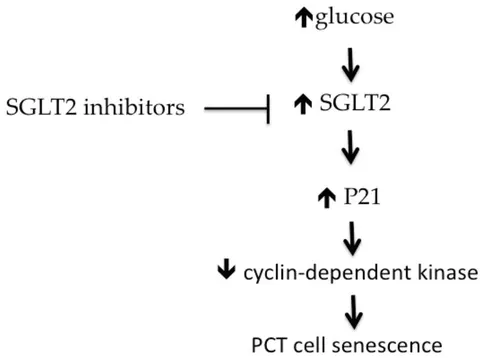
SGLT2Is not only decrease serum UA but they can decrease intracellular fructose metabolism and UA synthesis in the PCT epithelium [124]. Intracellular UA is pro-oxidant. It stimulates NADPH oxidase enzyme activity with consequent increase in production of ROS. This leads to premature senescence of these cells, activation of the renin-angiotensin system, epithelial-mesenchymal transition, and activation of the inflammatory cascade through activation of NF- κ B [125-127] [Fig. 5]. Cyclin-dependent kinase (CDK) inhibits cell senescence. P21 is an inhibitor of CDK and thus promote cell senescence. Hyperglycemia induces P21 while SGLT2Is inhibit this factor within PCT cells [128,129] [Fig. 9]. SGLT2Is also dampen the expression of Toll-like receptor-4, the binding of nuclear DNA for activator protein 1, the increased collagen IV expression as well as the increase in interleukin-6 secretion and interstitial macrophage infiltration induced by hyperglycemia within the renal parenchyma [130]. Moreover, fibrotic and inflammatory genes are suppressed within the diabetic kidney by SGLT2Is [131,132].

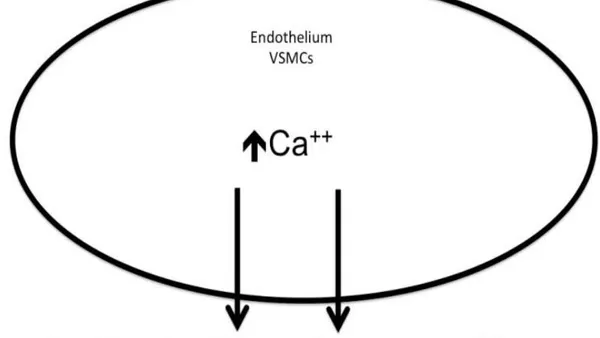
Fig. 2: Increased cytosolic calcium leads to decreased nitric oxide synthesis and increased secretion of endothelin. Increased vascular smooth muscle tone leads to increased peripheral resistance and decreased tissue perfusion. This leads to decreased insulin delivery. Endothelial damage induced by calcium can also decrease permeability of the endothelium to the delivered insulin. Decrease nitric oxide production has a role in pathogenesis of neuropathy, retinopathy and nephropathy PR= peripheral resistance; IR= insulin resistance.
Fig. 8: Mechanism of hyperfiltration induced by hyperglycemia and how do SGLT2Is control it. UF= ultrafiltrate; SGLT= sodium glucose transporter; Na ^{+} = sodium; PCT= proximal convoluted tubules; DCT= distal convoluted tubules; ATP= adenosine triphosphate; MD= macula densa; AMP= adenosine monophosphate; VD= vasodilatation; AA= afferent arteriole; VC= vaso-constriction. Fig. 9: Activation of SGLT2 in diabetic patients leads to over activity of P21, the natural inhibitor of Cyklin-dependent kinase 2. This kinase enzyme inhibits cell senescence. By inducing P21, diabetic patients suffer increased proximal tubular epithelium senescence. Through inhibition of SGLT2, SGLT2Is ptotect proximal tubular epithelial cells against increased senescence. SGLT=sodium glucose transporter; PCT=proximal convoluted tubule.
Fig. 8: Mechanism of hyperfiltration induced by hyperglycemia and how do SGLT2Is control it. UF= ultrafiltrate; SGLT= sodium glucose transporter; Na + = sodium; PCT= proximal convoluted tubules; DCT= distal convoluted tubules; ATP= adenosine triphosphate; MD= macula densa; AMP= adenosine monophosphate; VD= vasodilatation; AA= afferent arteriole; VC= vaso-constriction. Fig. 9: Activation of SGLT2 in diabetic patients leads to over activity of P21, the natural inhibitor of Cyklin-dependent kinase 2. This kinase enzyme inhibits cell senescence. By inducing P21, diabetic patients suffer increased proximal tubular epithelium senescence. Through inhibition of SGLT2, SGLT2Is ptotect proximal tubular epithelial cells against increased senescence. SGLT=sodium glucose transporter; PCT=proximal convoluted tubule.

Through suppression of intracellular UA production, SGLT2Is inhibits renal gluconeogenesis. Intracellular UA stimulates adenosine monophosphate dehydrogenase (AMPD) enzyme and inhibits adenosine monophosphate kinase (AMPK) enzyme activities. Intracellular AMPD stimulates while AMPK inhibits gluconeogenesis [133]. In healthy personnel, the kidneys participate in endogenous glucose production.

In the fasting state, 20%–25% of endogenous glucose production takes place through renal gluconeogenesis. In T2DM, renal gluconeogenesis increases three fold [134].

Empagliflozin in the EMPA-REG trial achieved a 55% reduction of the chance of ESRD in T2DM patients with established cardiovascular disease, and an eGFR >30 mL/min/1.73m2. The median observation time in the EMPA-REG trial was 3.1 years[135]. In comparison, losartan treatment of a similar population with DN led to a 28% delay in the onset of ESRD during a mean follow-up of 3.4 years[136]. Empagliflozin treatment resulted in a 39% reduction of incident or worsening nephropathy, a 38% reduction in progression to overt albuminuria, and a 44% reduction in doubling of serum creatinine[137]. The favorable outcome of SGLT2Is is attributable to their effect on glomerular hyperfiltration, blood pressure, body weight, and serum UA in diabetic patients[137-139]. SGLT2Is also inhibit NHEs on the surface of cardiomyocytes, endothelial cells, and renal tubular epithelial cells. NHE inhibition can explain the distinguished cardioprotective and renoprotective actions of SGLT2Is[140-142]. Decreased renal blood flow induced by SGLT2Is is related to tubuloglomerular feedback and not related to RAS blockade. Empagliflozin and dapagliflozin increase plasma aldosterone and angiotensin II[143, 144], together with increased activity of urinary angiotensin converting enzyme and angiotensin converting enzyme2[145].

2-years treatment of T2DM patients (total of 1450 cases) already kept on metformin with either once-daily canagliflozin 100 mg, canagliflozin 300 mg, or glimepiride titrated to 6-8 mg resulted in eGFR decline by 0.5, 0.9, and 3.3mL/min/1.73m2/year respectively (P<0.01 for each canagliflozin group versus glimepiride) in spite of comparable reductions in HbA1c. UAE declined more with canagliflozin 100 mg or canagliflozin 300 mg than with glimepiride. These results further support that the renoprotective effect of SGLT2Is is independent of their glycemic effect [146]. Contrary to DPP4Is and sulfonylurea as that are significantly associated with increased risk of diabetic retinopathy, SGLT2Is were not associated with a higher risk of diabetic retinopathy than placebo among 100 928 patients with T2DM included in 37 independent randomized controlled trials with 1806 diabetic retinopathy events [147]. In the Canagliflozin Cardiovascular Assessment Study (CANVAS), 10 142 T2DM patients were assigned to canagliflozin or placebo. 34% of the patients had ≥2 risk factors for cardiovascular events but had no history of previous cardiovascular event (primary prevention cohort), while the remaining 66% had a positive history of cardiovascular event (secondary prevention cohort). The patients were randomly assigned in a ratio of 1:1:1 to either canagliflozin 100 mg, canagliflozin 300 mg or matching placebo. After treatment for a mean of 3.6 years, the primary endpoint (cardiovascular death, nonfatal myocardial infarction, or nonfatal stroke) has occurred less frequently with canagliflozin compared with placebo (26.9 versus 31.5/1000 patient-years; P=0.02). There was no statistical evidence of heterogeneity between the primary and secondary prevention cohorts. Renal outcomes were reduced by 40% and heart failure hospitalization was reduced by 33% in patients treated with canagliflozin [148,149]. 17,160 T2DM patients, including 6,974 with atherosclerotic cardiovascular disease, were assigned for 10 mg Dapagliflozin or placebo 1:1 ratio and were followed for a median of 4.2 years. Dapagliflozin decreased the composite of cardiovascular death or hospitalizations for heart failure in those with established atherosclerotic cardiovascular disease (ASCVD) and those with only multiple risk factors. The renal composite endpoint ( ≥ 40% decrease in estimated glomerular filtration rate to <60 mL per minute per 1.73 m 2 of body-surface area, new end-stage renal disease, or death from renal or cardiovascular causes) decreased by 24% in the Dapagliflozin group [150]. When patients with previous myocardial infarction (n = 3,584) were specifically looked for, adverse cardiovascular events were 16% less in the dapagliflozin arm [151]. According to these studies, SGLT2Isshould be prescribed aiming at cardiovascular protection in patients with T2DM and ASCVD [152].

T2DM patients suffering CKD and albuminuria (4400 patients) were randomly assigned to receive canagliflozin100 mg daily or placebo in 1:1 ratio. All the patients had an eGFR of 30 to <90 mL/minute/1.73 m2 and albuminuria (urine albumin/creatinine ratio>300 to 5000 mg/gm) that were receiving RAS blockers. The primary outcome was a composite of ESRD (dialysis, transplantation, or a sustained eGFR of <15 mL/min/1.73 m2), a doubling of the serum creatinine, or death from renal or cardio-vascular causes. The projected duration of the study was 5.5 years. Investigators of this study prematurely terminated the trial after a planned interim analysis on the recommendation of the data and safety monitoring committee. This analysis has shown a highly significant reduction of the primary composite endpoint by 34% in patients treated with canagliflozin after 2.6 years of treatment. Patients in the canagliflozin group also had a lower risk of ESRD, hospitalization for HF, and the composite of CV death, myocardial infarction, or stroke. These results indicate that canagliflozin may be an effective treatment for renal and cardiovascular protection in T2DM patients suffering CKD [153]. The observed benefits were obtained mainly in patients whose basal eGFR was between 30 and <60mL/min/1.73 m2. The hypoglycemic effect of SGLT2Is is almost lost when eGFR is lower than 45 mL/min/1.73 m 2. In addition, these findings were observed despite very modest differences in blood sugar, weight, and blood pressure between the placebo and the active treatment groups. This suggests that the mechanism of benefit is independent of glycemic control and is likely related to the reduction in single nephron hyperfiltration related to NHE3 inhibition.

The more recent results of the DECLARE – TIMI 58 have supported the favorable effects of SGLT2Is. In this last mentioned trial, 17160 type 2 DM patients were studied using dapagliflozin 10 mg versus placebo in 1:1 ratio for 4.2 years. 47.6% of these patients had GFR >90, 45.1% had GFR between 60 and 90, while only 7.4% of the patients had GFR < 60 ml/min/1.73m2. In addition, more than two thirds of the patients had normal urine albumin excretion. Contrary to CREDENCE trial patients where all patients were prescribed RAS blockers, only 81.3% of DECLARE study patients were on RAS blockers. The pre specified composite cardio-Renal end points (sustained decline of at least 40% in eGFR to less than 60 mL/min/1·73m2, end-stage renal disease (defined as dialysis for at least 90 days, kidney transplantation, or confirmed sustained eGFR <15mL/min per 1·73 m2), or death from renal or cardiovascular causes were significantly reduced by 24% in the dapagliflozin group while the prespecified composite renal end points (excluding the cardiovascular causes of death from the cardio-renal composite endpoints) decreased by 47%, and the chance to develop ESRD decreased by 56% in the dapagliflozin group. The significant impact of dapagliflozin was encountered in patients having baseline GFR >90, between 60 and 90, in normo-albuminuric patients, in patients with microalbuminuria and in those with overt proteinuria. We would like to emphasize that these favorable effects were only encountered in patients already maintained on either ACE inhibitors or ARBs [154].

h) Free oxygen radicals scavengers

Many preclinical studies have overwhelmed the role of reactive oxygen species (ROS) in the pathogenesis of diabetic complications. However, the less favorable outcomes of different antioxidants to prohibit the development or progression of diabetic complications in large clinical trials have dampened the enthusiasm for the use of antioxidant agents in diabetes [155]. Clinical studies using vitamin A, C, and E as antioxidant agents in pre-diabetic and T2DM patients were disappointing. Nuclear factor erythroid 2-related factor 2 (Nrf2) is a transcription factor that protects and restores cell homeostasis upon activation. Although Nrf2 is activated in response to hyperglycemia, this activation does not reach the sufficient level capable to combat the oxidative stress fueled by hyperglycemia [156]. Insufficient Nrf2 activity is often associated with the pathogenesis of diabetes and its complications [157]. Natural products can activate Nrf2, as a potential therapeutic target to control diabetic complications [157, 158]. Cruciferous vegetables, grapes, buckwheat, black tea, citrus fruits, apple peels, cinnamon, turmeric, Berberis Mahonia plant, kiwi fruits, the climbing plant Sinomenium acutum, garlic, and Bitter Melon are rich sources of different natural Nrf2 activators [159-162].

Consumption of 10 gms of broccoli sprouts powder, a rich source of sulforaphane, daily for four weeks was associated with significant improvement in insulin resistance in sixty-three T2DM patients [163]. In a double-blind trial in T2DM patients, the study candidates consumed oral 2×5 mg resveratrol (resveratrol group) or a placebo (control group) for four weeks. Resveratrol significantly decreased insulin resistance, and urine ortho-tyrosine/creatinine ratio as an index of ROS production [164]. A more recent study of ten T2DM subjects, daily consumption of 3 grams of resveratrol for 12 week has increased skeletal muscle Sirtuin1 and adenosine monophosphate kinase enzymes expression. These findings can further support the insulin sensitizing effect of resveratrol [165]. On the other hand, resveratrol supplementation over five weeks in fourteen T2DM patients already kept on diet control did not have a significant effect on glycemic control [166].

In seventy-five patients undergoing primary cardiovascular disease prevention, resveratrol-rich grape supplement significantly decreased high-sensitivity C-reactive protein, tumor necrosis factor- α, plasminogen activator inhibitor type 1, and increased anti-inflammatory interleukin-10. The authors concluded that 1-year consumption of a resveratrol-rich grape supplement improved the inflammatory and fibrinolytic activities in high cardiovascular risk and diabetic patients [167]. The beneficial anti-inflammatory effect of resveratrol-rich grape supplement was further supported in a later study of 35 T2DM male patients. One-year consumption of resveratrol-rich grape supplement down-regulated the expression of pro-inflammatory cytokines in circulating mononuclear cells [168]. However, a more recent and larger study failed to prove a significant impact of low (40 mg/day) and high doses (500 mg/day) used for 6 months on fasting blood sugar, glycated hemoglobin or c-reactive protein [169]. When 36 dementia-free, T2DM 49-78 years old patients consumed single doses of synthetic trans-resveratrol (75, 150 and 300 mg) at weekly intervals, trans-cranial Doppler ultrasound both before and 45 min after treatment had shown that only the 75 mg dose was efficacious to improve the cerebral vasodilator responsiveness in both middle and posterior cerebral arteries [170]. In addition, a single 75 mg dose of resveratrol was found to improve neurovascular coupling and cognitive performance in Thirty-six T2DM adults aged 40-80 years [171]. A more recent study has shown that a daily 100mg resveratrol supplementation for twelve weeks in 50 T2DM patients was associated with a significant decrease of arterial stiffness estimated by cardio-ankle vascular index [172].

When the endothelial function was assessed using digital volume plethysmography to measure the changes in the reflective index, oral intake of curcumin 150 mg twice daily for eight weeks has lead to a significant improvement in endothelial function [173]. Supplementation of twenty T2DM patients suffering overt proteinuria with 22mg of curcumin three times daily for two months significantly decreased urinary protein excretion and urine IL-8 beside serum levels of TGF- β and IL-8 [174]. Curcumin 500 mg three times daily was administered for nine months to 120 pre-diabetic patients and significantly improved insulin resistance and beta cell function with consequent prevention of diabetes [175]. Further studies supported the favorable anti-diabetic effect of curcumin [176-178].

i) Recommendations of diabetes associations

In October 2018, the European Association for the Study of Diabetes (EASD) and the American Diabetes Association (ADA) issued an updated consensus statement on management of hyperglycemia in T2DM patients. This consensus showed-up during the annual meeting of EASD in Berlin, Germany. In this consensus, patients with clinical CV disease should receive one of SGLT2Is or GLP-1RAs, while in patients with CKD or clinical HF and ASCVD, SGLT2Is should be considered [179]. The choice of diabetes therapies as recommended by the American Association of Clinical Endocrinologists (AACE) and American College of Endocrinology (ACE) must be individualized based on many attributes including the risk reduction in heart and kidney disease [180].

j) Novel markers of Diabetic complications

Mannose-binding lectin (MBL) is a recognized protein of the innate immune system. It is composed of a lectin (carbohydrate-binding) moiety attached to a collagenous moiety. MBL binds to a wide range of sugars that permits MBL to interact with a wide range of viruses, bacteria, yeasts, fungi, and protozoa containing such sugars within their cell walls or membranes. When bound to its target sugar moiety, MBL can activate the complement system in the classic pathway or in C1-independent manner [181]. MBL is independently associated with HbA1c among diabetic patients [182]. MBL is involved in complement activation within the diabetic kidney [183] and was discovered as a possible independent predictor of DR, DN and other vascular complications in type 1 and type 2 diabetes [184−189].

In 297 newly diagnosed T2DM patients, serum fibrinogen was a strong predictor for DN [190]. Serum Adiponectin was proved as a strong predictor of DN in both type 1 and type 2 diabetic patients according to a recent meta-analysis of 13 studies of more than five thousand cases [190].

II. Discussion

Diabetic complications pose a massive public health and economic burden. The introduction of GLP1RAs, DPP4Is, and SGLT2Is has revived the hope to effectively prevent or slow down the rate of progression of these complications. These hypoglycemic agents have, in addition, a favorable effect on body weight with less likelihood to experience hypoglycemia. In parallel with their evolving evidence of CV and renal protective effects, ADA recommended SGLT2Is as second-or third-line antihyperglycemic treatment [191]. The updated consensus statement on management of hyperglycemia in type 2 diabetes issued by EASD and ADA has also recommended the early introduction of SGLT2Is and GLP1RAs to diabetic patients with clinical CV disease and SGLT2Is to patients with CKD or clinical HF and ASCVD. These recommendations were founded on the accumulating evidence of the significant impact of these agents in secondary prevention. The lack of similar significant impact in primary prevention is likely related to the relatively short duration of CVOTs. The most famous primary prevention trial in T2DM patients is UKPDS. It took ten years after the end of this study to get significant differences in acute myocardial infarction and overall mortality between intensive therapy group and the standard of care group [192]. In spite of the significant renoprotective effect of canagliflozin in CREDENCE trial in the whole studied group, patients with eGFR≥ 60 mL/min/1.73 m2and patients with UAE ≤1000 mg/gm creatinine failed to get the expected benefit [153]. The planned duration of this study was 5.5 years. However, the study was prematurely terminated according to the observed significant difference in the composite endpoints between the 2 arms in the whole group. Given the known long duration of stage 4 DN, the short duration of this study was not enough for patients recruited with eGFR≥ 60 mL/min/1.73 m2and patients with UAE ≤1000 mg/gm creatinine to develop enough number of primary endpoints. The rate of decline of GFR in DN patients is around 6mL/min/1.73m2 [146]. The more recent results of the DECLARE – TIMI 58 did support this view. This last mentioned trial continued for 4.2 years. In this study, the significant impact of dapagliflozin was encountered in patients having baseline GFR >90, between 60 and 90, in normoalbuminuric patients, and in patients with microalbuminuria. These favorable effects in patients of DECLARE study are likely related to the relatively longer duration of follow-up [154]. Taking these results into account and according to the accumulating evidence, more energetic primary preventive studies should be designed. These new studies should select newly diagnosed diabetic patients that have laboratory markers of likelihood to develop diabetic nephropathy later during the future course of their disease. The main obstacle for such studies is the duration needed to have enough number of endpoints for adequate statistical analysis. Such long duration may lend such studies very costly and very exhaustive. Given the safety and non-inferiority of SGLT2Is, GLP1RAs, and DPP4Is, and the highlighted beneficial effects of these agents, we suggest a more reproducible approach to manage T2DM patients. In addition to T2DM patients with clinical CV disease, and those with ASCVD, patients with high cardiovascular risk should be prescribed SGLT2Is as second-line hypoglycemic agent after metformin. RAS blockers should be additionally added to guarantee optimum benefit. In the case of morbid obesity, inability to control food avidity or hyperglycemia, GLP1RAs can be used instead of SGLT2Is. In case of failure of SGLT2Is to achieve the glycemic target, either DPP4I or GLP1RA should be added as the third-line agent. SGLT2I can be added on top of GLP1RA if the later failed to achieve the glycemic target. Routine screening of diabetic patients for likelihood to develop diabetic nephropathy using the early predictors like serum MBL, fibrinogen, or adiponectin can help to select patients prone to develop diabetic nephropathy. These patients should be prescribed SGLT2Is to prevent the development of the disease instead of waiting until they develop albuminuria. This primary prevention approach can completely abort the development of DN instead of the current secondary prevention that just postpones the event for few months or years.

Conflict of Interest

The authors have nothing to declare.

References

191 Cites in Article
  1. 1. Satija Hu F B (2015). Curbing the Diabetes Pandemic. JAMA, 313(23), 2319.
  2. 2. (2016). Diabetes Mellitus – epidemiology. World health organization Global report on diabetes
  3. 3. Ingelfinger R,Rosen J (2019). Clinical Credence- SGLT2 Inhibitors, Diabetes, and Chronic Kidney Disease. N Engl J Med
  4. 4. Rao Kondapally Seshasai,S. Kaptoge,S. Thompson,A.,Di Angelantonio,E. Gao,P. Sarwar,N. (2011). Diabetes mellitus, fasting glucose, and risk of cause-specific death. N Engl J Med, 364(9), 829-841.
  5. 5. Lidia Loukine,Chris Waters,Bernard Choi,Joellyn Ellison (2012). Loukine L, Waters C, Choi B C, Ellison J. Impact of diabetes mellitus on life expectancy and healthadjusted life expectancy in Canada. Population Health Metrics, 10(1), 7.
  6. 6. Y. Zheng,M. He,N. Congdon (2012). Zheng Y, He M, Congdon N The worldwide epidemic of diabetic retinopathy. Indian J Ophthalmol, 60(5), 428-431.
  7. 7. Schootman M (2008). Epidemiology of diabetes and diabetes-related complications Phys Ther. 2008 Nov, 88(11), 1254-1264.
  8. 8. Candrilli D,Davis L,Kan J,Lucero A,Rousculp D (2007). Prevalence and the associated burden of illness of symptoms of diabetic peripheral neuropathy and diabetic retinopathy J Diabetes Complications. 2007 Sep-Oct, 21(5), 306-314.
  9. 9. Humphry L,Ballard J,Frohnert P,Chu P,O'Fallon M,Palumbo J (1989). Chronic renal failure in non-insulin dependent diabetes mellitus. A population-based study in Rochester, Minnesota. Ann Intern Med, 111, 788-796.
  10. 10. R. DeFronzo (1995). Diabetic nephropathy: etiologic and therapeutic considerations. Diabetes Rev, 3, 510-564.
  11. 11. Nichols A,Hillier A,Erbey R,Brown B (2001). Congestive heart failure in type 2 diabetes: prevalence, incidence, and risk factors Diabetes Care. Diabetes Care, 24(9), 1614-1619.
  12. 12. Melec Zeadin,Christina Petlura,Geoff Werstuck (2013). Molecular Mechanisms Linking Diabetes to the Accelerated Development of Atherosclerosis. Canadian Journal of Diabetes, 37(5), 345-350.
  13. 13. Chen R,Ovbiagele B,Feng W (2016). Diabetes and Stroke: Epidemiology, Pathophysiology, Pharmaceuticals and Outcomes Am J Med Sci. 2016 Apr, 351(4), 380-386.
  14. 14. Milton Packer (2017). Activation and Inhibition of Sodium- Hydrogen Exchanger Is a Mechanism That Links the Pathophysiology and Treatment of Diabetes Mellitus with That of Heart Failure Circulation. Circulation, 136(16), 1548-1559.
  15. 15. Kenneth Maiese,New (2015). Maiese K New Insights for Oxidative Stress and Diabetes Mellitus. Oxidative Medicine and Cellular Longevity, 2015, 1-17.
  16. 16. Cai W,Duan M,Liu Y,Yu J,Tang L,Liu L (2017). Uric Acid Induces Endothelial Dysfunction by Activating the HMGB1/RAGE Signaling Pathway. Biomed Res Int, 2017, 4391920.
  17. 17. F. Whaley,J. (2011). Glucose dynamics and mechanistic implications of SGLT2 inhibitors in animals and humans. Kidney Int Suppl
  18. 18. (1993). The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus. New England Journal of Medicine, 329(14), 977-986.
  19. 19. UK Prospective Diabetes Study (UKPDS) Group (1998). Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). The Lancet, 352(9131), 837-853.
  20. 20. Ray K,Wijesuriya Seshasai S R,Nethercott Sivakumaran R,et Preiss D (2009). Effect of intensive control of glucose on cardiovascular outcomes and death in patients with diabetes mellitus: a meta-analysis of randomised controlled trials. The Lancet, 373, 1765-1772.
  21. 21. UK Prospective Diabetes Study (UKPDS) Group (1998). Effect of intensive blood-glucose control with metformin on complications in overweight patients with type 2 diabetes (UKPDS 34) Lancet. The Lancet, 352(9131), 854-865.
  22. 22. (2018). Consensus Statement by the American Association of Clinical Endocrinologists and American College of Endocrinology on the Comprehensive Type 2 Diabetes Management Algorithm – 2018 Executive Summary. 2018 Jan, 24(1), 91-120.
  23. 23. Røder E (2018). Major adverse cardiovascular event reduction with GLP-1 and SGLT2 agents: evidence and clinical potential Ther Adv Chronic Dis. 2018 Jan, 9(1), 33-50.
  24. 24. Solis-Herrera Triplitt C,Cersosimo E,Abdul- M,Defronzo mpagliflozin (2015). mpagliflozin and linagliptin combination therapy for treatment of patients with type 2 diabetes mellitus. Expert Opin Pharmac other, 16(18), 2819-33.
  25. 25. Wakisaka M,Nagao T (2017). Sodium glucose cotransporter 2 in mesangial cells and retinal pericytes and its implications for diabetic nephropathy and retinopathy. Glycobiology
  26. 26. Furchgott F,Zawadzki V (1980). The obligatory role of endothelial cells in the relaxation of arterial smooth muscle by acetylcholine Nature. Nature, 288, 373-376.
  27. 27. Roy D,Perreault M,Marette A (1998). Insulin stimulation of glucose uptake in skeletal muscles and adipose tissues in vivo is NO dependent. Am J Physiol, 274(4 Pt 1), 692-9.
  28. 28. Wang H,Wang X,Barrett J (2011). Caveolin-1 is required for vascular endothelial insulin uptake. Am J Physiol Endocrinol Metab, 300(1), E134-E144.
  29. 29. Kolka M,Bergman N (2013). The endothelium in diabetes: its role in insulin access and diabetic complications Rev Endocr Metab Disord. 2013 Mar, 14(1), 13-19.
  30. 30. Shenouda M,Chen Widlansky M E,Holbrook Xu G,et Tabit C E (2011). Altered Mitochondrial Dynamics Contributes to Endothelial Dysfunction in Diabetes Mellitus. Circulation, 124(4), 444-453.
  31. 31. Sharma A,Bernatchez N,de B (2012). Targeting endothelial dysfunction in vascular complications associated with diabetes. Int J Vasc Med, 2012
  32. 32. Ganley-Leal Farb M G,Liang Mott M,Ercan B,et Widlansky M E (2011). Arteriolar Function in Visceral Adipose Tissue Is Impaired in Human Obesity. Arterioscler Thromb Vasc Biol, 32(2), 467-473.
  33. 33. Jia Liu,Linda Jahn,Dale Fowler,Eugene Barrett,Wenhong Cao,Zhenqi Liu (2011). Free fatty acids induce insulin resistance in both cardiac and skeletal muscle microvasculature in humans J Clin Endocrinol Metab. The Journal of Clinical Endocrinology & Metabolism, 96(2), 438-446.
  34. 34. Li Rask-Madsen C,Feather Freund B,Wu Abramov R,et al (2010). Loss of insulin signaling in vascular endothelial cells accelerates atherosclerosis in apolipoprotein E null mice. Cell Metab, 11(5), 379-389.
  35. 35. Tremolada G,Del C,Lattanzio R,Maestroni S,Maestroni A,Bandello F (2012). The role of angiogenesis in the development of proliferative diabetic retinopathy: impact of intravitreal anti-VEGF treatment. Exp Diabetes Res, 2012, 1-8.
  36. 36. Simon Satchell (2012). The glomerular endothelium emerges as a key player in diabetic nephropathy Kidney Int. Kidney International, 82(9), 949-951.
  37. 37. Alin Stirban (2014). Stirban A Microvascular dysfunction in the context of diabetic neuropathy. Current Diabetes Reports, 14(11), 541.
  38. 38. L. Exalto,R. Whitmer,L. Kappele,G. Biessels (2012). An update on type 2 diabetes, vascular dementia and Alzheimer’s disease Exp Gerontol. Experimental Gerontology, 47(11), 858-864.
  39. 39. Yukiko Kanetsuna,Keiko Takahashi,Michio Nagata,Maureen Gannon,Matthew Breyer,Raymond Harris,Takamune Takahashi (2007). Deficiency of Endothelial Nitric-Oxide Synthase Confers Susceptibility to Diabetic Nephropathy in Nephropathy-Resistant Inbred Mice. The American Journal of Pathology, 170(5), 1473-1484.
  40. 40. Wang Zhao H J,Cheng H,Takahashi Zhang M Z,et Fogo A B (2006). Endothelial nitric oxide synthase deficiency produces accelerated nephropathy in diabetic mice. J Am Soc Nephrol, 17, 2664-2669.
  41. 41. Bentzien Huber J D,Burke Boyer S J,Eickmeier De Lombaert S,et al (2012). Identification of a Potent Sodium Hydrogen Exchanger Isoform 1 (NHE1) Inhibitor with a Suitable Profile for Chronic Dosing and Demonstrated Cardioprotective Effects in a Preclinical Model of Myocardial Infarction in the Rat. 2012 Aug, 55(16), 7114-7140.
  42. 42. Tsapas Sarigianni M,Kaloyianni Mikhailidis D P,Fliegel Koliakos G,et al (2010). Na + /H + exchanger-1: a link with atherogenesis?. 2010 Dec, 19(12), 1545-1556.
  43. 43. S. Wang,Q. Peng,J. Zhang,L. Liu (2008). Na+/H+ exchanger is required for hyperglycaemia-induced endothelial dysfunction via calcium-dependent calpain Cardiovasc Res. 2008 Nov 1, 80(2), 255-262.
  44. 44. Milton Packer (2017). Activation and Inhibition of Sodium- Hydrogen Exchanger Is a Mechanism That Links the Pathophysiology and Treatment of Diabetes Mellitus with that of Heart Failure Circulation. Circulation, 136(16), 1548-1559.
  45. 45. Katusic S,Austin A (2016). Neurovascular Protective Function of Endothelial Nitric Oxide - Recent Advances Circ J. 2016 Jun, 80(7), 1499-1503.
  46. 46. Alves-Lopes R,Neves B,Montezano C,Harvey A,Carneiro S,Touyz M (2016). Internal pudental artery dysfunction in diabetes mellitus is mediated by NOX1-derived ROS-, Nrf2-, and Rho kinasedependent mechanisms Hypertension. Hypertension, 68, 1056-1064.
  47. 47. Liu Yang S,Yang Ge B (2013). Protective effects of cariporide on endothelial dysfunction induced by homocysteine Pharmacology. Pharmacology, 92(5-6), 303-309.
  48. 48. Packer M (2017). Role of the sodium-hydrogen exchanger in mediating the renal effects of drugs commonly used in the treatment of type 2 diabetes. Diabetes Obes Metab, 20
  49. 49. Gao Chang H B,Hu Nepomuceno R,paradoxical cariporide (2015). Na+/H+ exchanger in the regulation of platelet activation and paradoxical effects of cariporide. 2015 Oct, 272, 11-16.
  50. 50. Osar Z,Samanci T,Demirel Y,Damci T,Ilkova H (2004). Nicotinamide effects oxidative burst activity of neutrophils in patients with poorly controlled type 2 diabetes mellitus Exp Diabesity Res. 2004 Apr-Jun, 5(2), 155-162.
  51. 51. Hansen S,Aasum E,Hafstad D (2017). The role of NADPH oxidases in diabetic cardiomyopathy. Biochim Biophys Acta
  52. 52. Roy S,Kim D,Hernandez C,Simo R,Roy S (2015). Beneficial effects of fenofibric acid on over expression of extracellular matrix components, cox- 2, and impairment of endothelial permeability associated with diabetic retinopathy. Exp Eye Res, 140, 124-9.
  53. 53. Othman A,Ahmad S,Megyerdi S (2013). Lipoxygenasederived lipid metabolites induce retinal endothelial cell barrier dysfunction: Contribution of NADPH oxidase. PLoS One, 8(2), e57254.
  54. 54. Y. Zheng,M. He,N. Congdon (2012). Zheng Y, He M, Congdon N The worldwide epidemic of diabetic retinopathy. Indian J Ophthalmol, 60(5), 428-431.
  55. 55. Wada J,Makino H (2013). Inflammation and the pathogenesis of diabetic nephropathy Clin Sci (Lond). 2013 Feb, 124(3), 139-152.
  56. 56. Bingmei Yang,Andrea Hodgkinson,Peter Oates,Beverley Millward,Andrew Demaine (2008). High glucose induction of DNAbinding activity of the transcription factor NF-κB in patients with diabetic nephropathy Biochim Biophys. Biochimica et Biophysica Acta (BBA) - Molecular Basis of Disease, 1782(5), 295-302.
  57. 57. Yu Ha H,Kitamura Choi Y J,Lee B (2002). Role of high glucose-induced nuclear factor-κB activation in monocyte chemo attractant protein-1 expression by mesangial cells. J. Am. Soc. Nephrol, 13, 894-902.
  58. 58. Park W,Kim H,Lee H,Kim S,Ahn J,et Shin Y S (2000). High glucose-induced intercellular adhesion molecule-1 (ICAM-1) expression through an osmotic effect in rat mesangial cells is PKC-NF-ϰB-dependent. Diabetologia, 43, 1544-1553.
  59. 59. Kashihara N,Haruna Y,Kondeti K,Kanwar S (2010). Oxidative Stress in Diabetic Nephropathy. Curr Med Chem, 17, 4256-4269.
  60. 60. D. Jalal,C. Rivard,R. Johnson,D. Maahs,K. McFann,M. Rewers,J. Snell-Bergeon (2010). Serum uric acid levels predict the development of albuminuria over 6 years in patients with type 1 diabetes: findings from the Coronary Artery Calcification in Type 1 Diabetes study Nephrol Dial Transplant. 2010 Jun, 25(6), 1865-1869.
  61. 61. Ficociello H,Rosolowsky T,Niewczas A,Maselli J,Weinberg M,Aschengrau A,Eckfeldt H,Stanton C,Galecki T,Doria A,Warram H,Krolewski S (2010). High-normal serum uric acid increases risk of early progressive renal function loss in type 1 diabetes: results of a 6-year follow-up Diabetes Care. Diabetes Care, 33(6), 1337-1343.
  62. 62. Hovind P,Rossing P,Tarnow L,Johnson J,Parving H (2009). Serum uric acid as a predictor for development of diabetic nephropathy in type 1 diabetes: an inception cohort study Diabetes. Diabetes, 58(7), 1668-1671.
  63. 63. Dandan Yan,Yinfang Tu,Feng Jiang,Jie Wang,Rong Zhang,Xue Sun,Tao Wang,Shiyun Wang,Yuqian Bao,Cheng Hu,Weiping Jia (2015). Yan D, Tu Y, Jiang F, Wang J, Zhang R, Sun X, Wang T, Wang S, Bao Y, Hu C, Jia W Uric Acid is independently associated with diabetic kidney disease: a cross-sectional study in a Chinese population. PLOS ONE, 10(6), e0129797.
  64. 64. Viazzi De Cosmo S,Giorda Pacilli A,Gentile Ceriello A,Russo G,Nicolucci Rossi M C,Feig Guida P,Johnson J,Pontremoli R; AMD-Annals Study Group (2015). Serum Uric Acid and Risk of CKD in Type 2 Diabetes Clin J Am Soc Nephrol. 2015 Nov 6, 10(11)
  65. 65. Takae K,Nagata M,Hata J,Mukai N,Hirakawa Y,Yoshida D,Kishimoto H,Tsuruya K,Kitazono T,Kiyohara Y,Ninomiya T (2016). Serum Uric Acid as a Risk Factor for Chronic Kidney Disease in a Japanese Community - The Hisayama Study Circ J. 2016 Jul, 80(8), 1857-1862.
  66. 66. Bartáková V,Kuricová K,Pácal L,Nová Z,Dvořáková V,Švrčková M (2016). Hyperuricemia contributes to the faster progression of diabetic kidney disease in type 2 diabetes mellitus. J Diabetes Complications, 30(7), 1300-1307.
  67. 67. Liu P,Chen Y,Wang B,Zhang F,Wang D,Wang Y (2015). Allopurinol treatment improves renal function in patients with type 2 diabetes and asymptomatic hyperuricemia: 3-year randomized parallelcontrolled study.Clin Endocrinol (Oxf). 2015 Oct, 83(4), 475-482.
  68. 68. Tahir Kanji,Mandark Gandhi,Catherine Clase,Robert Yang (2015). Kanji T, Gandhi M, Clase C M, Yang R Urate lowering therapy to improve renal outcomes in patients with chronic kidney disease: systematic review and meta-analysis. BMC Nephrology, 16(1), 58.
  69. 69. Erlandsson Harris,H. Andersson,U. (2004). Mini-review: The nuclear protein HMGB1 as a proinflammatory mediator Eur J Immunol. Eur J Immunol, 34(6), 1503-1512.
  70. 70. Cai W,Duan M,Liu Y,Yu J,Tang L,Liu L (2017). Uric Acid Induces Endothelial Dysfunction by Activating the HMGB1/RAGE Signaling Pathway. Biomed Res Int, 2017, 4391920.
  71. 71. Ji Wang,Tianqiang Qin,Jianrong Chen,Yulin Li,Ling Wang,He Huang,Jing Li (2014). Hyperuricemia and risk of incident hypertension: a systematic review and meta-analysis of observational studies. PLoS One, 9(12), e114259.
  72. 72. T. Vilsbøll,J. Holst (2004). Incretins, insulin secretion and type 2 diabetes mellitus Diabetologia. Diabetologia, 47(3), 357-366.
  73. 73. Kalra S (2013). Glucagon-like peptide-1 receptors agonists (GLP1 RA). J Pak Med Assoc, 63(10), 1312-5.
  74. 74. S. Ross,J. Ekoé (2010). Incretin agents in type 2 diabetes Can Fam Physician. Can Fam Physician, 56(7), 639-648.
  75. 75. Inzucchi E,Bergenstal M,Buse B,Diamant M,Ferrannini E,Nauck M (2015). Management of hyperglycemia in type 2 diabetes, 2015: a patientcentered approach: update to a position statement of the American Diabetes Association and the European Association for the Study of Diabetes Diabetes Care. Diabetes Care, 38(1), 140-149.
  76. 76. Jacob Sivertsen,Jaya Rosenmeier,Jens Holst,Tina Vilsbøll (2012). The effect of glucagon-like peptide 1 on cardiovascular risk. Nature Reviews Cardiology, 9(4), 209-222.
  77. 77. Daniel Drucker (2016). The Cardiovascular Biology of Glucagon-like Peptide-1. Cell Metabolism, 24(1), 15-30.
  78. 78. Olson Lepore J J,Demopoulos L,Barbour M (2016). Effects of the Novel Long-Acting GLP-1 Agonist, Albiglutide, on Cardiac Function, Cardiac Metabolism, and Exercise Capacity in Patients With Chronic Heart Failure and Reduced Ejection Fraction. JACC Heart Fail, 4(7), 559-566.
  79. 79. Margulies B,Hernandez F,Redfield M,Givertz M,Oliveira H,Cole R (2016). Effects of liraglutide on clinical stability among patients with advanced heart failure and reduced ejection fraction: a randomized clinical trial. JAMA, 316(5), 500.
  80. 80. Pfeffer A,Claggett B,Diaz R,Dickstein K,Gerstein C,Køber V (2015). Lixisenatide in Patients with Type 2 Diabetes and Acute Coronary Syndrome. New England Journal of Medicine, 373(23), 2247-2257.
  81. 81. Marso P,Daniels H,Brown-Frandsen K,Kristensen P,Mann F,Nauck A (2016). Liraglutide and Cardiovascular Outcomes in Type 2 Diabetes. New England Journal of Medicine, 375(4), 311-322.
  82. 82. Marso P,Bain C,Consoli A,Eliaschewitz G,Jódar E,Leiter A (2016). Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes. New England Journal of Medicine, 375(19), 1834-1844.
  83. 83. Holman R R,M. Bethel,R. Mentz,V. Thompson,Y. Lokhnygina,J. Buse (2017). Effects of onceweekly exenatide on cardiovascular outcomes in type 2 diabetes N Engl J Med. N Engl J Med, 377(13), 1228-1239.
  84. 84. Røder E (2018). Major adverse cardiovascular event reduction with GLP-1 and SGLT2 agents: evidence and clinical potential Ther Adv Chronic Dis. 2018 Jan, 9(1), 33-50.
  85. 85. Keith Ferdinand,Fady Botros,Charles Atisso,Philip Sager (2016). Ferdinand K C, Botros F T, Atisso C M, Sager P T Cardiovascular safety for once-weekly dulaglutide in type 2 diabetes: a pre-specified meta-analysis of prospectively adjudicated cardiovascular events. Cardiovascular Diabetology, 15(1), 38.
  86. 86. Thomas C. (2017). The potential and pitfalls of GLP- 1 receptor agonists for renal protection in type 2 diabetes. Diabetes Metab, 43(Suppl 1), 20-2.
  87. 87. J. Int (2016). Aroor A, Zuberek M, Duta C, Meuth A, Sowers J R, Whaley-Connell A, et al., Angiotensin II Stimulation of DPP4 Activity Regulates Megalin in the Proximal Tubules. Mol Sci, 780.
  88. 88. Girardi C,Fukuda E,Rossoni V,Malnic G,Reboucas A (2008). Dipeptidyl peptidase IV inhibition downregulates Na+ - H+ exchanger NHE3 in rat renal proximal tubule. Am J Physiol Renal Physiol, 294, F414-F422.
  89. 89. Marcel Muskiet,Mark Smits,Linde Morsink,Michaela Diamant (2014). The gut–renal axis: do incretin-based agents confer renoprotection in diabetes?. Nature Reviews Nephrology, 10(2), 88-103.
  90. 90. Scirica M,Braunwald Bhatt D L,Davidson Steg P G,et Hirshberg B,Saxagliptin (2013). Saxagliptin and cardiovascular outcomes in patients with type 2 diabetes mellitus. N Engl J Med, 369, 1317-1326.
  91. 91. J. Udell,D. Bhatt,E. Braunwald,M. Cavender,O. Mosenzon,P. Steg (2015). Saxagliptin and cardiovascular outcomes in patients with type 2 diabetes and moderate or severe renal impairment: observations from the SAVOR-TIMI 53 Trial. Diabetes Care, 38, 696-705.
  92. 92. Eun Lee,J. Kim,J. Lee,M. Song,H. Ghee,J. Kang,Y. (2016). DA-1229, a dipeptidyl peptidase IV inhibitor, protects against renal injury by preventing podocyte damage in an animal model of progressive renal injury. Lab Invest, 96(5), 547-560.
  93. 93. J. Am (2012). Glorie L L, Verhulst A, Matheeussen V, Baerts L, Magielse J, Hermans N, et al., DPP4 inhibition improves functional outcome after renal ischemiareperfusion injury. Physiol Renal Physiol, 2012; 303: F
  94. 94. J. Holst,C. Deacon (2005). Glucagon-like peptide-1 mediates the therapeutic actions of DPP-IV inhibitors. Diabetologia, 48(4), 612-615.
  95. 95. J. Am (2017). Nistala R, Savin V Diabetes, hypertension and chronic kidney disease progression: Role of DPP4. Physiol Renal Physiol 2017 Apr 1; 312(4): F661-F670, F661-F670.
  96. 96. Deacon F (2005). What do we know about the secretion and degradation of incretin hormones?. Regul Pept, 128(2), 117-24.
  97. 97. M. De,I. Korom,S. Van,D. Scharpe,S. (1999). CD26, let it cut or cut it down. Immunol Today, 20, 367-375.
  98. 98. Klemann C,Wagner L,Stephan M,von S (2016). Cut to the chase: a review of CD26/dipeptidyl peptidase-4's (DPP4) entanglement in the immune system. Clinical and Experimental Immunology, 185(1), 1-21.
  99. 99. Famulla Lamers D,Hartwig Wronkowitz N,Lehr S,et Ouwens D M (2011). Dipeptidyl Peptidase 4 Is a Novel Adipokine Potentially Linking Obesity to the Metabolic Syndrome. Diabetes, 60
  100. 100. (2016). Hypoxia Alters the Expression of Dipeptidyl Peptidase 4 and Induces Developmental Remodeling of Human Preadipocytes. J Diabetes Res, 2016, 7481470.
  101. 101. Eckel Röhrborn D,smooth Lett (2014). Shedding of dipeptidyl peptidase 4 is mediated by metalloproteases and up‐regulated by hypoxia in human adipocytes and smooth muscle cells.
  102. 102. Adriana Girardi,Brenda Degray,Tamas Nagy,Daniel Biemesderfer,Peter Aronson (2001). Association of Na+-H+ Exchanger Isoform NHE3 and Dipeptidyl Peptidase IV in the Renal Proximal Tubule. Journal of Biological Chemistry, 276(49), 6671-4667.
  103. 103. Girardi C,Fukuda E,Rossoni V,Malnic G,Reboucas A (2008). Dipeptidyl peptidase IV inhibition downregulates Na+ - H+ exchanger NHE3 in rat renal proximal tubule. Am J Physiol Renal Physiol, 294, F414-F422.
  104. 104. J. Int (2016). Aroor A, Zuberek M, Duta C, Meuth A, Sowers JR, Whaley-Connell A, et al., Angiotensin II Stimulation of DPP4 Activity Regulates Megalin in the Proximal Tubules. Mol Sci 2016 May 20; 17(5). pii: E780, 780.
  105. 105. Michael Gekle (2005). RENAL TUBULE ALBUMIN TRANSPORT. Annual Review of Physiology, 67(1), 573-594.
  106. 106. G. Dekan,A. Miettinen,E. Schnabel,M. Farquhar (1990). Binding of monoclonal antibodies to glomerular endothelium, slit membranes, and epithelium after in vivo injection. Localization of antigens and bound IgGs by immunoelectron microscopy. Am J Pathol, 137, 913-927.
  107. 107. Alter L,Ott M,Tsuprykov von W K,Krause-Relle Sharkovska Y,et al (2012). DPP-4 inhibition on top of angiotensin receptor blockade offers a new therapeutic approach for diabetic nephropathy. Kidney Blood Press Res, 36, 119-351.
  108. 108. Leibowitz Mosenzon O,Cahn Bhatt DL,Hirshberg B,Wei al (2017). Effect of Saxagliptin on Renal Outcomes in the SAVOR-TIMI 53 Trial. Diabetes Care, 40, 69-76.
  109. 109. Cornel H,Bakris L,Alvarsson Stevens S R,BaxW A,et Chuang L M (2016). Effect of Sitagliptin on Kidney Function and Respective Cardiovascular Outcomes in Type 2 Diabetes: Outcomes From TECOS. Diabetes Care, 39, 2304-2310.
  110. 110. White B,Cannon P,Heller R,Nissen E,Bergenstal M,et Bakris G L (2013). Alogliptin after acute coronary syndrome in patients with type 2 diabetes. NEngl J Med, 369, 1327-1335.
  111. 111. Groop H,Perkovic Cooper M E,Kanasaki Hocher B,et Haneda M,Linagliptin,its hyperglycaemia (2017). Linagliptin and its effects on hyperglycaemia and albuminuria in patients with type 2 diabetes and renal dysfunction: The randomized MARLINA-T2D trial. Diabetes Obes Metab, 19, 1610-1619.
  112. 112. Groop H,Perkovic Cooper M E,Emser A,Woerle J,renal dysfunction (2013). Linagliptin Lowers Albuminuria on Top of Recommended Standard Treatment in Patients With Type 2 Diabetes and Renal Dysfunction. Diabetes Care, 36(11), 3460-3468.
  113. 113. Kanasaki K,Shi S,Kanasaki M,He J,Nagai T,Nakamura Y (2014). Linagliptin-mediated DPP-4 inhibition ameliorates kidney fibrosis in streptozotocin-induced diabetic mice by inhibiting endothelial-to-mesenchymal transition in a therapeutic regimen. Diabetes, 63 sx(6), 2120-31.
  114. 114. Shi S,Kanasaki Srivastava S P,Kitada He J,et Nagai T (2015). Interactions of DPP-4 and integrin β1 influences endothelial-to-mesenchymal transition. 2015 Sep, 88(3), 479-489.
  115. 115. Y. Kim,G 4,Hj Cho,H. Jeong,S. Lee,S. Lee (2016). Lee C S 1, 2, 3, Kim Y G 4, Cho HJ 1, 2, 4, Park J 1, 2, 4, Jeong H 1, Lee S E 1, 2, 4, Lee S P et al., Dipeptidyl Peptidase-4 Inhibitor Increases Vascular Leakage in Retina through VE-cadherin Phosphorylation. Lee C S, 1, 29393.
  116. 116. Chung R,Park W,Kim W (2016). PROTECTIVE EFFECTS OF DIPEPTIDYL PEPTIDASE-4 INHIBITORS ON PROGRESSION OF DIABETIC RETINOPATHY IN PATIENTS WITH TYPE 2 DIABETES. Retina, 36(12), 2357-2363.
  117. 117. Milton Packer (2018). Have dipeptidyl peptidase-4 inhibitors ameliorated the vascular complications of type 2 diabetes in large-scale trials? The potential confounding effect of stem-cell chemokines. Cardiovascular Diabetology, 17(1), 9.
  118. 118. V. Ferdousie,M. Mohammadi,G. Hassanshahi,H. Khorramdelazad,S. Falahati-Pour,M. Mirzaei (2017). Ferdousie V T, Mohammadi M M, Hassanshahi G, Khorramdelazad H, Falahati-Pour S K, Mirzaei M, et al., Serum CXCL10 and CXCL12 chemokine levels are associated with the severity of coronary artery disease and coronary artery occlusion. Int J Cardiol, 233, 23-28.
  119. 119. J. Am (2011). Darisipudi M N, Kulkarni O P, Sayyed S G, Ryu M, Migliorini A, Sagrinati C, et al., Dual blockade of the homeostatic chemokine CXCL12 and the proinflammatory chemokine CCL2 has additive protective effects on diabetic kidney disease. The American Journal of Pathology, 179(1), 116-124.
  120. 120. Butler M,Koc Guthrie S M,Caballero Afzal A,et Brooks H L,sufficient retinopathy (2005). SDF-1 is both necessary and sufficient to promote proliferative retinopathy. J Clin Invest, 115, 86-93.
  121. 121. Hompesch DeFronzo R A,Liu Kasichayanula S,Pfister Hong Y,et al (2013). Characterization of Renal Glucose Reabsorption in Response to Dapagliflozin in Healthy Subjects and Subjects With Type 2 Diabetes. Diabetes Care, 36, 3169-3176.
  122. 122. J. Clin (2017). van Bommel E J, Muskiet M H, Tonneijck L, Kramer M H, Nieuwdorp M, van Raalte D H SGLT2 Inhibition in the Diabetic Kidney-From Mechanisms to Clinical Outcome. Am Soc Nephrol, 12(4), 700-710.
  123. 123. Samukawa Chino Y,Nakai Sakai S,Nakanishi Yamaguchi J,et al (2014). SGLT2 inhibitor lowers serum uric acid through alteration of uric acid transport activity in renal tubule by increased glycosuria. Biopharm Drug Dispos, 35, 391-404.
  124. 124. Bjornstad P,Ishimoto Lanaspa M A,Kume Kosugi T,et Jalal D,Fructose,uric nephropathy (2015). Fructose and uric acid in diabetic nephropathy. Diabetologia, 58(9)
  125. 125. M. García,F. García-Arroyo,E. Tapia,H. Osorio,A. Arellano-Buendía,M. Madero (2015). Cristóbal-García M, García-Arroyo F E, Tapia E, Osorio H, Arellano-Buendía A S, Madero M, et al., Renal oxidative stress induced by long-term hyperuricemia alters mitochondrial function and maintains systemic hypertension. Oxid Med Cell Longev, 2015, 535686.
  126. 126. Ryu E-S,Kim J,Shin H-S,Jang H,Choi S,Jo I (2013). Uric acid-induced phenotypic transition of renal tubular cells as a novel mechanism of chronic kidney disease. Am J Physiol Renal Physiol, 304, 471-80.
  127. 127. Ding al (2015). Wuling San protects kidney dysfunction by inhibiting renal TLR4/MyD88 signaling and NLRP3 inflammasome activation in high fructose-induced hyperuricemic mice. 2015 Jul 1, 169, 49-59.
  128. 128. Leonard Hayflick (2003). Living forever and dying in the attempt. Experimental Gerontology, 38(11-12), 1231-1241.
  129. 129. Nakano Kitada K,Hitomi Ohsaki H,Yatabe Minamino T,et al (2014). Hyperglycemia causes cellular senescence via a SGLT2- and p21-dependent pathway in proximal tubules in the early stage of diabetic nephropathy. 2014 Sep-Oct, 28(5), 604-611.
  130. 130. Panchapakesan U,Pegg K,Gross S,Komala G,Mudaliar H,Forbes J (2013). Effects of SGLT2 inhibition in human kidney proximal tubular cells-- renoprotection in diabetic nephropathy?. PLoS One, 8(2), e54442.
  131. 131. A. Ojima,T. Matsui,Y. Nishino,N. Nakamura,S. Yamagishi (2015). Empagliflozin, an Inhibitor of Sodium- Glucose Cotransporter 2 Exerts Anti-Inflammatory and Antifibrotic Effects on Experimental Diabetic Nephropathy Partly by Suppressing AGEs-Receptor Axis Horm Metab Res. 2015 Aug, 47(9), 686-692.
  132. 132. Terami N,Ogawa D,Tachibana H,Hatanaka T,Wada J,Nakatsuka A (2014). Long-term treatment with the sodium glucose cotransporter 2 inhibitor, dapagliflozin, ameliorates glucose homeostasis and diabetic nephropathy in db/db mice. PLoS One, 9(6), e100777.
  133. 133. Cicerchi C,Li N,Kratzer J,Garcia G,Roncal- A,Tanabe K (2014). Uric acid-dependent inhibition of AMP kinase induces hepatic glucose production in diabetes and starvation: evolutionary implications of the uricase loss in hominids. FASEB J, 28(8), 3339-50.
  134. 134. Jph Wilding (2014). The role of the kidneys in glucose homeostasis in type 2 diabetes: Clinical implications and therapeutic significance through sodium glucose co-transporter 2 inhibitors. Metabolism, 63, 1228-1237.
  135. 135. Wanner C,Inzucchi E,Fitchett Lachin J M,Mattheus von Eynatten M,Empagliflozin et al (2016). Empagliflozin and Progression of Kidney Disease in Type 2 Diabetes. 2016 Jul, 375(4), 323-334.
  136. 136. Brenner M,Cooper E,de D,Keane F,Mitch E,Remuzzi Parving H H,Zhang Snapinn S M,Shahinfar Investigators (2001). Effects of losartan on renal and cardiovascular outcomes in patients with type 2 diabetes and nephropathy N Engl J Med. 2001 Sep, 345(12), 861-869.
  137. 137. Yamout H,Bakris L (2016). Diabetic nephropathy: SGLT2 inhibitors might halt progression of diabetic nephropathy Nat Rev Nephrol. 2016 Oct, 12(10), 583-584.
  138. 138. Thomas Grempler R,Himmelsbach Eckhardt M,Sauer A,et Sharp D E,Empagliflozin (2012). Empagliflozin, a novel selective sodium glucose cotransporter‐2 (SGLT‐2) inhibitor: characterisation and comparison with other SGLT‐2 inhibitors. 2012 Jan, 14(1), 83-90.
  139. 139. Cherney Z,Soleymanlou Perkins B A,Lai Maione M,et Lee A (2014). Renal Hemodynamic Effect of Sodium-Glucose Cotransporter 2 Inhibition in Patients With Type 1 Diabetes Mellitus. Circulation, 129(5), 587-597.
  140. 140. (2018). Class effects of SGLT2 inhibitors in mouse cardiomyocytes and hearts: inhibition of Na+/H+ exchanger, lowering of cytosolic Na+ and vasodilation. Diabetologia, 61(3), 722-726.
  141. 141. Roberto Vettor,Silvio Inzucchi,Paola Fioretto (2017). The cardiovascular benefits of empagliflozin: SGLT2- dependent and -independent effects Diabetologia. Diabetologia, 60(3), 395-398.
  142. 142. Baartscheer A,Schumacher A,Wüst C,Fiolet W,Coronel Stienen G J,et al,rabbits (2017). Empagliflozin decreases myocardial cytoplasmic Na+ through inhibition of the cardiac Na+/H+ exchanger in rats and rabbits. Diabetologia, 60(3), 568-573.
  143. 143. Skrtić M,Yang K,Soleymanlou Perkins B A,Lytvyn Y,et von Eynatten M,renal hyperfiltration (2014). Characterisation of glomerular haemodynamic responses to SGLT2 inhibition in patients with type 1 diabetes and renal hyperfiltration. Diabetologia, 57(12), 2599-2602.
  144. 144. Lambers Heerspink,H. de Zeeuw,D. Wie,L. Leslie,B. List,J. (2013). Dapagliflozin a glucoseregulating drug with diuretic properties in subjects with type 2 diabetes Diabetes Obes Metab. Diabetes Obes Metab, 15(9), 853-862.
  145. 145. Cherney Z,Soleymanlou Perkins B A,Zimpelmann Xiao F,et Woerle H J (2014). Sodium glucose cotransport-2 inhibition and intrarenal RAS activity in people with type 1 diabetes. 2014 Nov, 86(5), 1057-1058.
  146. 146. Heerspink J,Desai M,Jardine M,Balis D,Meininger G,Perkovic V (2017). Canagliflozin Slows Progression of Renal Function Decline Independently of Glycemic Effects J Am Soc Nephrol. 2017 Jan, 28(1), 368-375.
  147. 147. Tang H,Li G,Zhao Y,Wang F,Gower W,Shi L (2018). Comparisons of diabetic retinopathy events associated with glucose-lowering drugs in patients with type 2 diabetes mellitus: A network metaanalysis. Diabetes Obes Metab, 20(5), 1262-1279.
  148. 148. Perkovic Neal B,Mahaffey W,Fulcher de Zeeuw D,Canagliflozin et al,Cardiovascular (2017). Canagliflozin and Cardiovascular and Renal Events in Type 2 Diabetes. 2017 Aug, 377(7), 644-657.
  149. 149. (2018). Canagliflozin for Primary and Secondary Prevention of Cardiovascular Events. Circulation, 137(4), 323-334.
  150. 150. Raz Wiviott S D,Mosenzon Bonaca M P,et Kato E T,Dapagliflozin (2019). Dapagliflozin and Cardiovascular Outcomes in Type 2 Diabetes. 2019 Jan, 380(4), 347-357.
  151. 151. Rhm Furtado,M. Bonaca,I. Raz,T. Zelniker,O. Mosenzon (2019). Furtado RHM, Bonaca M P, Raz I, Zelniker T A, Mosenzon O. et al., Dapagliflozin and Cardiovascular Outcomes in Patients with Type 2 Diabetes and Prior Myocardial Infarction: A Subanalysis from DECLARETIMI-58 Trial. Circulation
  152. 152. Das R,Everett M,Birtcher K,Brown M,et Cefalu W T (2018). 2018 ACC Expert Consensus Decision Pathway on Novel Therapies for Cardiovascular Risk Reduction in Patients With Type 2 Diabetes and Atherosclerotic Cardiovascular Disease: A Report of the American College of Cardiology Task Force on Expert Consensus Decision Pathways. J Am Coll Cardiol, 72, 3200-3223.
  153. 153. Perkovic V,Jardine J,Neal B,Bompoint S,Heerspink HJL (2019). Canagliflozin and Renal Outcomes in Type 2 Diabetes and Nephropathy. N Engl J Med
  154. 154. Mosenzon O,Wiviott D,Cahn A,Rozenberg A,Yanuv I (2019). Effects of dapagliflozin on development and progression of kidney diseasein patients with type 2 diabetes: an analysis from the DECLARE-TIMI 58 randomised trial. Lancet Diabetes Endocrinol, 7(8), 606-617.
  155. 155. Di E,Sharma Jha J C,Wilkinson-Berka L,Jandeleit-Dahm A (2015). Are reactive oxygen species still the basis for diabetic complications?. Clin Sci (Lond, 129(2), 199-216.
  156. 156. C. Zoja,A. Benigni,G. Remuzzi (2014). The Nrf2 pathway in the progression of renal disease. The Nrf2 pathway in the progression of renal disease. Nephrol Dial Transplant, i19-i24.
  157. 157. Matzinger M,Fischhuber K,Heiss H (2017). Activation of Nrf2 signaling by natural products-can it all eviate diabetes?. Biotechnol Adv, 0734-9750.
  158. 158. Joshua David,William Rifkin,Piul Rabbani,Daniel Ceradini (2017). David J A, Rifkin W J, Rabbani P S, Ceradini DJThe Nrf2/Keap1/ARE Pathway and Oxidative Stress as a Therapeutic Target in Type II Diabetes Mellitus. J Diabetes Res, 2017, 4826724.
  159. 159. Jiménez-Osorio S,González-Reyes S,Pedraza- J (2015). Natural Nrf2 activators in diabetes Clin Chim Acta. Clin Chim Acta, 448, 182-192.
  160. 160. J. Int (2016). Zhang X, He H, Liang D, Jiang Y, Liang W, Chi Z H, et al., Protective Effects of Berberine on Renal Injury in Streptozotocin (STZ)-Induced Diabetic Mice. Mol Sci
  161. 161. Raish M,Ahmad A,Jan L,Alkharfy M,Ansari A,Mohsin K (2016). Momordica charantia polysaccharides mitigate the progression of STZ induced diabetic nephropathy in rats. Int J Biol Macromol, 91, 394-9.
  162. 162. Yin Q,Xia Y,Wang G (2016). Sinomenine alleviates high glucose-induced renal glomerular endothelial hyperpermeability by inhibiting the activation of RhoA/ROCK signaling pathway Biochem Biophys Res Commun. 2016 Sep 2, 477(4), 881-886.
  163. 163. Bahadoran Z,Tohidi M,Nazeri P,Mehran M,Azizi F,Mirmiran P (2012). Effect of broccoli sprouts on insulin resistance in type 2 diabetic patients: a randomized double-blind clinical trial Int J Food Sci Nutr. 2012 Nov, 63(7), 767-771.
  164. 164. J. Br (2011). Brasnyó P, Molnár G A, Mohás M, Markó L, Laczy B, Cseh J, et al., Resveratrol improves insulin sensitivity, reduces oxidative stress and activates the Akt pathway in type 2 diabetic patients. Nutr, 106(3), 383-389.
  165. 165. Goh P,Lee Y,Lau P,Supaat W,Chan H,Koh F (2014). Effects of resveratrol in patients with type 2 diabetes mellituson skeletal muscle SIRT1 expression and energy expenditure Int J Sport Nutr Exerc Metab. 2014 Feb, 24(1), 2-13.
  166. 166. J. Am (2016). Thazhath S S, Wu T, Bound M J, Checklin H L, Standfield S, Jones K L et al., Administration of resveratrol for 5 wk has no effect on glucagonlike peptide 1 secretion, gastric emptying, or glycemic control in type 2 diabetes: a randomized controlled trial. Clin Nutr, 103(1), 66-70.
  167. 167. J. Am (2012). Tomé-Carneiro J, Gonzálvez M, Larrosa M, Yáñez- Gascón M J, García-Almagro F J, Ruiz-Ros J A, et al., One-year consumption of a grape nutraceutical containing resveratrol improves the inflammatory and fibrinolytic status of patients in primary prevention of cardiovascular disease. Cardiol, 110(3), 356-363.
  168. 168. Larrosa Tomé-Carneiro J,Dávalos Yáñez-Gascón M J,Gonzálvez Gil-Zamorano J,et al (2013). One-year supplementation with a grape extract containing resveratrol modulates inflammatory-related microRNAs and cytokines expression in peripheral blood mononuclear cells of type 2 diabetes and hypertensive patients with coronary artery disease. 2013 Jun, 72, 69-82.
  169. 169. Ponzo Bo S,Evangelista Ciccone G,Saba F,Goitre al (2016). Six months of resveratrol supplementation has no measurable effect in type 2 diabetic patients. A randomized, double blind, placebo-controlled trial. 2016 Sep, 111, 896-905.
  170. 170. R. Wong,R. Nealon,A. Scholey,P. Howe (2016). Low dose resveratrol improves cerebrovascular function in type 2 diabetes mellitus. 2016 May, 26(5), 393-399.
  171. 171. Wong R H,D. Raederstorff,P. Howe (2016). Acute Resveratrol Consumption Improves Neurovascular Coupling Capacity in Adults with Type 2 Diabetes Mellitus. Nutrients, 425.
  172. 172. Yamaguchi Imamura H,Saiki Nagayama D,Shirai K (2017). Resveratrol Ameliorates Arterial Stiffness Assessed by Cardio-Ankle Vascular Index in Patients With Type 2 Diabetes Mellitus. 2017 Aug 3, 58(4), 577-583.
  173. 173. Usharani P,Mateen A,Naidu U,Raju S,Chandra N (2008). Effect of NCB-02, atorvastatin and placebo on endothelial function, oxidative stress and inflammatory markers in patients with type 2 diabetes mellitus: a randomized, parallel-group, placebo-controlled, 8-week study Drugs R D. Drugs in R & D, 9(4), 243-250.
  174. 174. Azad Javidnia K,Malekmakan L,et Nasab M H,transforming factor-β,double-blind,placebo-controlled Nephrol (2011). Oral supplementation of turmeric attenuates proteinuria, transforming growth factor-β and interleukin-8 levels in patients with overt type 2 diabetic nephropathy: a randomized, double-blind and placebo-controlled study.
  175. 175. Chuengsamarn S,Rattanamongkolgul S,Luechapudiporn R,Phisalaphong C,Jirawatnotai S (2012). Curcumin extract for prevention of type 2 diabetes Diabetes Care. Diabetes Care, 35(11), 2121-2127.
  176. 176. (2014). Curcuminoids Target Decreasing Serum Adipocyte-fatty Acid Binding Protein Levels in Their Glucose-lowering Effect in Patients with Type 2 Diabetes. Biomed Environ Sci, 27(11), 902-6.
  177. 177. R. Neerati P 1, Devde,A. Gangi (2014). Evaluation of the effect of curcumin capsules on glyburide therapy in patients with type-2 diabetes mellitus Phytother Res. Phytother Res, 28(12), 1796-1800.
  178. 178. Na L X 1,Y. Li,H. Pan,X. Zhou,D. Sun,M. Meng,X. Li,C. Sun (2013). Curcuminoids exert glucoselowering effect in type 2 diabetes by decreasing serum free fatty acids: a double-blind, placebocontrolled trial. Mol Nutr Food Res, 57(9), 1569-77.
  179. 179. 179. Davies M J, D'Alessio D A, Fradkin J, Kernan W N, Mathieu C, et al., Management of hyperglycaemia in type 2 diabetes, 2018. A consensus report by the American Diabetes Association (ADA) and the European Association for the Study of in type 1 diabetes.Diabetes. 2004 Jun; 53(6): 1570-6. 189. Hovind P 1, Hansen T K, Tarnow L, Thiel S, Steffensen R, et al., Mannose-binding lectin as a predictor of microalbuminuria in type 1 diabetes: an inception cohort study. Diabetes. 2005 May; 54(5): 1523-7. 190. Pan L, Ye Y, Wo M, Bao D, Zhu F, et al., Clinical Significance of Hemostatic Parameters in the Prediction for Type 2 Diabetes Mellitus and Diabetic Nephropathy. Dis Markers. 2018 Feb 4; 2018: 5214376. 191. Pabalan N, Tiongco R E, Pandac J K, Paragas N A, Lasta S L, et al. Association and biomarker potential of elevated serum adiponectin with nephropathy Diabetes (EASD). Diabetologia. 2018 Dec; 61(12): among type 1 and type 2 diabetics: A meta- 2461-2498.
  180. 180. Alan Garber,Martin Abrahamson,Lawrence Joshua I. Barzilay,et al (2019). Consensus Statement by the American Association of Clinical Endocrinologists and American College of Endocrinology on the Comprehensive Type 2 Diabetes Management Algorithm – 2019 Executive Summary. Endocrine Practice, 25(1), 69-100.
  181. 181. M. Turner (2003). The role of mannose-binding lectin in health and disease Mol Immunol. 2003 Nov, 40(7), 423-429.
  182. 182. Forsblom Saraheimo M,Hansen K,Fagerudd Teppo A M,et al,overt nephropathy (2005). Increased levels of mannan-binding lectin in type 1 diabetic patients with incipient and overt nephropathy. Diabetologia, 48(1), 198-202.
  183. 183. Li Q,Chang Y,Chen M,Zhao H (2018). Complement activation in patients with diabetic nephropathy. Diabetes Metab, 1262-3636.
  184. 184. Zhang Man X,Ma Yu H (2015). Increased serum mannose binding lectin levels are associated with diabetic retinopathy. 2015 Jan-Feb, 29(1), 55-58.
  185. 185. Huang Q,Shang G,Deng H,Liu J,Mei Y (2015). High Mannose-Binding Lectin Serum Levels Are Associated with Diabetic Retinopathy in Chinese Patients with Type 2 Diabetes. PLoS One, 10(7), e0130665.
  186. 186. Zhao Q,Hu Lectin (2016). Mannose‐Binding Lectin and Diabetic Nephropathy in Type 1 Diabetes. 2016 Jul, 30(4), 345-350.
  187. 187. Ling-Zhi Guan,Qiang Tong,Jing Xu (2015). Guan L Z, Tong Q, Xu J. Elevated serum levels of mannose-binding lectin and diabetic nephropathy in type 2 diabetes. PLOS ONE, 10(3), e0119699.
  188. 188. Hansen K,Tarnow L,Thiel S,Steffensen R,Stehouwer D Association between mannose-binding lectin and vascular complications analysis. PLoS ONE, 13(12), e0208905.
  189. 189. American Diabetes Association (2016). Standards of medical care in diabetes—2016. Diabetes Care, 39(Suppl 1), S1-S109.
  190. 190. Holman R R,S. Paul,M. Bethel,D. Matthews,Haw Neil (2008). year follow-up of intensive glucose controlin type 2 diabetes N Engl J Med. N Engl J Med, 359, 1577-1589.
  191. 191. (1993). The course of kidney function in type 2 (non-insulindependent) diabetic patients with diabetic nephropathy Diabetologia. Diabetologia, 36(10), 1071-1078.

Funding

No external funding was declared for this work.

Conflict of Interest

The authors declare no conflict of interest.

Ethical Approval

No ethics committee approval was required for this article type.

Data Availability

Not applicable for this article.

How to Cite This Article

Usama A A Sharaf El Din, Dina O Abdulazim. 2019. "Should We Change the Therapeutic Algorithm of Type 2 Diabetes Based on Accumulating Evidence?". Global Journal of Medical Research - K: Interdisciplinary GJMR-K Volume 19 (GJMR Volume 19 Issue 23 (K5)).

More Citation Formats

Download Citation

Issue Cover
GJMR Volume 19 Issue 23 (K5)
Pg. 27-47
Journal Specifications

Crossref Journal DOI 10.17406/gjmra

Print ISSN 0975-5888

e-ISSN 2249-4618

Keywords
Classification
GJMR-K Classification NLMC Code: WD 200
Version of record
v1.2

Issue date
July 1, 2019

Language
English
Order Article Reprint
Experience in AR

Explore published articles in an immersive Augmented Reality environment. Our platform converts research papers into interactive 3D books, allowing readers to view and interact with content using AR and VR compatible devices.

Read in 3D

Your published article is automatically converted into a realistic 3D book. Flip through pages and read research papers in a more engaging and interactive format.

Article Matrices
Total Views: 1.1K
Total Downloads: 66
All Trends

This is the heading

Lorem ipsum dolor sit amet, consectetur adipiscing elit. Ut elit tellus, luctus nec ullamcorper mattis, pulvinar dapibus leo.

High-quality academic research articles on global topics and journals.

Should We Change the Therapeutic Algorithm of Type 2 Diabetes Based on Accumulating Evidence?

Mona Salem
Mona Salem
Dina Abdulazim
Dina Abdulazim

Request Access

Please fill out the form below to request access to this research paper. Your request will be reviewed by the editorial or author team.
X