





I. INTRODUCTION
Dental anxiety is a psychological and physiological response to an extreme fear of dental treatments, the use of clinical instruments, and even the general dental clinic atmosphere. It affects the oral health of patients as they miss or delay dental appointments, which can exacerbate diseases (Yildirim 2016; Mihaela, Lyndsay 2016). Hmud & Walsh, 2007 demonstrates the same fact through statistical evidence, reporting a prevalence of between 5 and 20%, with a recent estimate of 6-15% globally, of patients who avoid dental care because of high levels of dental anxiety and dental phobia. It evokes physical, cognitive, emotional, and behavioral responses in an individual (Deva Priya, 2016). Moreover, patients with elevated anxiety have negative feelings and thoughts, sleep disturbance, increased use of medication, a greater tendency towards socialization, impaired social and occupational functioning relative to patients without dental anxiety (Gordona, Heimberga, Tellezb, & Ismail, 2013).
The consequences of dental anxiety also include bad breath, cavities, and periodontal disease. In one study, dentally anxious individuals had eight to nine decayed teeth compared to only one or two in the general population (Gordon, Sartory, & Jöhren, 2013). Having decayed or missing teeth has a strong negative impact on self-esteem (Kaur et al., 2017) and because periodontal disease is associated with cardiovascular disease, diabetes, stroke, and premature birth, he adds, the fear of going to the dentist can ultimately even be life-threatening" (American psychological association, 2016).
From a dentist's perspective, "the dentist needs to know about the patient's possible dental fear before the first procedure to be able to choose the best way to deal with the patient" (Jaakkola 2009). The dentists can become anxious when dealing with these patients because individuals with dental anxiety are more difficult to control, and, consequently, dental treatment procedures take a long time (llguy et al., 2005). As a result, it negatively affects outcomes and may give rise to occupational stress (Mihaela, 2014). Therefore, it is challenging to treat patients with dental anxiety.
Thus, it is important to understand the management modalities to relieve dental anxiety. This literature review will briefly discuss etiologies of dental anxiety, factors that impact dental anxiety, and measurement scales for dental anxiety before discussing the different management strategies for this condition.
II. ETIOLOGY OF DENTAL ANXIETY
Previous studies have examined potential etiologies for dental anxiety in adults. The significance of knowing these causes is that it will lead to determining which approach should be taken to manage it. There are various etiologies ranging from previous traumatic experiences, especially in childhood (conditioning experiences), environmental factors like vicarious learning from anxious family members or peers, genetic causes, individual personality characteristics such as neuroticism and self-consciousness, lack of understanding, exposure to frightening portrayals of dentists in the media, the coping style of the individual, perception of body image, and the vulnerable position of lying back in a dental chair (Yildirim 2016; Locker 1996 & Deva Priya 2017).
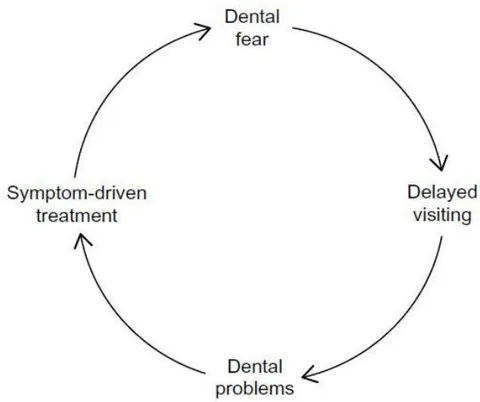
Dental anxiety itself can also worsen underlying anxiety. Fig 1 shows the vicious cycle of dental anxiety, which describes that extremely anxious patients rarely visit dental clinics. They only visit when there is an emergency such as trauma to teeth, exacerbation of dental condition, pain due to delayed appointments etc. As a result, poor oral health increases dental anxiety even more (Deva priya 2017 & Armfield 2016).
a) Factors associated with Dental anxiety
The level of dental anxiety may be affected by age, gender, education level, and socio-economic status (Jaakkola et al., 2016). Women have more dental fear than men (Yildirim et al., 2017). Recent studies have shown that dental fear is more common among younger adults than older individuals. Severe dental fear is more common among patients with low education and those who are single, than among those with higher education and in a relationship (Hagglin et al., 2000). It would be expected that being female, having a low income, and having a low perception of one's oral health status would be linked with higher levels of dental anxiety (Yildirim 2017 & Haumud 2007). Some studies say that people with low education have more anxiety while others say that people with higher education levels show more anxiety. However, age and gender are the most determining factors of Dental anxiety.
b) Determining the level of Dental anxiety
The presence of anxiety is noticed at the initial visit of a patient. However, to individualize the treatment protocol for the anxious patient, a more objective determination is necessary. Objective analysis can be done by questionnaires such as: Corah's Dental Anxiety Scale (CDAS), Modified Dental Anxiety Scale (MDAS), Spielberger State–Trait Anxiety Inventory, Kleinknecht et al's Dental Fear Survey (DFS). Previous studies show that among all the scales DFS, MDAS and CDAS are the most acceptable and reliable scales.
| CDAS | MDAS | DFS |
| 4 questions | 5 questions | 20 questions |
| 1 to 5 scores (non-anxious to extremely anxious) | 1 to 5 scores (non-anxious to extremely anxious) | 5 response options |
| Possible scores 4-20, after 15 phobic | Possible scores 5-25, 19 is the cut off for extremely anxious | Possible scores 20 to 100. ≥60 is the cut off for high anxiety |
Deva Priya (2016) says that according to these questions, anxiety level can be categorized as mild anxiety/moderate anxiety/high anxiety/phobic. The significance of knowing this level helps determine the approach for the specific patient.
c) Management strategies of Dental anxiety
Approaches are broadly categorized as psychotherapeutic approaches and pharmacological approaches. Strategy is based on the dentist's expertise, level of patient's anxiety, Patient's characteristics, and clinical situation (Yildirim 2016, Armfield & Heaton 2013).
Psychotherapeutic approaches: Psychotherapeutic approaches are listed in table 2. They are either behaviorally oriented or cognitively oriented. All these approaches are effective for mild to moderate levels of dental anxiety (deva Priya 2016; Gordon 2013; lawlicki 1991 & Lydsny 2004). Cognitively oriented approaches include cognitive behavior therapy (CBT). (Henry W. Fields, Bernard Machen & Marilyn Murphy, 1984) have conducted primary research on the acceptability of the behavioral approach. As per his research, acceptability of behavioral approach depends on its need during the time of the treatment based on the urgency of it. However, these techniques are effective in positively reinforcing the patient for the long-term.
| Psychotherapeutic Approaches |
| Communication skills, rapport, and trust building: iatro sedative technique |
| Relaxation techniques: deep breathing, muscle relaxation |
| Brief relaxation or functional relaxation therapy |
| Autogenic relaxation |
| Ost's applied relaxation technique |
| Deep relaxation or diaphragmatic breathing |
| Relaxation response |
| Guided imagery |
| Biofeedback |
| Hypnotherapy |
| Acupuncture |
| Distraction |
| Enhancing control |
| "Tell-show-do", signaling |
| Systematic desensitization or exposure therapy |
| Positive reinforcement |
| Cognitive therapy |
| Cognitive behavioral therapy (CBT) |
This literature review will focus on the following behavioral and cognitive psychotherapeutic management modalities that have proven to be most effective and can be performed without advanced technical equipment: relaxation, distraction, communication and environment, acupuncture, and cognitive behavioral therapy.
Patients with mild level dental anxiety
1) Communication and Environment
The communicative ability provides the first impression of the provider to the patient. Deva Priya (2016) states that there should be a two way, non-judgmental, composed, and calm communication between a doctor and a patient. As mentioned in the table, 'iatrosedative technique' is a process of communication between a dental practitioner and the patient that creates a bond of understanding, trust, and confidence (JM Armfield & LJ Heaton, 2013). This technique mainly involves a systemic approach to make the patient feel calm and comfortable by the dental practitioner's behavior, attitude, and communicative stance (JM Armfield & LJ Heaton, 2013).
2) Deep breathing and muscle relaxation
When a patient is physically relaxed, it is difficult to make them psychologically anxious (Deva Priya, 2016). When patients enter the clinic, the doctor should first communicate amicably to make them relaxed. Raghad Hmud & Laurence Walsh, 2007 and Deva Priya 2016 similarly emphasize that Jacobsen's progressive muscular relaxation technique is most acceptable and effective. It involves tensing specific muscle groups for 5–7 seconds, followed by 20 seconds of relaxation. The method can be demonstrated at the bedside and should be practiced and rehearsed by the patient at home. Other relaxation methods include Ost's applied relaxation technique, functional relaxation, the rapid-relaxation technique, autogenic relaxation, and relaxation response (Deva Priya 2016).
3) Guided imagery
Guided imagery has been defined as a directed, deliberate daydream that uses all the senses to create a focused state of relaxation and a sense of physical and emotional well-being. It is a mind–body exercise in which patients are taught to develop a mental image of a pleasant, tranquil experience that consciously guides their attention to achieve relaxation. There are generally three stages to guided imagery: relaxation, visualization, and positive suggestion (Deva Priya et al., 2016). To make the patient visualize the place or the object of their selection, the doctor should make the script or sound or smell according to it to make the patient feel relaxed and in an imagery phase. This method is effective in anxious pediatric patients as children enjoy hearing stories.
4) Distraction and Acupuncture
Distraction techniques have been found to be as effective as relaxation-based techniques, and superior to no intervention. Audio-taped distractions are more effective than video-taped, possibly since they allow children to close their eyes and hence avoid the feared stimulus (T. Newton, K. Asimakopoulou, B. Daly, S. Scambler and S. Scott5 Essential 2012). Distraction by background peaceful music is an effective approach according to this author's experience.
Acupuncture is a technique in which a disease is treated by inserting needles at various points on the body, known as acupuncture points. It has been reported that acupuncture is effective in treating dental problems such as anxiety, temporomandibular dysfunction syndrome, pain, and Sjögren's syndrome. It is an inexpensive treatment modality that requires special training before it can be incorporated into practice. Reports on the use of auricular acupuncture for treating chronic and acute anxiety have shown promising results (Deva Priya 2016).
5) Tell-show-do
This technique is useful for children and adults as well. First, show the instrument or material which is being used. Showing a visual model of the procedure or the videos to the patients helps in increasing patient's confidence and ensures the feeling of safety and security in them (Deva Priya 2016).
Patients with moderate level of Dental anxiety
Cognitive behavior therapy
Cognitive behavior therapy (CBT) is an example of brief psychological therapy. T newton (2012) states that, "It is a synthesis of behavior therapy and cognitive therapy and uses both behavior modification techniques and cognitive restructuring procedures to change the behavior of the patient. CBT includes learning relaxation skills, conducting mini-experiments and systematic desensitization (constructing a hierarchy of situations that elicit varying and increasing degrees of anxiety or fear and then progressing through the hierarchy in a relaxed, non-anxious manner)" (T. Newton, K. Asimakopoulou, B. Daly, S. Scambler and S. Scott5 Essential 2012). Mihaela Dumitrachea, Valentina Neacsub & Ionela, 2014 conducted a study to measure CBT's efficacy with 47 patients of a private dental clinic. They concluded that the possibility of getting a substantial reduction in dental anxiety level is high with the sessions of cognitive reconstruction.
Patients with high-level of Dental anxiety
Pharmacological approach
It includes conscious sedation and general anesthesia. Pharmacological approaches to the management of patients with dental phobia are well established, including relative analgesia, conscious sedation, and general anesthesia (T. Newton, K. Asimakopoulou, B. Daly, S. Scambler and S. Scott5 Essential 2012). There is an ongoing need for such services when individuals delay treatment to the point where they are in severe pain or have otherwise compromised their oral health. However, in general, pharmacological approaches are less acceptable in the management of dental fear when compared to psychological techniques by individuals with extreme dental fear and members of the public(T. Newton, K. Asimakopoulou, B. Daly, S. Scambler and S. Scott5 Essential 2012).
III. CONCLUSION
Despite advances in dental equipment in contemporary dentistry, anxiety associated with dental practice and fear of pain related to dentistry remain common. 73% to 79% of individuals have at least some dental anxieties (Yildirim, 2017). Patients with low to moderate anxiety can be treated by behavior therapies as studies have shown its effects. Patients should be encouraged to maintain good oral health to prevent them from going to a vicious cycle of anxiety. However, a highly anxious patient needs a conventional sedation method. Moreover, past childhood experience impacts a lot in developing anxiety in adulthood. It is recommended for a Dentist to be incredibly careful while treating child patients so that they do not develop anxiety due to traumatic or fearful experience. Thus, managing anxiety will help dentists to perform successful treatment and for an anxious person to maintain good oral health.



