
I. INTRODUCTION
In recent years, there has been an increase in the occurrence of cardiovascular diseases (CVD) around the world, resulting in a greater risk to the health and development of the population. These diseases are currently characterized as one of the main causes of death in the world[^1], with an estimate of 23 million deaths annually by 2030, predominantly in low- and middle-income countries[^2].
Various factors can be considered when analyzing the risk of developing CVD, such as smoking, physical activity, body mass index (BMI), blood pressure, glycemia, cholesterol, environment, and others[^3]. Several studies have shown that the greater the number of factors, the greater the risk of cardiovascular events4, 5, 6, emphasizing the importance of measuring risks and applying them to individuals and the population, in order to propose health promotion actions aimed at preventing diseases and illnesses[^7]. However, implementing lifestyle change strategies and interventions on a population basis is still a challenge.
In recent years, there has been an increase in the occurrence of cardiovascular diseases (CVD) worldwide, resulting in a greater risk to the health and development of the population. These diseases are currently characterized as one of the main causes of death in the world[^8], with an estimated 23 million deaths per year by 2030, predominantly in low- and middle-income countries[^9].
A low-risk profile for cardiovascular disease (untreated cholesterol , untreated blood pressure , never smoked and no history of diabetes mellitus or myocardial infarction) in middle age is associated with markedly better health outcomes in older age, but few middle-aged adults have this low-risk profile[^10]. In a study[^11] with 3,154 participants, the authors examined whether the adoption of a healthy lifestyle throughout young adulthood is associated with the presence of a low cardiovascular disease risk profile in middle age, and concluded that maintaining a healthy lifestyle throughout young adulthood is strongly associated with a low cardiovascular disease risk profile in middle age. Individual and public health efforts are needed to improve the adoption and maintenance of healthy lifestyles in young adults.
In view of the above, there is a clear need to evaluate the factors that predispose to cardiovascular health, as well as to analyze the increase in cardiovascular risks in relation to normal levels, establishing a correlation with the lifestyle of young adults. The aim of this study was to identify the main risk factors for cardiovascular health in young adults associated with lifestyle, to analyze the cardiovascular health risks of young adults between the ages of 30 and 50, and to correlate the risks with the lifestyle of young adults.
II. METHODS
This is a cross-sectional study with a quantitative approach. The project was approved by the Research Ethics Committee (CEP) under opinion no. 5.311.307. Young adults of both sexes were recruited, with a minimum age of 30 and a maximum age of 50. The study did not include individuals undergoing chemotherapy, post-surgery patients with less than a year to go before surgery, patients discharged from hospital after less than six months, individuals with stroke sequelae or COVID-19.
Some data were collected, such as blood pressure, muscle strength, total and fractional cholesterol, blood glucose, anthropometric measurements, bioimpedance, heart rate, double product, recovery of the double product after an exercise test, lifestyle, and Framingham cardiovascular risk. The data were analyzed to find out if there was an increase in cardiovascular risk in these participants.
a) Anthropometric Assessment
A portable electronic scale from the Multilaser brand was used to measure the weight of all the participants, with a capacity of and a sensitivity of . The participants removed their shoes and jackets, respecting everyone's privacy. The participant was positioned in the center of the equipment, in an upright posture, with their feet together and arms outstretched close to their body. The participant remained in this position until the reading was taken[^12].
b) Bioimpedance
Bioimpedance testing (BIA) assesses body composition, and is a simple, non-invasive procedure with reproducible results and rapid acquisition of muscle mass and fat mass in grams and percentages. From this test it is possible to obtain data on body hydration, bone density, visceral fat and basal metabolic rate . To carry out the test, the participant lay supine and the electrodes were placed on the upper and lower limbs while the software recorded the data.
c) Blood Pressure Measurements
BP was measured according to the VII Brazilian Guideline on Hypertension of , with the patient resting for 3 to 5 minutes in a quiet environment, before and during the measurement. In the sitting position, with legs uncrossed, feet flat on the floor, back against the chair and relaxed. The participant was instructed not to talk during the measurement, and any doubts were clarified before or after the procedure.
d) Heart Rate
Heart rate was measured using the patient's wrist. Once the artery was located, the index and middle fingers were pressed down and the rate was measured for 60 seconds using a digital or analog clock. Reference values vary between age groups. In this study, the value used for adults was 60 to 100 beats/ .
e) Capillary Blood Glucose
A calibrated Accu-Chek glucose meter was used to obtain capillary blood glucose values. The participant's finger was wiped with alcohol to decontaminate it, and then the test strip was inserted into the device. With the lancet, a small hole was made in the digital pulp of the finger, and blood was collected with the reagent strip to obtain the glycemic reading from the device.
f) Lipid Profile (Total Cholesterol, Fractionated and Triglycerides)
Approximately of blood was collected by venipuncture for the biochemical measurement of Low-Density Lipoprotein (LDLc), High Density Lipoprotein (HDLc) and Tricylglycerides (TG). The blood samples were processed and the serum (for TC, TG, LDLc and HDLc) and plasma (for glycemia) were analyzed in a clinical analysis laboratory. Serum levels of TC, HDLc and TG were obtained using the colorimetric-enzyme method[17, 18].
g) Heart Rate Recovery and Double Product
The step test to check heart rate (HR) recovery was carried out with the individual at rest, the first HR data was collected, followed by BP. Afterwards, the individual walked up and down an 11-step staircase for three minutes, then was instructed to sit down and HR and BP were collected again. This measurement is called peak exercise data, after which the data is collected every minute, with the subject always sitting down, and then the HR and BP recovery per minute is observed, totaling five minutes of recovery time and six HR samples.
The data was collected with the participant in the supine position, placing the forearm next to the lower chest with the elbow at a angle. A superficial artery in the area was palpated and gently compressed, thus counting the arterial beats for 1 minute. The reference value for HR in adults is 60 to 100 beats per minute .
The double product (DP) is an indirect predictor of myocardial oxygen consumption and is a parameter of cardiovascular risk during exercise. The double product is the multiplication of heart rate (HR) by systolic blood pressure .
h) Framingham Cardiovascular Risk
The Framingham study is the most widely used theoretical framework in the world, which shows a causal relationship with CVD. Thus, based on its relevance, the use of the ERF justifies the appropriate stratification of CVR for future CVD. Thus, the primary outcome of the study is to assess cardiovascular risks in young adults.
i) Data Analysis
All results were expressed as absolute numbers and percentages for categorical variables, while continuous variables were presented as mean and standard deviation and/or median and interquartile range (IQR). Data symmetry was analyzed using the Kolmogorov-Smirnov test.
j) Results
Fifty-two patients were assessed, but only 31 completed all the evaluations. Nine patients didn't have their total and fractional cholesterol measured, six patients didn't have their physical tests, and another seven patients only filled in the questionnaires. The average age of the participants was 42.5 years, with the majority being female, there were six hypertensive patients and two with systolic hypertension, four patients had high blood glucose levels, all patients recovered their heart rate and double product within the first five minutes of completing the test.
| Variables | Mean and Standard Deviation |
| Age (years) | 42,5±7,2 |
| Women (%) | 66,6 |
| IMC (kg/m2) | 27,3±4,1 |
| Lean Mass (KG) | 49,8±9,3 |
| Lean Mass (%) | 68,5±6,9 |
| Fat Mass (KG) | 23,3±7,7 |
| Fat Mass (%) | 31,4±6,9 |
| Basal metabolic rate (Kcal) | 1519±300 |
| Cholesterol Total (mg/dl) | 192,4±40,3 |
| HDL (mg/dl) | 53,4±15,5 |
| LDL (mg/dl) | 138,9±41,4 |
| Triglycerides (mg/dl) | 125,7±59,9 |
| Resting HR (bpm) | 89,5±24,2 |
| SBP (mmHg) | 122,5±21,2 |
| PAD (mmHg) | 89,4±13,2 |
| Blood sugar (mg/dl) | 95±21,4 |
| Double product at rest | 6.890±4.235 |
| Lifestyle | 23,2±8,6 |
The cardiovascular risk measured by the Framingham score was found to be moderate or intermediate for four people and high for three participants, the others were classified as low.
The final Framingham cardiovascular risk score was correlated with the total score of the individual lifestyle questionnaire (PEVI) and a good inverse correlation was found, i.e. the higher the PEVI score, the better the lifestyle, the lower the Framingham score, i.e. the lower the cardiovascular risk Figure 1.
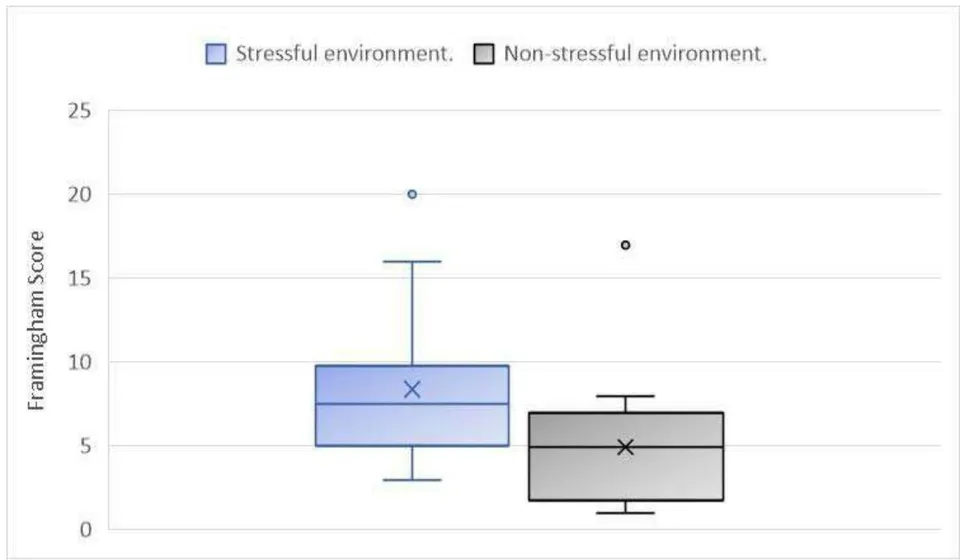
The Framingham score was evaluated for the participants who reported living or not living in a stressful environment. It was found that cardiovascular risk was significantly increased for those participants who reported living in a stressful environment (p=0.03, Figure 2).
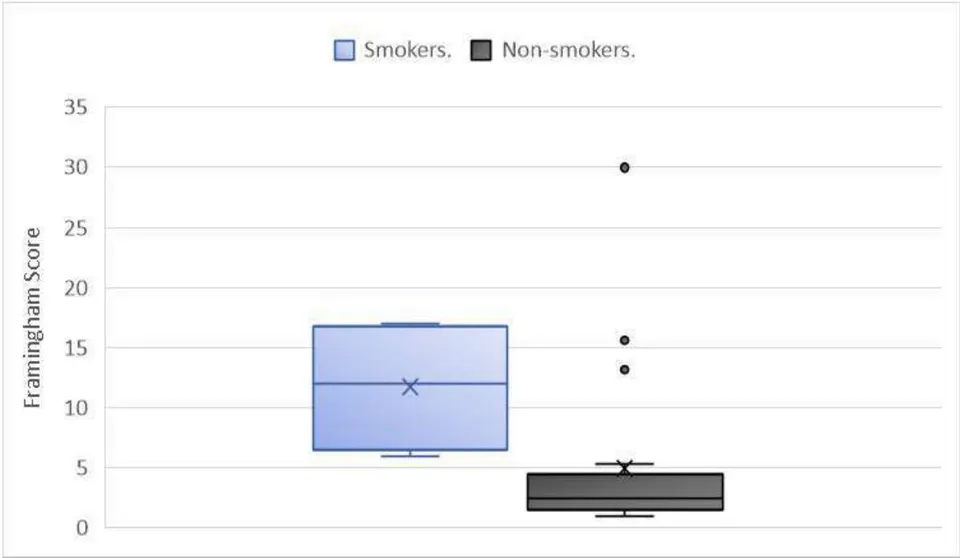
The Framingham score was evaluated for the groups of smokers and non-smokers. It was found that the cardiovascular risk was significantly increased for smokers compared to non-smokers , figure 3.
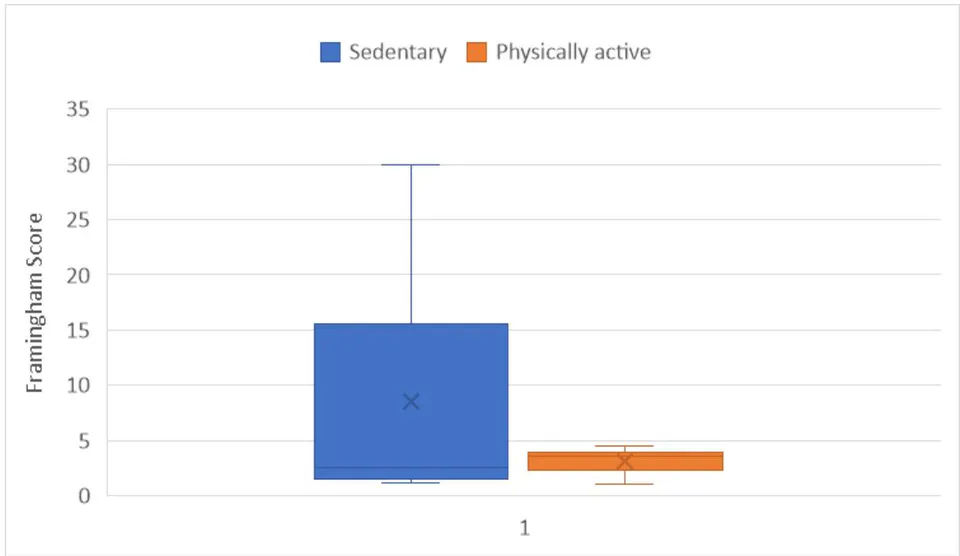
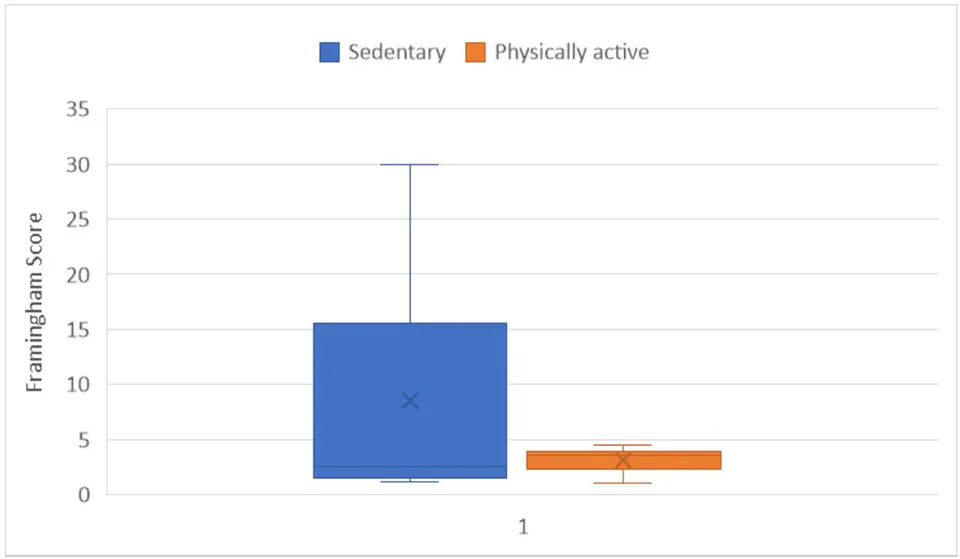
The Framingham score was evaluated for physically active and sedentary participants. It was found that the cardiovascular risk was significantly increased for those participants who were sedentary compared to those who were physically active , figure 4.
k) Discussion
The main results of this study show that four risk factors significantly affect health and predisposition to cardiovascular events: physical inactivity, stressful environments, smoking, and lifestyle. These factors do not act separately and, when combined, exponentially increase the chances of cardiovascular events occurring.
The average age of those interviewed was 42.5 years, with being female, as shown in Table 1.
Compared to the official data for the municipality of São Paulo, more than half of the entire population of São Paulo is female (51%) 20. According to Carneiro21, women seek primary health care more than men due to their concern, care, and awareness of their own health.
The average body mass index of the population studied was , which is characteristic of overweight. These data corroborate the results found in VIGITEL 2021, with of the Brazilian population being overweight[22].
Based on the Framingham risk score, low cardiovascular risk was found for 77.4 of the participants, with 22.5 between intermediate and high risk. Similar results were observed in a study estimating the 10-year cardiovascular risk of the Brazilian population, which showed a greater predominance of low risk for both men and women[23]. However, it is important to point out that there are several factors that can lead to CVD, so all of them must be taken into account.
According to our findings, the better the lifestyle of individuals, the lower their cardiovascular risk. It is important to note that lifestyle can act as a protective barrier against chronic degenerative diseases during ageing .
In the present study, the stressful environment was significant in increasing cardiovascular risk. A study of employees at a university hospital in Rio Grande do Sul found that of participants had intermediate levels of occupational stress. These results reflect the relationship between work as the main factor influencing an individual in association with a stressful environment and with considerable emotional tension[25].
With regard to smoking, the CV risk was more than double. These results corroborate a multinational prospective cohort study which found a strong association between smoking and CV risk in 21 low-, middle- and high-income countries, and these data are even superior to the relationship between physical activity[^6].
In our findings, individuals who practiced physical activity and were labeled non-sedentary showed a reduction in cardiovascular risk compared to non-practitioners. Several studies have shown that a sedentary lifestyle is an important factor associated with worse cardiovascular health indicators, such as BMI, waist circumference and blood markers (glucose, lipid profile, lipoproteins and insulin)[26](LEIVA et al., 2017). High levels of physical activity can help neutralize the adverse effects of body fat, among other common CVD risk factors.
In their retrospective cohort study, Porto et al.24 observed a reduction in physical activity between youth and adulthood. Of the participants, reported having practiced sports in their teens and twenties, but only did so in adulthood, which is worrying for the continuity of health care in later life.
A study was carried out with 48 elderly hypertensive patients, using a 12-day protocol to practice physical activity. It was then observed that even in a group at risk of cardiovascular disease, it was possible to identify a reduction in this prominent risk, improving depressive symptoms, increasing quality of life, and reducing total cholesterol and LDL[^5].
The main limitations of this study include the external validity of the data, which does not allow the results to be generalized, the cross-sectional design, which makes it difficult to make inferences, and possible memory biases. However, in order to minimize potential sources of error, some precautions were adopted, such as the evaluation of a large and representative sample, stratified and random selection of participants, small proportions of losses and evaluation of the outcome based on the use of anthropometric, biochemical and hemodynamic information derived from measured information and not self-report, which could underestimate the prevalence of the risk factors evaluated.
Fortaling the role of professional nurses in this paradigm, when one realizes the impact that health education for self-care has on patients with various diseases and the importance of drawing up a therapeutic plan that is coherent with cardiovascular risk assessment.
It is believed that this study can contribute to enlightening not only the general population, but also health professionals and the general population about cardiovascular risks.
III. CONCLUSION
Through this study, it was possible to conclude that severe and moderate cardiovascular risk was found for of the sample. Smoking, a sedentary lifestyle and living in a stressful environment were the main cardiovascular risk factors found.